The Keyword that Defines our Approach to Design is ‘Active’.

The keyword that defines our approach to design is ‘Active’.

If we look up the definition of ‘Active Birth’ we get, “Childbirth during which the mother is encouraged to move around freely and assume any position which feels comfortable”.

Founder and Director Keith Brainin spent 17 years as co-director of the Active Birth Centre in London with world famous author, educator and childbirth activist Janet Balaskas where he met water birth pioneer Michel Odent, Sheila Kitzinger and many other midwives and childbirth experts.

The knowledge and understanding gained from this formative experience has enabled us to design water birth pools that uniquely fulfil the needs of labouring women enabling them to have a better experience of labour and birth.

Freedom of movement combined with the relaxing effects of warm water and release of oxytocin significantly increases the possibility of a physiological labour and natural active birth.

We’ve spent decades observing the way that mothers move in our pools and considered how to best serve their needs.

Our passion for excellence has led us to study ergonomic design theory and to work closely with mothers, midwives, health and safety and manual handling experts.

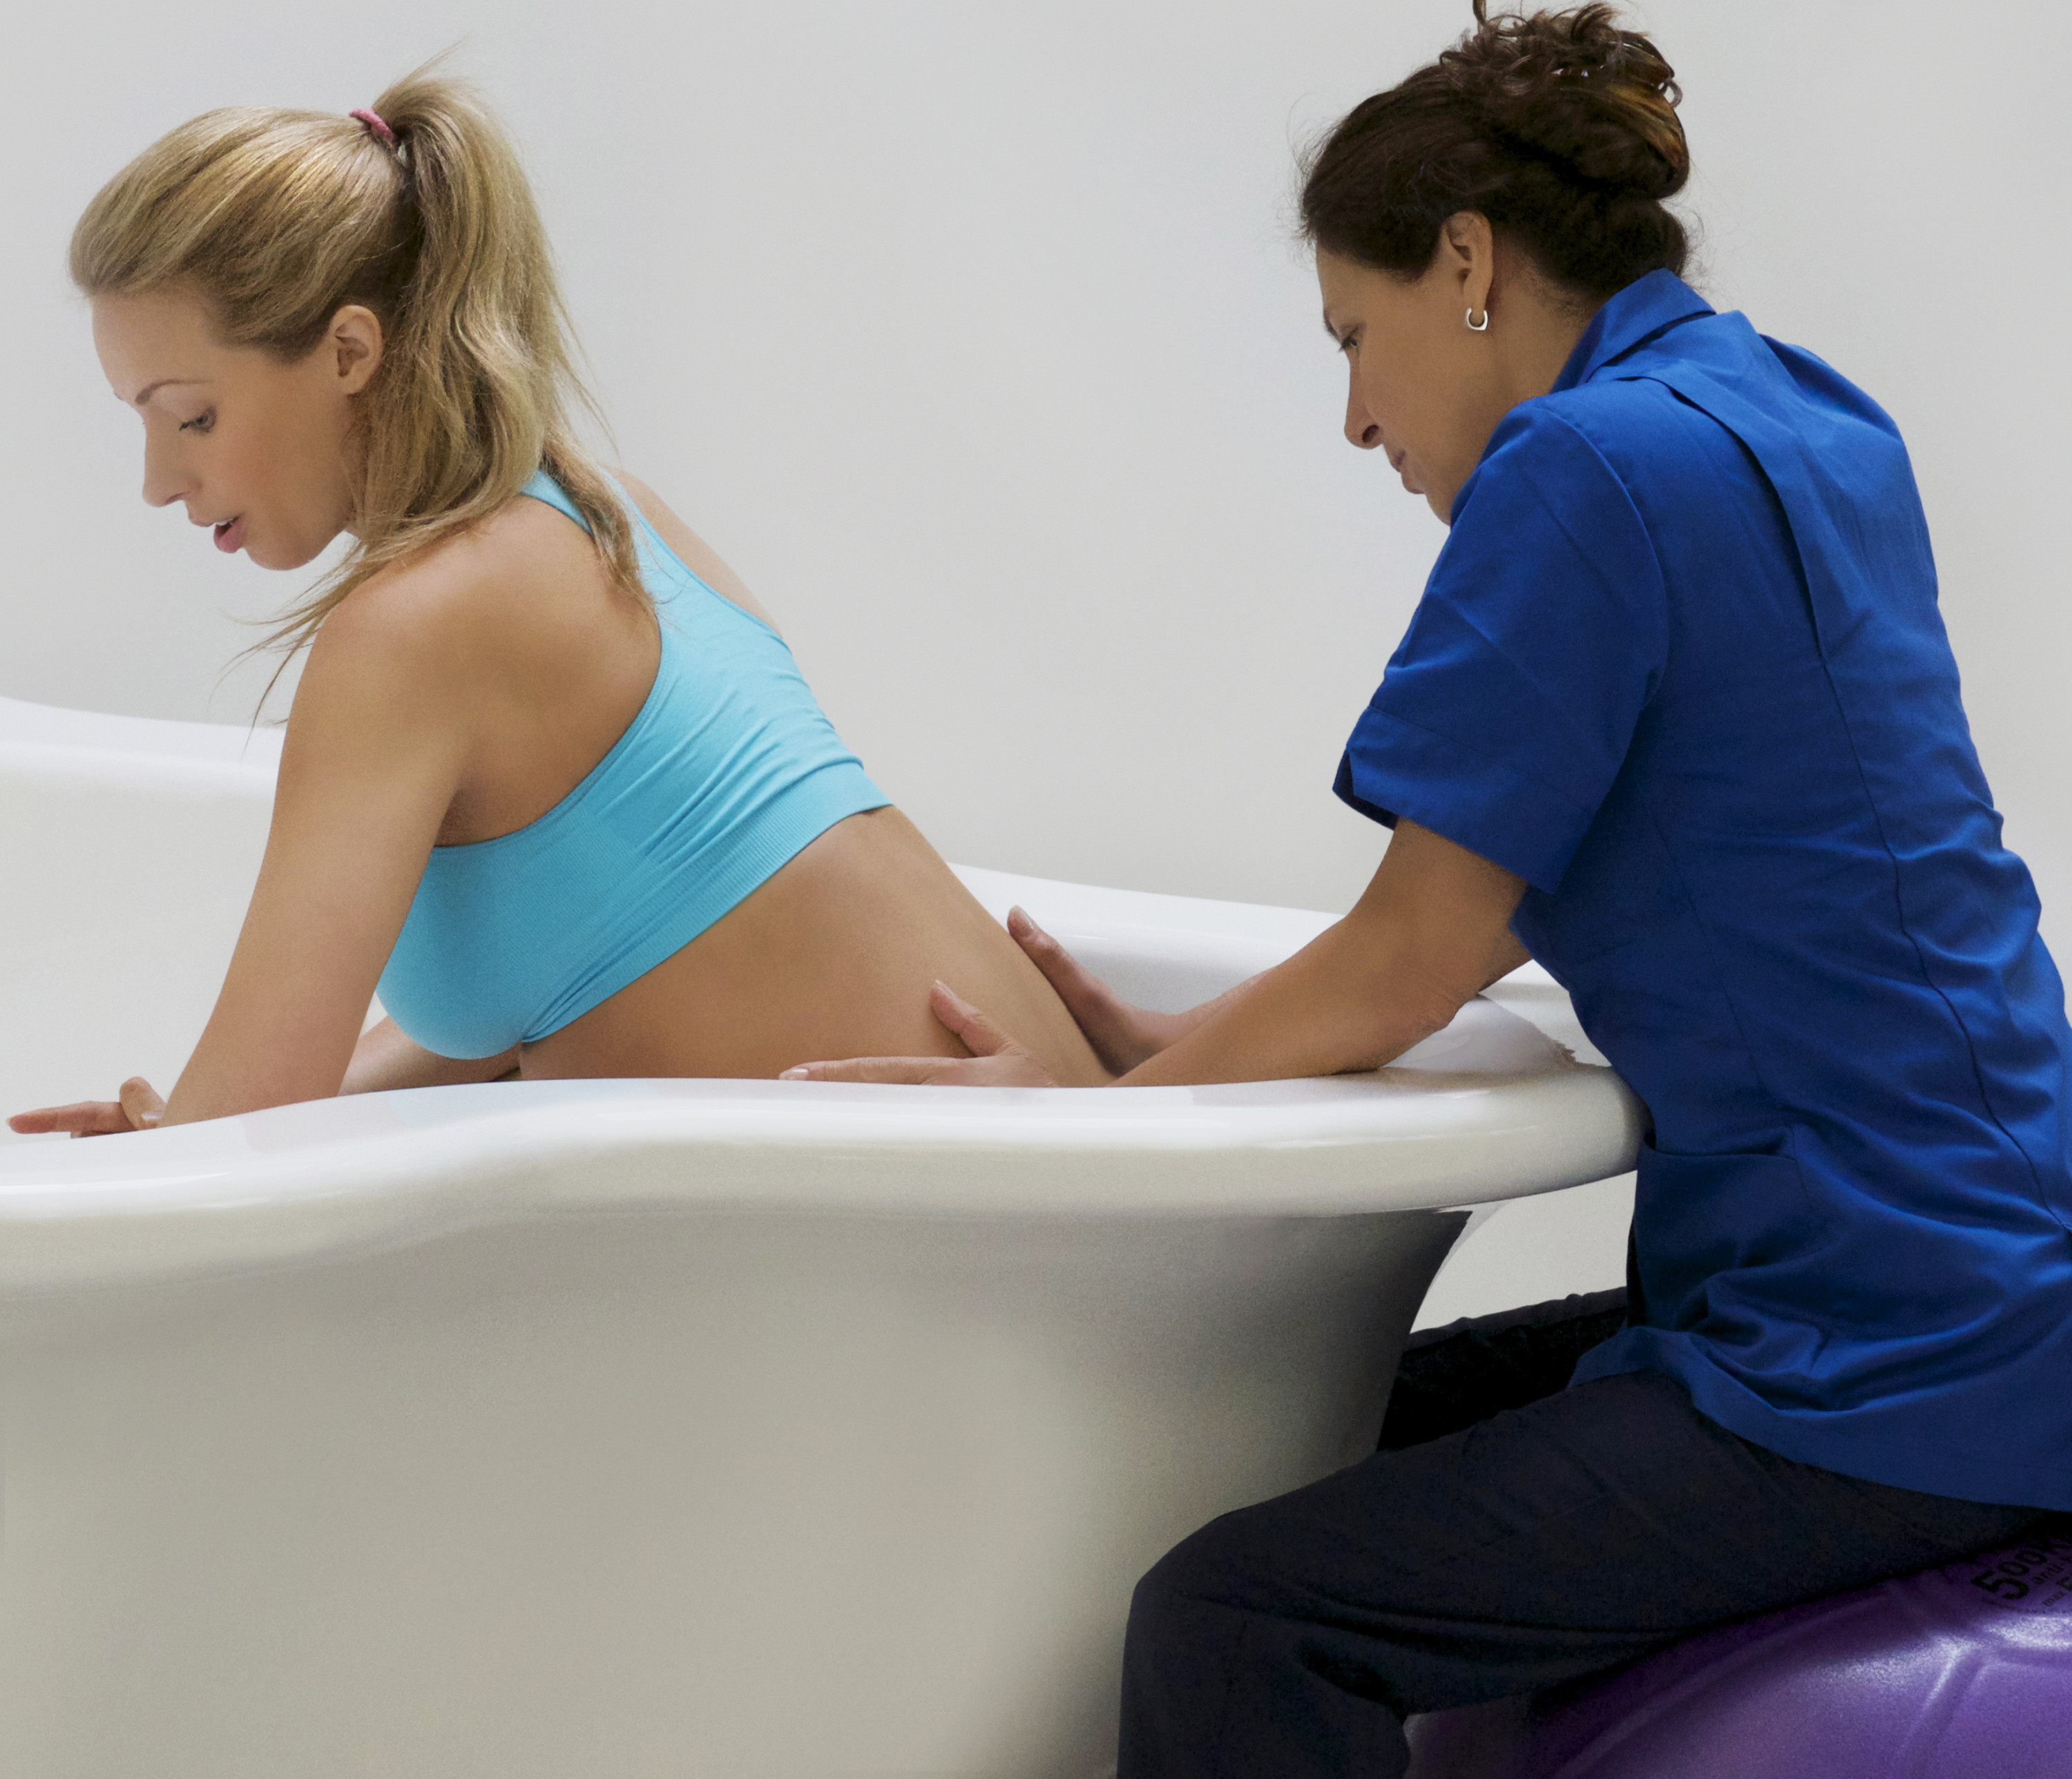
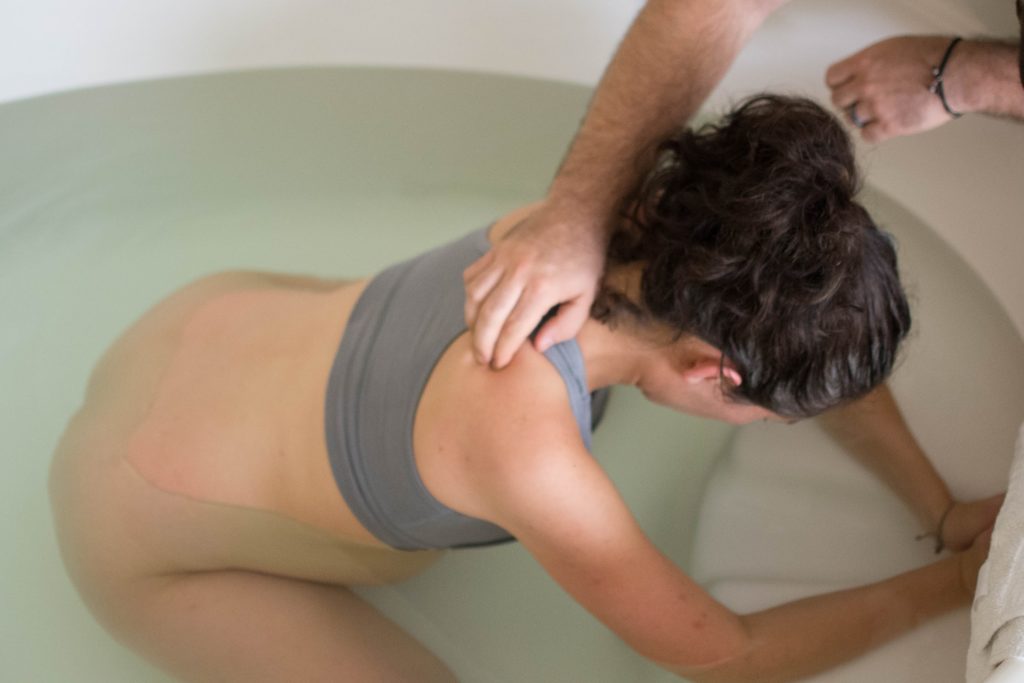
Active Birth Pools provide optimum support for mothers in the range of upright positions natural to labour and birth.

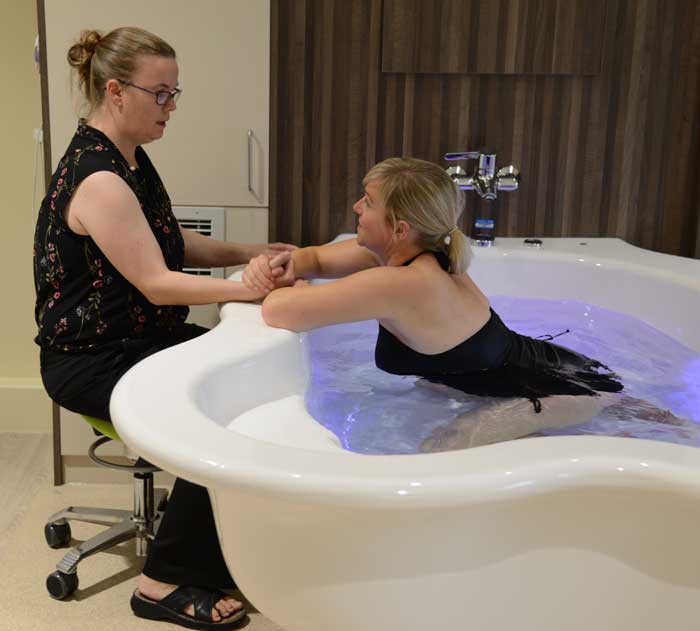
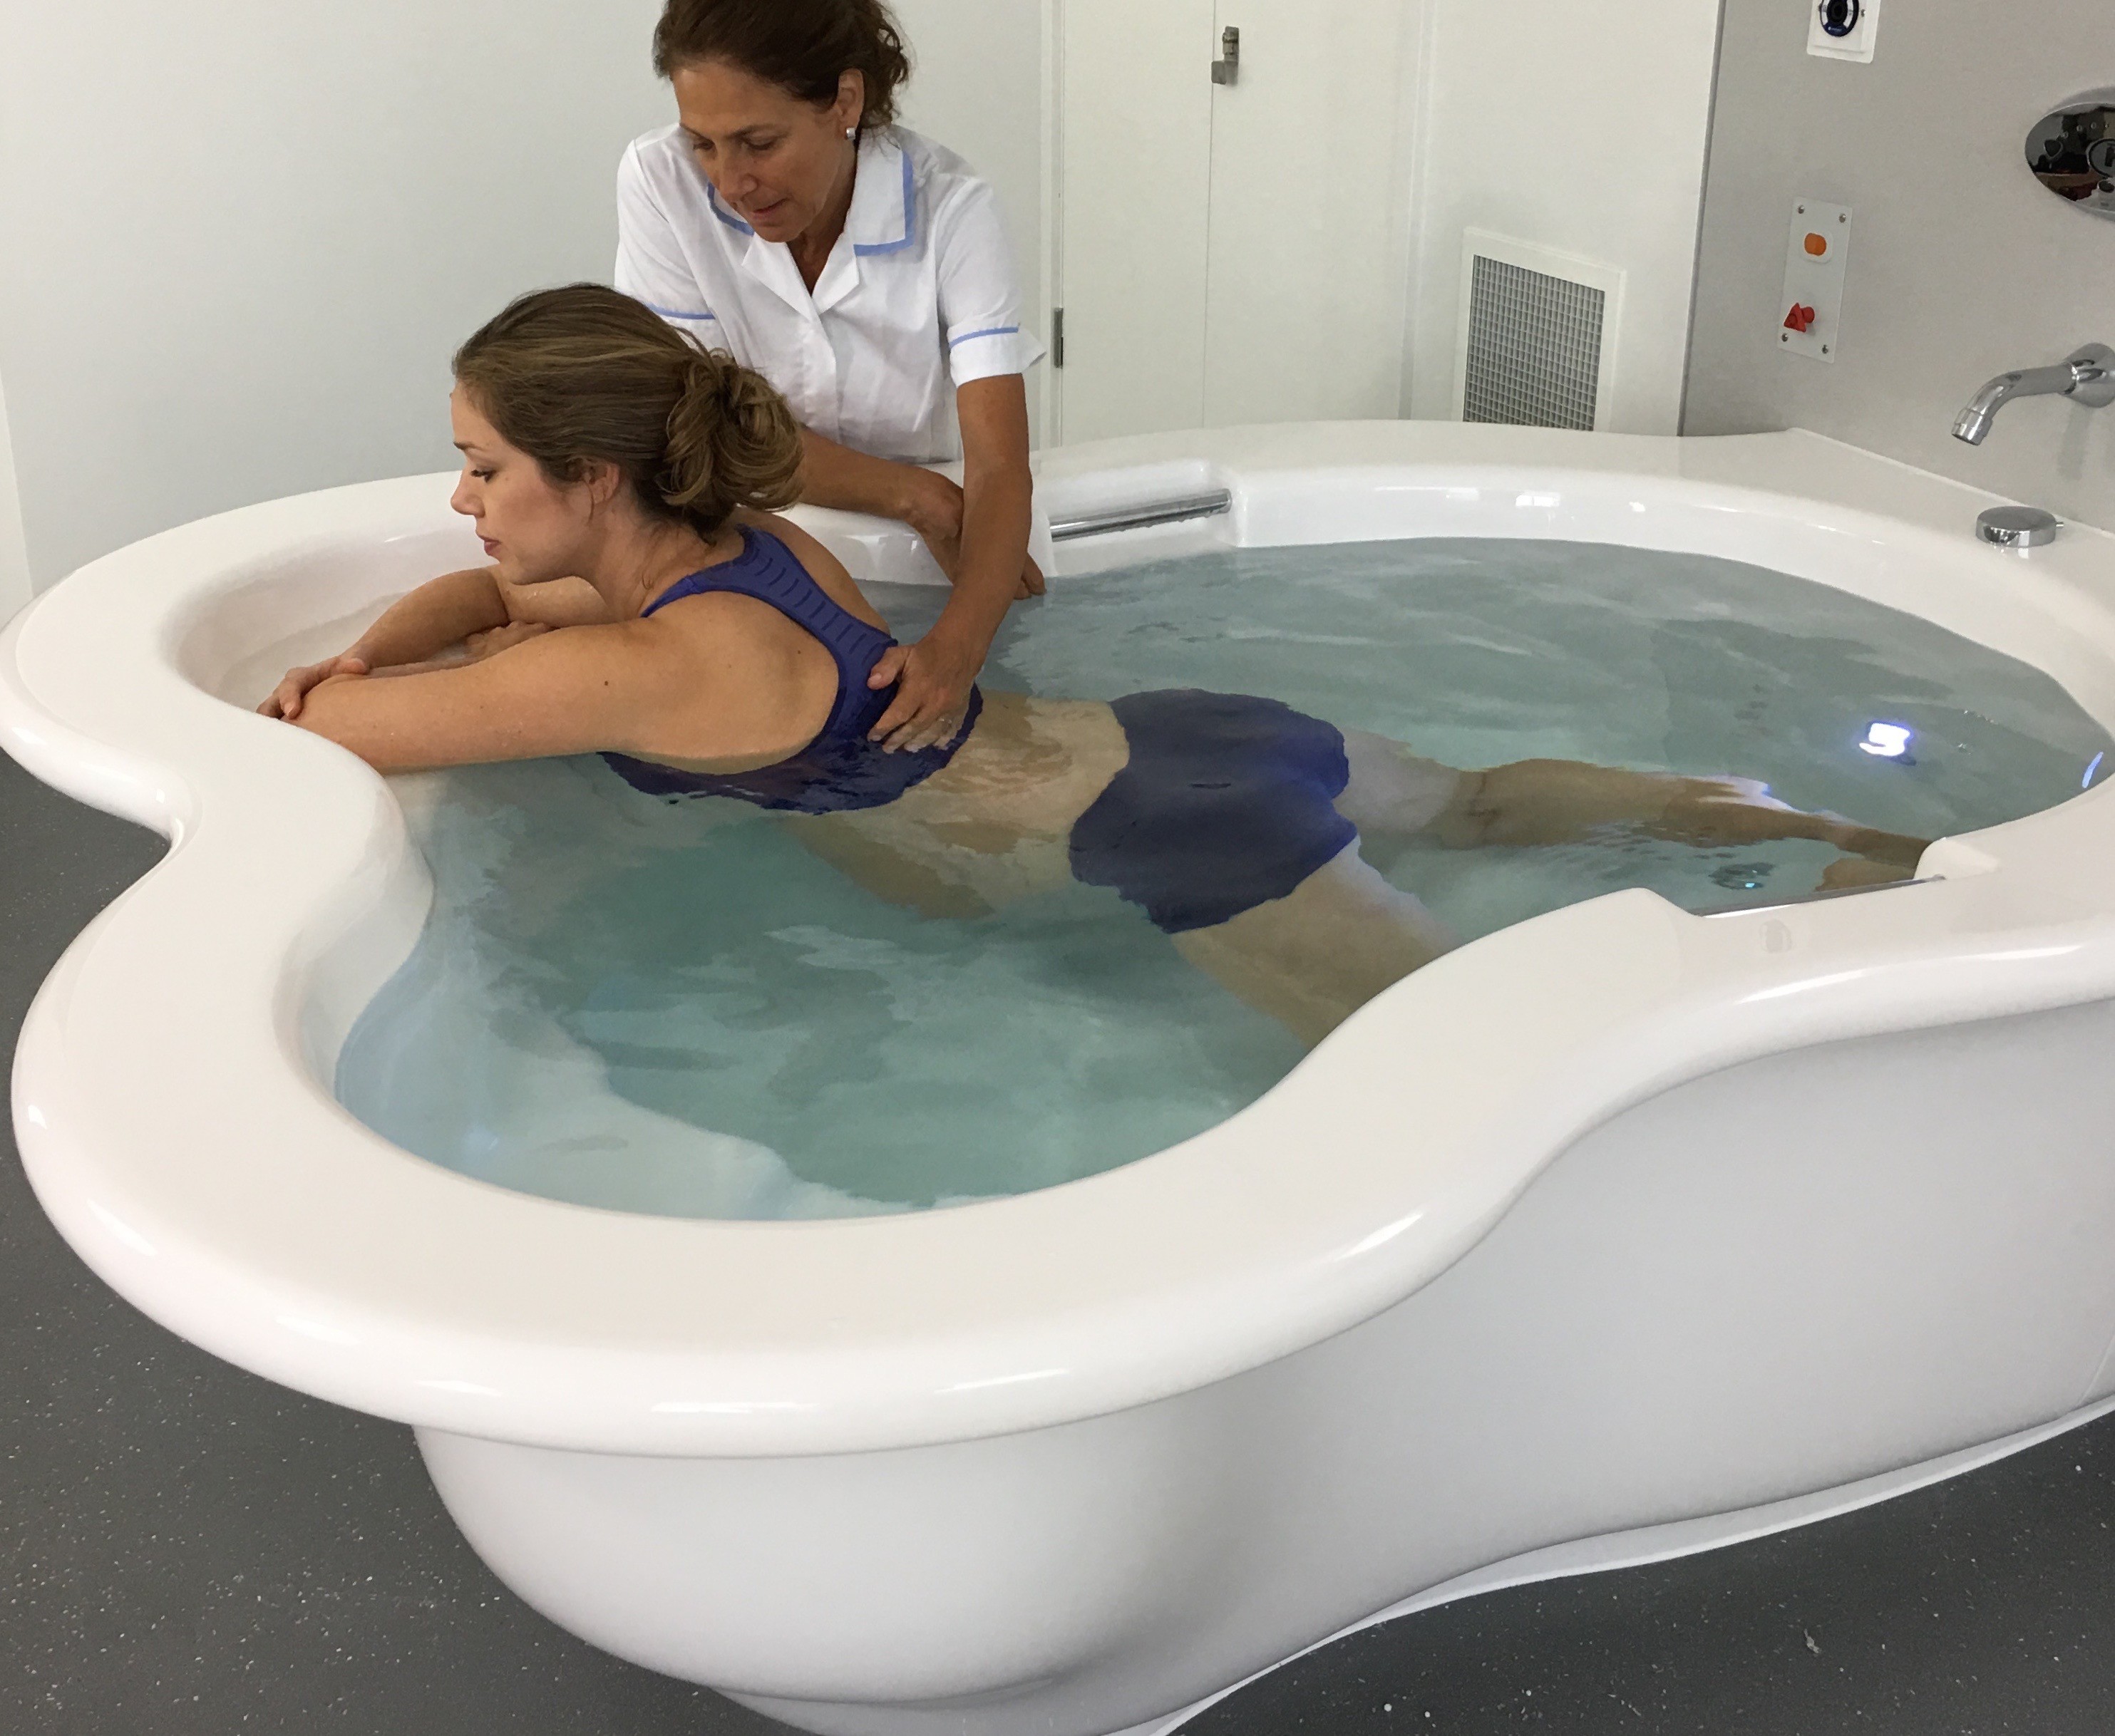
They can hold onto the recessed handgrips or use the wrap around, bullnose-shape rim for support as the they move around the pool to explore and find the most beneficial upright positions.

Features such as the Labour Support Seat, Safety Seat and Lumbar Support create additional possibilities for mothers to explore and find the most comfortable and beneficial positions.

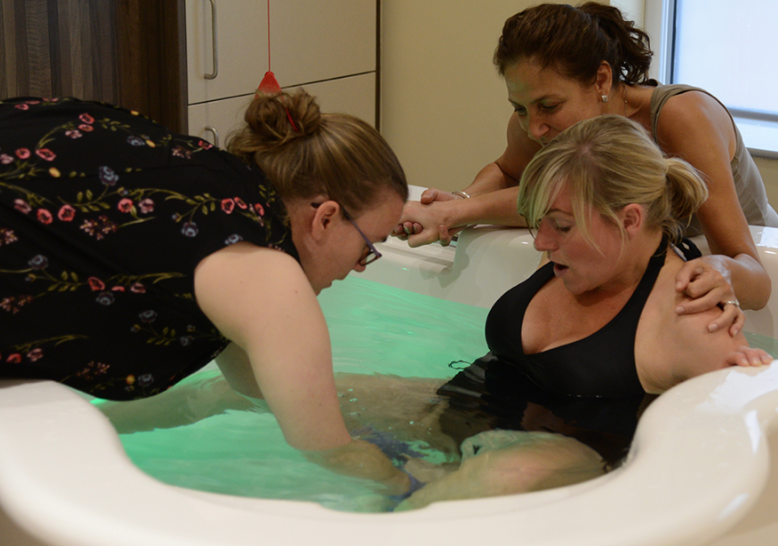
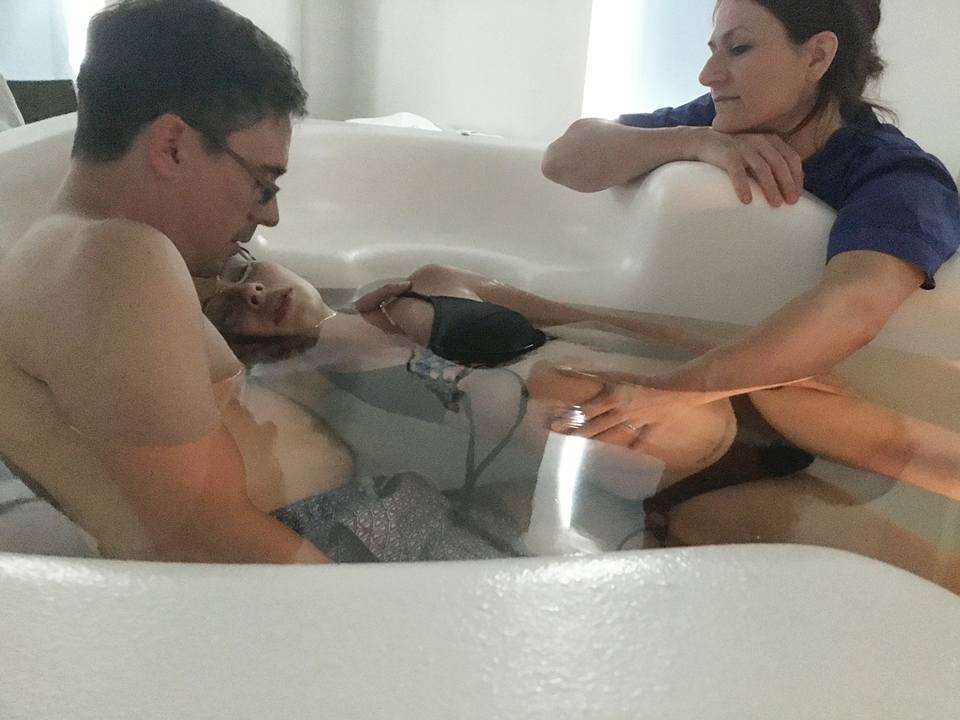
The design of our pools allows partners to sit in comfort and get really close to the mother.

The intimacy that couples experience with our pools is unique. No other pools allow partners to be so close without actually getting in the water.

The support thats provided both physically and emotionally has many benefits, and is key to helping mothers cope with pain and progress to experiencing physiological labour and natural birth.

Mothers simply tell us that, ‘they love our pools’.

They are actively encouraged to move freely and naturally.

They instinctively interact with the pool and find comfort and support wherever they are.

They benefit from complete freedom of movement and unparalleled comfort and therefore have greater probability of experiencing a physiological labour and having a natural active birth.

But, this is not the case with most water birth pools as renown author and educator Sheila Kitzinger OBE wrote in  ‘The clock, the bed, the chair’…

“Even a recent innovation, the birth pool, does not always permit free movement.

In theory, a pool allows a woman, supported by water, to move unencumbered.

Or so it might be thought.

Though published research often refers to mobility as an advantage of being in a pool, some pools are elaborate constructions with seats, handgrips and foot-rests, and movement in them is restricted.”

The pool dictates the position the mother should be in by placing her in a semi-recumbent posture with hand holds and foot rests to fix the arms and legs.

Mothers are positioned in the classic lying back with legs wide-open position but happen to be immersed in water.

The seats in these water birth pools are typically tilted backwards.

The mother is immobilised in a position with her pelvis tilted upwards resulting in her  pelvic outlet being up to 30% smaller.

This puts pressure on the sacrum which flexes upward, into a curved position that restricts the diameter of the pelvic outlet inhibiting the baby’s descent.

The birth canal is placed in an “uphill” orientation, forcing the mother to push upward against gravity to give birth to her  baby.

These seats and moulded fittings greatly reduce the space the mother has to move in and restricts her ability to use the positions most beneficial.

The benefits of labouring in water are largely negated.

The possibility of a physiological labour and natural birth is greatly reduced.”

Baths Are Simple Things. So Are Water Birth Pools. What Matters Most Is the Material They Are Made From

Why choice of material determines safety, usability, hygiene and over-all whole-life value

A bath is a simple object. It holds water. It needs to be comfortable, durable and easy to clean.

A water birth pool is also a simple object in principle.

But in a hospital maternity unit, that simplicity is deceptive.

A hospital water birth pool must cope with repeated filling and emptying, frequent cleaning and disinfection, temperature change, the weight of water and mother, and the everyday demands of a busy clinical environment.

In maternity settings, the pool is part of the care environment rather than a domestic bathroom product.

NICE guidance recognises birth in water as an option to consider and discuss with women and pregnant people, which makes the design and maintainability of the pool itself important to safe service provision. [1]

So when hospitals compare water birth pools, the most important question is not: “What does it look like?” It is: “What material is it made from?”

Because the material determines almost everything that matters: strength, hygiene, durability, comfort, wet-use performance, expected service life, sustainability and long-term value.

Simple products expose material quality

Complex products can sometimes hide mediocre materials behind technology and features. A water birth pool cannot.

Its performance depends directly on the integrity of its structure and surface. The material has to create a pool that is rigid, stable, smooth, non-porous, easy to clean and able to withstand years of professional use.

Those qualities cannot be added later. They have to be built into the product from the start.

A lower-cost pool may look perfectly acceptable when it is new. Most products do. The real test comes later.

How does the surface perform after years of use? How does it respond to repeated cleaning and disinfection? Does it remain rigid? Does it scratch, chip, stain or deteriorate? Can it be repaired? How soon will it need to be replaced?

That is where material quality reveals itself.

The surface is not cosmetic

In a hospital, the surface of a water birth pool is not just part of its appearance.

It is the part that comes into contact with the water, the mother and the hospital’s cleaning procedures. It must remain smooth, intact, accessible and inspectable for effective cleaning.

Healthcare building guidance repeatedly emphasises surfaces and sanitary assemblies that can be cleaned, maintained and used safely in clinical environments.

HBN 00-10 Part C deals specifically with sanitary assemblies, while HBN 00-02 provides design guidance for sanitary spaces in healthcare buildings. [2,3]

Damage matters.

Scratches, chips, cracks, joints and surface-mounted fittings can create areas that are harder to inspect and clean.

A pool may still look serviceable from a distance while its surface is becoming more difficult to maintain.

This is why hospitals should consider material quality and construction quality together.

A strong structure with a poor surface is not enough.

Nor is an attractive finish enough if the pool lacks rigidity or durability.

Seamless construction makes sense

Every unnecessary seam, joint, projection and attached fitting adds complexity.

Complexity means more edges to clean, more potential weak points and more places where water or contamination may collect.

A seamless, one-piece pool is simpler to inspect, simpler to maintain and easier to clean consistently.

It also allows handgrips, support areas and rounded rims to be formed into the pool itself rather than added afterwards.

This matters because simplicity, when it is properly engineered, is not merely an aesthetic quality.

It is a practical advantage.

The same principle is reflected in infection-control design guidance: smooth, cleanable and impervious surfaces are preferred in clinical areas, and surfaces should be accessible and resistant to the effects of cleaning agents. [4]

Ficore®, fibreglass and acrylic

Fibreglass

Fibreglass pools are generally made by applying layers of glass-fibre reinforcement and resin into a mould. The visible surface is usually a gelcoat.

This method can produce complex shapes relatively economically. However, the performance of the pool depends heavily on the quality of both the laminate and the gelcoat.

Over time, gelcoat surfaces can become scratched, chipped, stained or worn. If damage exposes the underlying structure, cleaning can become more difficult and specialist repair may be required.

Fibreglass may offer a lower initial price, but hospitals should look carefully at surface durability, structural consistency and long-term performance.

Acrylic

Acrylic is widely used for domestic baths. It is usually made by heating and vacuum-forming a sheet of acrylic, then reinforcing it from underneath.

Acrylic can provide a smooth and attractive finish. However, the forming process can stretch and thin the material, particularly around deeper curves and more complex shapes.

The strength of the finished product therefore depends not only on the acrylic surface but also on the quality of the reinforcement behind it.

Acrylic can also be susceptible to scratching and may be affected by inappropriate cleaning products or abrasive methods. For domestic use, that may be acceptable. For repeated hospital use, it deserves closer scrutiny.

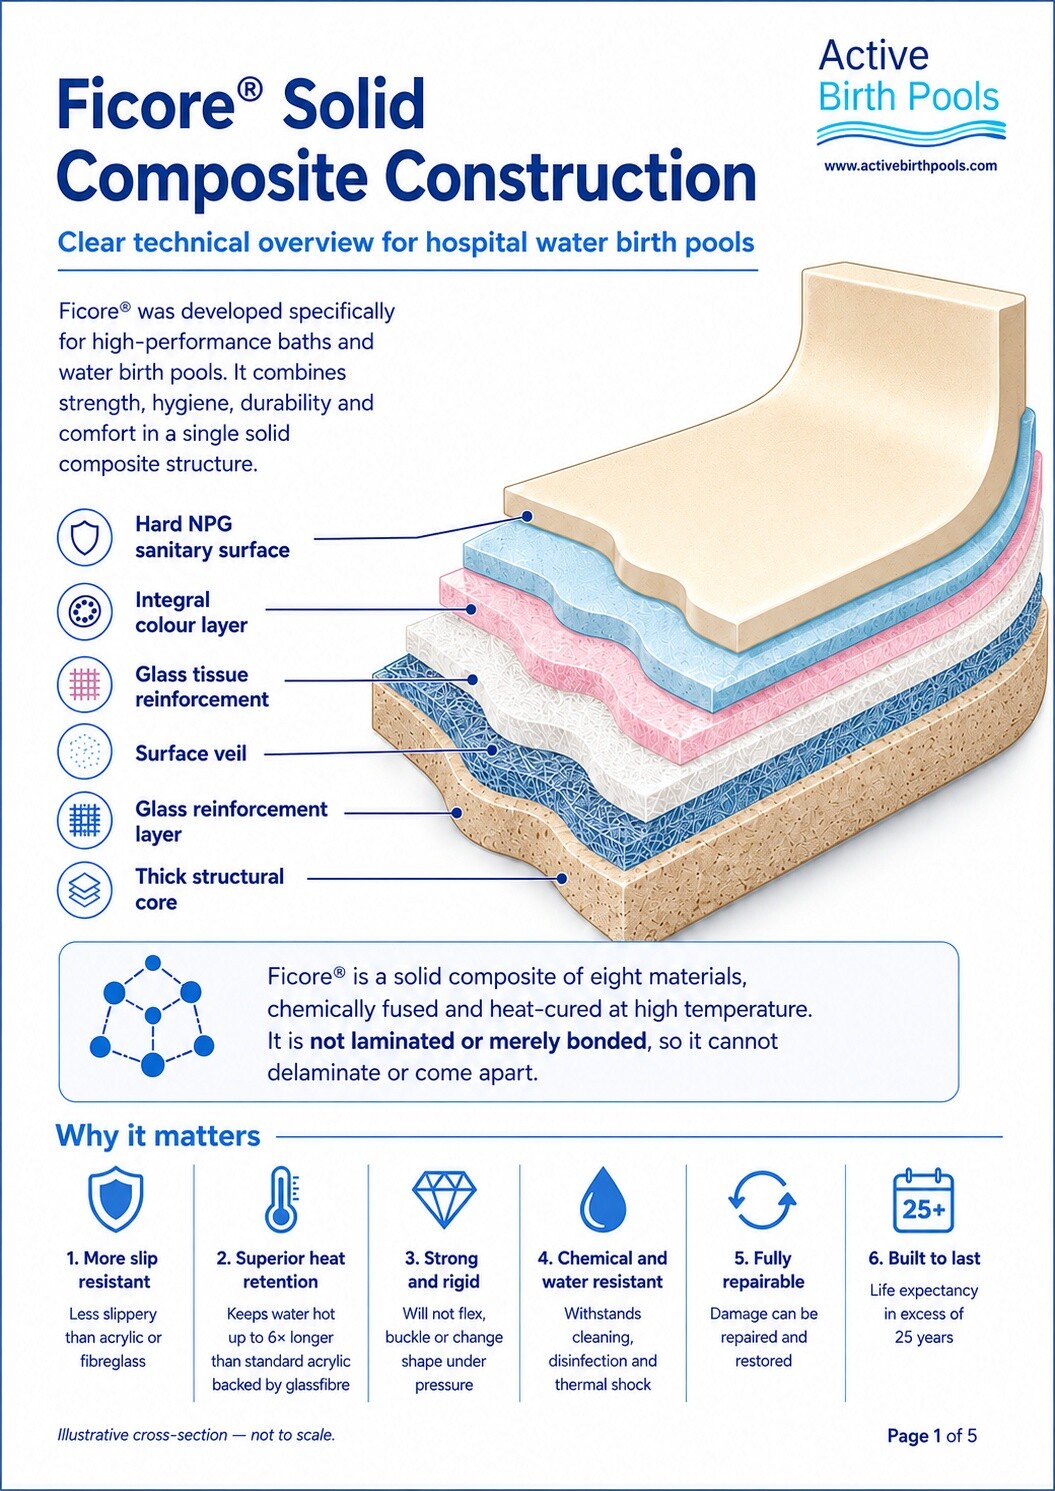
Ficore® Composite Resin

Ficore® is the specialist composite material used to manufacture Active Birth Pools.

Unlike acrylic, it is not a thin vacuum-formed sheet supported by a separate backing structure. Unlike conventional fibreglass, it does not rely on a thin decorative gelcoat over a laminate.

Ficore® is used to create a substantial, rigid, one-piece structure with a hard, smooth and non-porous surface. Active Birth Pools’ own Ficore® material specification describes it as a composite that is chemically fused and heat cured, rather than laminated or bonded. [12]

It is designed for repeated professional use in maternity environments where the pool must be filled, emptied, cleaned and disinfected again and again over many years.

It also enables important ergonomic features to be moulded directly into the pool, including handgrips, support areas and broad rounded rims. This produces a cleaner, stronger and more integrated design. [8,10]

Less slippery, more tactile and warm to the touch

Ficore® has a greater adhesive factor than fibreglass or acrylic. In practical terms, its surface is less slippery than fibreglass or acrylic and more slip resistant than those materials.

That does not mean Ficore® should be described as slip-proof. No wet surface should be. It does mean that Ficore® offers a more secure-feeling surface for mothers who need to move instinctively and change position during labour.

Ficore® also has a warmer and more tactile feel than fibreglass or acrylic.

Because a mother in labour is in close, continuous contact with the pool — leaning on the rim, bracing against the sides, resting her arms, or placing her hands and feet against the surface — this sensory difference matters.

Compared with the harder, colder and more plasticky feel often associated with fibreglass and acrylic, Ficore® feels more substantial, reassuring and comfortable to touch. Its smooth, solid surface gives the pool a softer tactile quality without compromising cleanability or durability.

Together, these qualities can make the pool feel less clinical and more inviting, helping mothers relax into the water and move with greater confidence. In a birth environment, small sensory differences can have a meaningful effect on how secure and supported the pool feels in use.

Durability matters far beyond the product itself

Durability is not just about whether a pool continues to look good. In a hospital, durability has clinical, operational and financial consequences.

When a fixed water birth pool needs replacing, the cost is not limited to the price of a new pool.

The room may need to be taken out of service. Plumbing must be disconnected. The old pool must be removed and disposed of. Floors, walls and seals may need making good. A new pool must be delivered, installed, connected and tested.

All of that takes time, money and planning. It may also temporarily reduce the number of birth rooms available to mothers.

A more durable pool reduces the likelihood of this disruption. That is why the service life of the material matters so much.

Ficore® water birth pools are engineered for a working life exceeding 25 years in demanding hospital environments. That longevity changes the value equation completely. [11,13]

Sustainability begins with longevity

Sustainability is often reduced to one question: “Can this material be recycled?” That matters, but it is not the whole picture.

A product that needs replacing every few years creates repeated environmental costs through raw materials, manufacturing, packaging, transport, installation and disposal.

A product that remains in service for decades spreads the environmental cost of its manufacture across a much longer working life.

That is one of the strongest sustainability arguments for Ficore®.

Its durability can reduce the need for replacement, which in turn can reduce material consumption, manufacturing demand, transport, packaging, installation work, disposal and disruption within the hospital.

There is also another important factor: repairability. Where appropriate, accidental damage to Ficore® can be professionally repaired. That may allow the pool to remain in service rather than being discarded and replaced.

A product that can be maintained and repaired is inherently more sustainable than one that becomes disposable when damaged. Durability and sustainability are not separate benefits. They are closely connected. [11]

The lifetime guarantee

Active Birth Pools offer a lifetime guarantee on Ficore® water birth pools, subject to the published terms and conditions.

That guarantee covers structural failure, loss of rigidity, leakage and surface breakdown. [9]

A guarantee of this scope is only possible when there is real confidence in the material, the design and the manufacturing process.

It is not simply a marketing statement. It reflects the belief that the pool has been made to endure.

The guarantee also makes an important point about value.

The higher initial cost of a Ficore® pool is not simply the price of a premium material.

It is the price of a product designed for long-term use, supported by a manufacturer prepared to stand behind its structural integrity.

Purchase price is not lifetime cost

Two water birth pools may perform the same basic function. One may cost less initially.

But if that pool deteriorates earlier, requires more maintenance, is harder to repair or must be replaced several times during the period in which a Ficore® pool remains operational, the lower purchase price may prove misleading.

The true cost of a water birth pool includes the original purchase, installation, maintenance, repair, downtime, replacement, removal, disposal and disruption to the maternity unit.

That is the difference between purchase price and whole-life value.

A higher-quality pool can cost more at the beginning and still cost less over its lifetime. Price is what the hospital pays on day one. Value is what the hospital receives over decades.

Why Active Birth Pools use Ficore®

Active Birth Pools use Ficore® because a hospital water birth pool must do more than look good when it is first installed.

It must remain strong, rigid, cleanable and dependable through years of repeated professional use. It must perform well when wet. It must support ergonomic design.

It must be repairable where appropriate. It must reduce the likelihood of premature replacement.

And it must provide hospitals with confidence that their investment will continue to deliver value over the long term.

Ficore® makes that possible.

Its quality allows Active Birth Pools to offer a lifetime guarantee.

Its durability supports a working life exceeding 25 years.

Its greater adhesive factor makes it less slippery than fibreglass or acrylic and more slip resistant than those materials, while its warmer, more tactile feel makes it more comfortable and reassuring to touch.

Its one-piece construction supports hygiene, strength and integrated ergonomic design.

The result is not simply a pool made from a different material. It is a pool designed to remain part of the maternity environment for decades.

Material matters most

A water birth pool does not need to be technologically complicated. It needs to be exceptionally well made.

Its safety, hygiene, comfort, durability, sustainability and long-term value all begin with the material.

A better material can produce a stronger pool, a more durable surface, a less slippery, warmer and more tactile wet-use experience, a longer service life, less waste and better whole-life value.

It can also give the manufacturer enough confidence to guarantee the product for life.

Baths are simple things. Water birth pools are simple things too. And precisely because they are simple, the material they are made from matters most.

References

  1. Intrapartum care. NICE guideline NG235. Recommendations, section 1.9: water birth. Published 29 September 2023; last reviewed 14 November 2025. https://www.nice.org.uk/guidance/ng235/chapter/Recommendations
  2. NHS England. Health Building Note 00-10: Part C – Sanitary assemblies. Department of Health / NHS Estates guidance. https://www.england.nhs.uk/wp-content/uploads/2021/05/HBN_00-10_Part_C_Final.pdf
  3. NHS England. Health Building Note 00-02: Sanitary spaces. Published 20 March 2013. https://www.england.nhs.uk/publication/designing-sanitary-spaces-like-bathrooms-hbn-00-02/
  4. NHS England. Health Building Note 00-09: Infection control in the built environment. Department of Health, 2013. https://www.england.nhs.uk/wp-content/uploads/2021/05/HBN_00-09_infection_control.pdf
  5. NHS England. Health Technical Memorandum 04-01: Safe water in healthcare premises. Published 20 May 2016; page updated 27 August 2024. https://www.england.nhs.uk/publication/safe-water-in-healthcare-premises-htm-04-01/
  6. NHS England. National Standards of Healthcare Cleanliness 2025. https://www.england.nhs.uk/long-read/national-standards-of-healthcare-cleanliness-2025/
  7. NHS England. National infection prevention and control manual (NIPCM) for England. https://www.england.nhs.uk/national-infection-prevention-and-control-manual-nipcm-for-england/
  8. Active Birth Pools. Superior Material Results in Superior Safety, Value and Performance: Why Ficore® Composite Is the Better Material for Hospital Water Birth Pools. 25 May 2026. https://activebirthpools.com/ficore-composite-water-birth-pool/
  9. Active Birth Pools. Terms and Conditions / Guarantee: Lifetime Warranty. https://activebirthpools.com/terms-conditions/
  10. Active Birth Pools. How to Choose a Water Birth Pool for a Hospital. https://activebirthpools.com/how-to-choose-a-water-birth-pool-for-a-hospital/
  11. Active Birth Pools. Active Birth Pools: Value and Sustainability. https://activebirthpools.com/active-birth-pools-value-and-sustainability/
  12. Design & Form / Active Birth Pools. FICORE® Composite: Active Birth Pools material specification. https://activebirthpools.com/wp-content/uploads/2022/11/Active-Birth-Pools-Material-specification-FICORE.pdf
  13. Active Birth Pools. Catalogue and Guide. https://activebirthpools.com/wp-content/uploads/2025/10/Catalogue-and-Guide.pdf

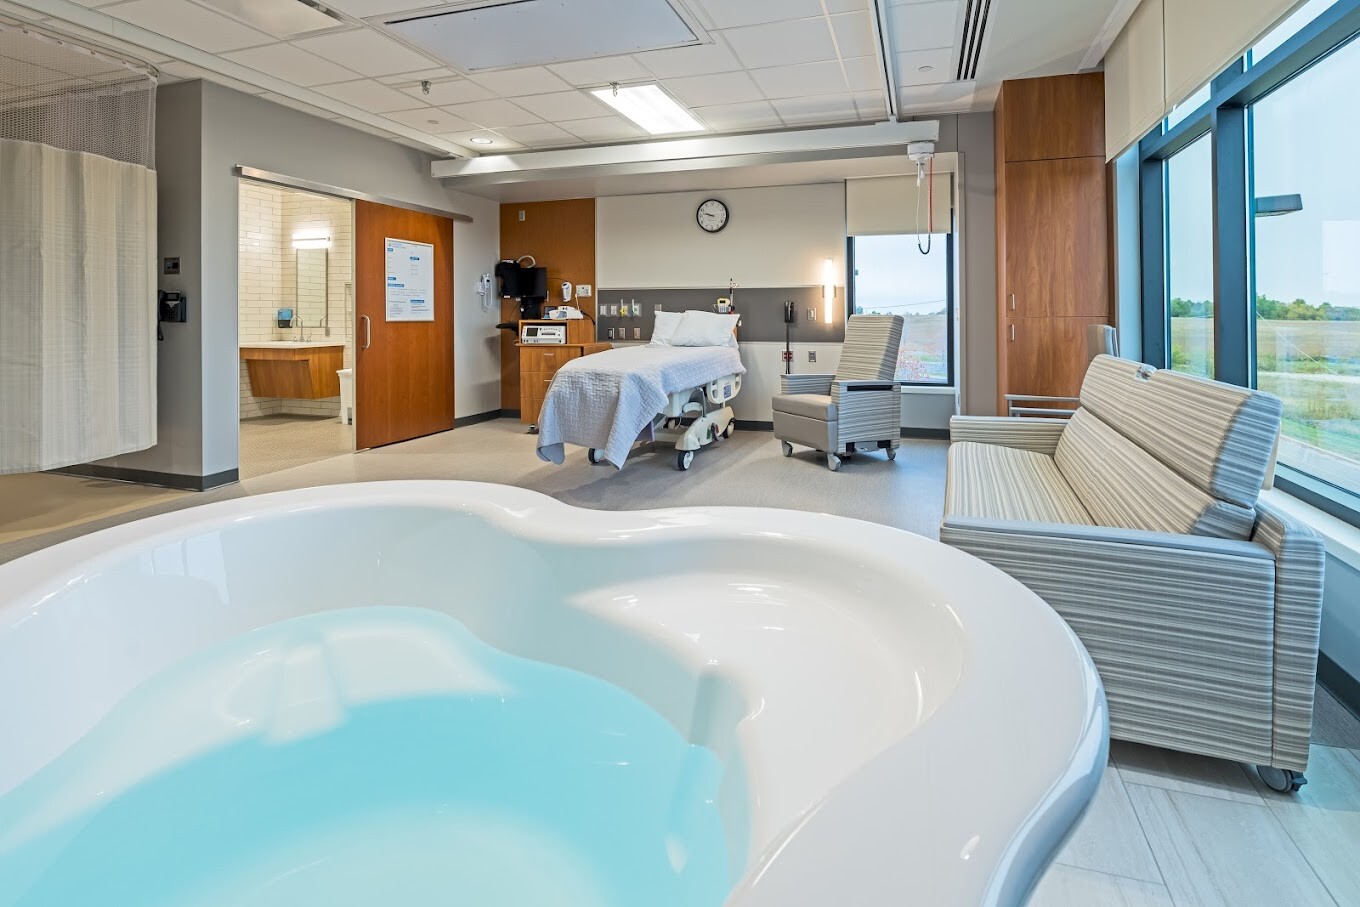
“Why Privacy, Warmth and Low Light Matter in the Birth Room”

Why the Room Mothers Give Birth in Should Be Like the Room They Made Love in

I first heard this idea from Michel Odent at the Active Birth Centre in London in the late 1980s.

It stayed with me because it made immediate, instinctive sense.

Birth and lovemaking are not the same experience, of course. But they are governed by some of the same deep physiological needs: privacy, safety, warmth, intimacy, low light, freedom from observation, and the ability to let go.

These are not luxuries. They are conditions that help the body work as nature intended.

Birth is affected by the environment

A woman in labour is exquisitely sensitive to her surroundings.

Bright lights, noise, interruptions, unfamiliar equipment, people coming and going, and the feeling of being watched can all disturb the quiet, instinctive state that supports physiological labour.

A calm, private, softly lit room can have the opposite effect. It helps the mother feel safe. It supports relaxation. It encourages the release of the natural hormones involved in labour, birth and bonding. [1,2]

This is why the birth room matters.

It is not simply a clinical space where birth happens. It is part of the birth process itself.

Privacy supports physiology

Michel Odent often spoke about the importance of protecting the labouring woman from unnecessary stimulation.

His central message was simple: when a woman feels private, safe and undisturbed, her body is more able to release oxytocin — the hormone that helps labour progress. When she feels anxious, exposed or scrutinised, stress hormones may rise and the normal rhythm of labour can be disrupted. [1]

This is one reason the comparison with the room where love is made is so powerful.

The ideal birth environment should not feel exposed, institutional or impersonal. It should feel intimate, protected and emotionally safe.

A homely room is not a cosmetic choice

Research into birth environments supports what midwives have long observed: the design of the room can influence how women move, how they feel, and how they experience labour.

Alternative or homelike birth settings have been associated with reduced use of some interventions, increased spontaneous vaginal birth, greater maternal satisfaction, and a more positive experience of care. [3,4]

Good birth room design is therefore not about decoration alone.

It is about creating a space that supports normal physiology, active birth, privacy, dignity and confidence.

The mother needs to move

The bed should not dominate the room.

When the bed is the central feature, it silently suggests that the mother should lie down and become a patient. But in physiological labour, the mother needs freedom to move, lean, kneel, squat, rest, change position and follow her body.

A well-designed birth room should make movement feel natural.

This is one of the reasons water birth pools are so valuable. Warm water gives the mother buoyancy, comfort and freedom. It allows her to change position easily, conserve energy, and remain active without feeling unsupported.

The room, the pool, the lighting, the furniture and the people present should all give the same message:

 – You are safe.
 – You are private.
 – You are free to move.
 – Your body knows what to do.

The details matter

A supportive birth environment should include:

soft, adjustable lighting
privacy from unnecessary observation
good acoustic control and reduced noise
comfortable room temperature
space for upright and forward-leaning positions
access to water for labour and birth
furniture that supports the mother and birth partner
minimal visual emphasis on clinical equipment
calm, respectful staff who protect the mother’s space

These features are not decorative extras. They help create the conditions in which physiological birth is more likely to unfold well. [5,6]

The birth room should invite confidence

When a woman enters the birth room, she should not feel that she has entered a theatre, a treatment bay or an emergency setting.

She should feel that she has entered a protected space prepared for one of the most intimate and powerful events of her life.

The room should help her soften, breathe, move, rest, focus inward and trust herself.

In that sense, the room you give birth in really should share something with the room you made love in.

– It should be private.

– It should be warm.

– It should feel safe.

– It should allow instinct to take over.

And it should honour the simple truth that birth, like lovemaking, belongs first to the body.

References

[1] Odent, M. (selected writings and lectures on physiological birth, privacy, oxytocin, dim light and homelike birth environments). See also The Guardian obituary summarising Odent’s work on protecting labour from unnecessary disturbance. https://www.theguardian.com/lifeandstyle/2025/sep/11/michel-odent-obituary

[2] World Health Organization. WHO recommendations: intrapartum care for a positive childbirth experience. Geneva: WHO, 2018. This guideline frames a positive childbirth experience around respectful, woman-centred care, dignity, privacy, emotional support, informed choice and safety. https://www.who.int/publications/i/item/9789241550215

[3] Hodnett, E. D., Downe, S., & Walsh, D. Alternative versus conventional institutional settings for birth. Cochrane Database of Systematic Reviews. The review reports that alternative institutional birth settings are associated with lower rates of some medical interventions and higher maternal satisfaction. https://www.cochrane.org/evidence/CD000012_alternative-versus-conventional-institutional-settings-birth

[4] Goldkuhl, L. et al. Impact of Birthing Room Design on Maternal Childbirth Experience: Results From the Room4Birth Randomized Trial. HERD: Health Environments Research & Design Journal, 2023. The Room4Birth trial found improved self-reported childbirth experience in a specially designed, more person-centred birthing room. https://pubmed.ncbi.nlm.nih.gov/36239523/

[5] Jenkinson, B., Josey, N., & Kruske, S. BirthSpace: An evidence-based guide to birth environment design. Queensland Centre for Mothers & Babies, 2014. The guide reviews evidence on design features that may reduce maternal stress and support physiological birth. https://espace.library.uq.edu.au/view/UQ:339451

[6] NHS England. Health Building Note 09-02: Maternity care facilities. This guidance covers planning and design considerations for maternity care facilities, including birthing rooms, privacy, dignity, daylight, acoustics and the clinical environment. https://www.england.nhs.uk/publication/maternity-care-facilities-planning-and-design-hbn-09-02/

A personal message from Founder
 and Director Keith Brainin

Dear Buyer, Midwife, Procurement Lead, Architect, Planner or Project Manager,

Choosing a water birth pool is an important decision. It should never be based on appearance or price alone.

A birth pool is a long-term clinical asset. It influences safety, hygiene, infection control, workflow, maternal comfort, midwife confidence, maintenance, installation and the overall quality of the birthing environment.

That is why proper due diligence is essential.

When you compare birth pools carefully – not simply by their initial cost, but by their design, materials, safety, usability, cleaning requirements, durability, installation process, service life and real-world performance – the right choice becomes clear.

Active Birth Pools are designed specifically for hospitals, birth centres and maternity units.

Every detail has been developed with the needs of mothers, midwives, infection control teams, manual handling teams, estates departments, procurement teams, architects and planners in mind.

When assessing any water birth pool, I encourage you to ask the questions that truly matter.

  • Is the pool easy and safe for women to enter and leave?
  • Does it support upright, active and instinctive positions during labour and birth?
  • Can midwives work comfortably around the pool without unnecessary strain?
  • Is the internal shape designed to support movement, buoyancy, rest and security?
  • Are the surfaces smooth, durable and easy to clean?
  • Are there unnecessary fittings, joints, seams or recesses that could make infection control more difficult?
  • Is the material robust enough for repeated clinical use?
  • Will the pool continue to look professional after years of service?
  • Is installation straightforward for estates teams and contractors?
  • Does the supplier have genuine experience in hospital and birth centre projects?
  • Will support be available before, during and after installation?

These are the questions that reveal the real value of a water birth pool.

A lower initial price can quickly become expensive if the product is difficult to clean, uncomfortable to use, awkward to install, poorly supported or not properly suited to the demands of a busy maternity unit.

Active Birth Pools are designed to avoid those compromises.

They combine elegant design with clinical practicality. They are comfortable for mothers, accessible for midwives, appropriate for healthcare environments and built to withstand the realities of repeated professional use.

For procurement teams, they offer long-term value.

For architects and planners, they provide a proven, attractive and practical solution for maternity room design.

For midwives, they support safe, confident, hands-on care.

For mothers, they create a calm, spacious and supportive environment for labour and birth.

Due diligence is not about choosing the cheapest option. It is about choosing the right one.

When you look closely at the design details, the materials, the user experience, the supplier’s expertise and the needs of everyone who will interact with the pool, Active Birth Pools stand apart.

I invite you to compare carefully because when you carry out proper due diligence, I believe you will see why Active Birth Pools are the logical choice.

I am always happy to help, answer questions or provide guidance at any stage of your project.

I look forward to hearing from you.

Best wishes,

Keith Brainin
Founder and Director
Active Birth Pools
Established 1987

Active Birth Pools Information Hub

Why Birth Pool Design Matters: Sheila Kitzinger’s Advice Still Holds True

“Even a recent innovation, the birth pool, does not always permit free movement.” — Sheila Kitzinger OBE

Sheila Kitzinger was one of the most influential voices in modern childbirth. As an author, social anthropologist and birth activist, she spent decades challenging the assumption that women should labour and give birth in positions chosen for the convenience of the institution rather than the needs of the body.

In her 2003 article The Clock, the Bed, the Chair, the Pool, Kitzinger made a point that remains highly relevant for maternity units today: a birth pool should support freedom of movement — but not every pool does. [1][2]

A birth pool should not become a bed filled with water

Water immersion is often valued because it can help women feel lighter, more private, more comfortable and more able to move instinctively during labour. Evidence reviews have found that labouring in water may reduce the use of epidural analgesia, without evidence of increased adverse outcomes for mothers or babies in the studies reviewed. [3]

NICE also recognises water immersion as an option for pain relief in labour, while noting that evidence on actual birth in water continues to be assessed separately. [4]

But the benefits of water depend on the environment created by the pool itself.

A poorly designed birth pool can reproduce the same problem Kitzinger identified in beds and chairs: it can direct the mother into a fixed, semi-recumbent position. Built-in seats, moulded supports, foot rests and rigid hand grips may look reassuring, but they can also restrict the very mobility that makes water valuable in labour.

The problem with fixed seating

When a pool contains a fixed seat, it subtly instructs the mother how to use it.

Instead of inviting upright, forward-leaning, kneeling, squatting or all-fours positions, it can encourage the mother to lean back with her legs forward. In effect, the pool becomes a reclined chair under water.

That matters because maternal position affects how freely the pelvis can move. Upright and flexible positions are associated with several possible advantages in the second stage of labour when compared with supine or lithotomy positions, although the evidence varies in certainty and each position has its own benefits and considerations. [5]

Research and reviews of maternal positioning also describe how positions such as squatting, kneeling and upright postures can increase or optimise pelvic outlet dimensions compared with more horizontal positions. [6][7]

The design question is therefore simple:

Does the pool allow the mother to move — or does it decide her position for her?

Water birth works best when the mother can respond to her body

Labour is dynamic. A woman may want to lean forward during one contraction, kneel during the next, rest between contractions, hold the pool edge, float, turn, squat, or change position quickly as the baby descends.

A pool designed around freedom of movement should make these changes easy.

It should provide:

  • open internal space, rather than restrictive moulded seating;
  • comfortable support points that can be used in different positions;
  • sufficient room for the mother to turn, kneel, lean, squat and rest;
  • safe access for the midwife without compromising the mother’s privacy;
  • a design that supports physiological labour rather than imposing a posture.

The best birth pool is not simply a vessel for warm water. It is part of the clinical environment, part of the mother’s support system, and part of the midwife’s working space.

Kitzinger’s insight is still a design standard

Sheila Kitzinger’s observation was not an objection to birth pools. It was a challenge to design them properly.

A pool that restricts movement can undermine the reasons for using water in the first place. A pool that supports movement can help create the conditions that many women seek from water birth: comfort, autonomy, privacy, buoyancy and the ability to follow instinctive positions in labour.

For hospitals, architects, maternity planners and midwives, this is the key lesson:

A birth pool should never dictate the birth position. It should make movement possible.

That principle has guided the development of Active Birth Pools for decades. Our designs avoid restrictive internal mouldings and fixed birth seats because freedom of movement is not an optional feature. It is central to the purpose of water birth.

When choosing a birth pool, ask not only how it looks, but how it behaves in use.

Does it support the mother?

Does it support the midwife?

Does it preserve space, mobility and dignity?

And most importantly:

Does it allow the woman in labour to move as her body needs?

References used

[1] Your current page quotes Kitzinger and frames the issue around how some pools restrict movement with seats, handgrips and footrests.
[2] Sheila Kitzinger’s article is listed as Sheila Kitzinger’s Letter from Europe: The Clock, the Bed, the Chair, the Pool, published in Birth in March 2003.
[3] Cochrane’s review on immersion in water during labour found that labouring in water may reduce epidural use and found no evidence of increased adverse outcomes in the reviewed studies.
[4] NICE’s intrapartum care guidance covers care during labour and includes recommendations relating to water immersion for pain relief.
[5] The Cochrane review on positions in the second stage of labour reports possible benefits of upright positions compared with supine positions for women without epidural anaesthesia, while also noting uncertainties and possible trade-offs.
[6] A 2019 review of common maternal positions notes, for example, that squatting can increase the pelvic outlet by approximately 20%.
[7] A 2021 MRI-based study reports that maternal birthing position may influence pelvic capacity, with upright positions potentially optimising capacity through freer pelvic movement.
[8] The 2022 systematic review and meta-analysis in BMJ Open found that water immersion during labour and birth was associated with several maternal benefits and no increase in adverse neonatal outcomes in the included evidence.

The History of Water Birth and the Development of Specially Designed Water Birth Pools

The history of water birth and the development of specialised water birth pools is a remarkable story of innovation and transformation in childbirth practices, driven by the insights of obstetrician Michel Odent and the design expertise of Keith Brainin.

Michel Odent’s groundbreaking work in the field of water birth began in the late 1970s at a state hospital near Paris.

Odent believed that childbirth had become overly medicalized and sought a more natural approach.

He introduced a pool in the hospital to ease the pain of labor, leading to some babies being born in the water.

Michel Odent with his pool in the maternity unit in Pithiviers, France

This innovative approach offered a more comfortable and less stressful birthing experience for mothers, with warm water helping to relax muscles, reduce stress, and enhance blood circulation.

Odent’s work demonstrated a reduction in the need for interventions like epidurals and episiotomies, aligning with many parents’ desires for a minimally invasive childbirth experience.

His observations and clinical experiences suggested that water birth provided a gentle transition for babies, mirroring the amniotic fluid environment​​.

“When asked about the history of birthing pools in hospitals, I mention the day when Keith Brainin realised that special bath tubs might be designed and commercialised to meet the needs of labouring women.”   Michel Odent

1989 – Sheila Kitzinger and Ethel Burns raise money to have the first specially designed water birth pool installed in an NHS Hospital at the John Radcliffe, Oxford

Building on Odent’s pioneering work, Keith Brainin, founder and director of Active Birth Pools, developed the world’s first specially designed water birth pools.

Starting in 1987, Brainin and his team focused on design, engineering, and manufacture to develop a water birth pool that excelled in quality, functionality, and durability.

Judges at the Building Better Healthcare Awards said that, “Active Birth Pools are the pinnacle of water birth pool design and development – an incomparable combination of design, materials and manufacturing” 

The Active Birth Pool was designed with ergonomic principles to support natural childbirth postures and provide comfort for the mother.

Features like extra-wide rims, integrated handrails, and specially designed labor support and safety seats were included to enhance safety and functionality.

The use of Ficore composite for construction ensured a harder, more chemical-resistant, and warm-to-the-touch surface that retains heat efficiently.

Keith Brainin with Sheena Byrom and midwives in the Lotus Birth Centre, Royal London Hospital 2018

Additionally, the pools were equipped with features like chromotherapy LED lighting and Bluetooth sound systems, allowing mothers to personalize their birthing environment.

These innovations in water birth pool design have significantly contributed to the safety, comfort, and natural approach to childbirth​​.

Both Michel Odent’s clinical insights and Keith Brainin’s design innovations have played a crucial role in transforming childbirth practices, emphasizing the importance of a natural, holistic approach to labor and delivery.

Their contributions have been instrumental in making water birth a viable and increasingly popular option for expectant mothers worldwide.

Fluid modernities: the birthing pool in late twentieth-century Britain

Active Birth Pools: Ethos and Values Statement

Active Birth Pools, established in 1987, has played a pioneering role in the use of water for labour and birth.

Their values and approach can be comprehensively understood by examining various aspects of their operations and products.

Innovation and Pioneering Spirit:

Active Birth Pools helped pioneer the use of water in labour and birth, working closely with midwives, mothers, obstetricians, and experts in infection control and manual handling.

This collaborative approach led to the development of the world’s first specially designed hospital-grade water birth pool, demonstrating their commitment to innovation and improvement in maternity care​​​​.

Safety, Value, and Performance:

The company emphasizes these core principles in their products.

They focus on producing birthing pools that are safe, offer great value, and perform exceptionally.

This focus is evident in their use of specialized materials like Ficore®, a proprietary material known for its durability, practicality, and safety features.

Ficore® pools, for example, retain heat efficiently and are resistant to bacteria and harsh disinfectants, ensuring high standards of hygiene​​​​​​.

Ergonomic Design:

Active Birth Pools employs evidence-based, user-centred ergonomic design principles.

Their pools are crafted to meet the comfort needs of both mothers and midwives, featuring designs that support various positions like sitting, kneeling, and squatting.

The wide rims of the pools allow midwives to rest comfortably, akin to sitting at a desk, which showcases their consideration for both the users’ comfort and practicality​​.

Customer Feedback and Endorsements:

The company values customer feedback and has received numerous positive testimonials from healthcare professionals and mothers.

These testimonials often highlight the comfort, ease of use, safety, and practicality of the pools, reflecting the company’s dedication to quality and user satisfaction​​.

Build Quality and Guarantee:

Active Birth Pools are hand-made to order in England by highly skilled craftsmen who take great pride in their work and are dedicated to excellence.

Active Birth Pools offers a lifetime guarantee on their water birth pools, which reflects their commitment to quality and durability.

This lifetime guarantee is a testament to the trust the company places in its design, materials and manufacturing processes.

Sustainability and Longevity:

Active Birth Pools places importance on sustainability.

Their pools have a life expectancy exceeding 25 years, making them a sustainable choice in comparison to other birthing pools with shorter lifespans.

This longevity not only provides value for money but also aligns with environmental sustainability principles​​.

Global Reach and Experience:

With a history spanning several decades, Active Birth Pools has supplied thousands of water birth pools worldwide.

Their extensive experience and knowledge in the field have made them a leading choice for hospitals and midwives globally.

This worldwide reach underlines their commitment to improving maternity care on a global scale​​.

In summary, Active Birth Pools’ values are centred around innovation, safety, ergonomic design, customer satisfaction, sustainability, and a global perspective in improving maternity care.

These values have guided their operations and product development, positioning them as a leader in the water birth pool market.

Winner – Building Better Healthcare Awards


Catalogue, information, videos and plans


The Design Philosophy Behind Active Birth Pools

In the world of industrial design, few principles have stood the test of time like those set forth by Dieter Rams. Among his “Ten Principles of Good Design,” one stands out for its quiet power and enduring relevance: “Good design is as little design as possible.”

This idea champions simplicity, honesty, and restraint—a philosophy that aligns perfectly with the ethos behind Active Birth Pools.

At Active Birth Pools, we design water birth pools not just as products, but as environments.

Our pools support one of life’s most natural and transformative events: childbirth.

This is not a time or place for gimmicks, clutter, or over-engineering.

Instead, our focus is on creating objects that are intuitive, purposeful, and deeply respectful of the experience they’re designed to serve.

Form Follows Function

When we say “as little design as possible,” we’re not talking about doing less.

We’re talking about doing only what’s essential—and doing it beautifully.

Every curve, surface, and contour of an Active Birth Pool is there for a reason.

There is no ornamentation, no unnecessary elements added to make a statement.

The pool’s elegant, organic form is shaped entirely by the physiological needs of women in labour and the practical requirements of midwives and clinical staff.

The result is a design that feels as natural as the process it supports.

It invites instinctive use and makes sense without explanation. This is design that understands the moment and quietly serves it.

Design That Disappears Into the Experience

Our goal is not to impress with visible complexity but to enable a powerful experience through simplicity.

When a woman enters an Active Birth Pool, she shouldn’t be thinking about the product; she should be free to focus entirely on herself and her baby.

The pool becomes part of the background—supportive, safe, unobtrusive.

It’s not a showpiece; it’s a silent partner in birth.

This kind of “invisible” design is only possible when everything unnecessary is stripped away.

What remains is the essence—a sculptural yet practical space that feels calm, grounded, and purposeful.

Integrated, Not Added-On

Good design does not bolt on features.

It integrates them.

At Active Birth Pools, every element—whether it’s a hand grip, step, or recessed area for medical access—is part of the form itself. There are no visible seams, fixtures, or accessories that suggest improvisation.

Everything flows together in a unified whole, contributing to both safety and aesthetics.

This seamless integration also supports infection control and long-term durability—crucial factors in hospital environments. But more than that, it’s a commitment to clarity and coherence in design.

Material Honesty and Tactile Comfort

We select materials not just for their performance but for their sensory qualities.

The finish of our pools is smooth, warm, and inviting to the touch. It’s easy to clean, gentle against the skin, and psychologically comforting—a key consideration for women in labour.

This is another way we practice “as little design as possible.”

We let the materials speak for themselves, choosing those that support the function and the feeling without the need for artificial textures or decorative layering.

Quiet Confidence in a Clinical World

In hospital settings, design can often be sterile or overbearing. By contrast, Active Birth Pools offer a quiet confidence. Their presence in a room is understated yet reassuring.

They don’t try to dominate the space; they help define it with dignity and grace.

This sense of calm and order is not just aesthetic—it’s functional. A well-designed pool reduces stress, supports natural movement, and allows midwives to work more effectively.

In this way, minimal design becomes a powerful tool for improving outcomes.

Conclusion: Less, But Better

At its core, “good design is as little design as possible” is about restraint, intention, and clarity.

It’s about stripping away the noise to let the true purpose shine through. This philosophy is not a style—it’s a discipline. And it’s one we practice daily at Active Birth Pools.

By honouring the principle of minimal design, we’ve created birth pools that are not only clinically superior and user-friendly, but emotionally supportive and deeply human.

In a world of overdesigned solutions, our pools stand as a quiet reminder: sometimes, the best design is the one you don’t notice at all.

The Benefits of Labouring in Water for Plus-Size Women

Childbirth is a transformative experience, and every expectant mother deserves the opportunity to have a comfortable and empowering birthing experience.

For plus-size women, the challenges of labour and delivery can sometimes be compounded by their body size.

However, one increasingly popular option that offers numerous benefits is labouring in water.

This article explores the advantages of water labour specifically for plus-size women, highlighting how it can enhance their birthing experience and overall well-being.

Buoyancy and Weight Support

One of the primary benefits of labouring in water for plus-size women is the buoyancy and weight support provided by the water.

As water buoys the body, it reduces the gravitational pull on joints and muscles, making it easier for women with larger body sizes to move and change positions during labour.

This buoyancy can alleviate the pressure on the pelvis and lower back, which is especially important for plus-size women who may already experience discomfort in these areas due to their size.

Reference: Geissbuehler V, Stein S, Eberhard J. Waterbirths compared with land births: an observational study of nine years. J Perinat Med. 2004;32(4):308-314.

Pain Relief and Relaxation

Warm water has a natural analgesic effect, helping to ease the pain and discomfort associated with labour contractions.

Plus-size women may have additional challenges due to their size, such as increased strain on the body, making the soothing properties of water particularly beneficial.

Water labour can promote relaxation, reduce stress, and create a calming environment, allowing mothers to focus on their breathing and coping techniques.

Reference: Harper SG, Lynch M, Vernacchio L. “Waterbirth: a retrospective comparative study of waterbirth and land birth outcomes.” Journal of Perinatal Education. 2002;11(2):22-29.

Improved Blood Circulation

For plus-size women, carrying extra weight can sometimes lead to issues with blood circulation and swelling in the extremities.

Immersing in warm water during labour can improve blood circulation by promoting vasodilation, which can help reduce swelling and alleviate discomfort.

Improved circulation can also support the baby’s oxygen supply during contractions.

Reference: Mollamahmutoglu L, Moraloğlu Ö, Ozyer S, et al. Warm showers as an alternative to warm sponges for the management of third stage of labour. European Journal of Obstetrics & Gynaecology and Reproductive Biology. 2002;101(1):19-23.

Enhanced Mobility and Positioning

Water labour allows for greater freedom of movement, which is especially valuable for plus-size women.

The buoyancy of water makes it easier to change positions, squat, or kneel, providing a range of options for comfort and facilitating the progress of labour.

The flexibility to find a comfortable position can be especially important for plus-size women, as it may help prevent complications and reduce the need for interventions.

Reference: Cluett ER, Burns E. Immersion in water in labour and birth. Cochrane Database of Systematic Reviews. 2009(2):CD000111.

Reduced Stress on Joints

The extra weight carried by plus-size women can put strain on their joints and ligaments, potentially leading to discomfort during labour.

Immersion in water can reduce the stress on joints, making movements smoother and less painful.

This can be particularly advantageous during the pushing phase of labour, as it allows for better control and coordination of efforts.

Reference: Zanetti-Daellenbach R, Tschudin S, Zhong X, et al. Influence of immersion in water on uterine contractility and cerebral oxygenation during the first stage of labour. Am J Obstet Gynecol. 2007;196(5):468.e1-8.

Conclusion

Laboring in water offers numerous benefits to plus-size women, enhancing their birthing experience and promoting a sense of empowerment during childbirth.

The buoyancy and weight support of water, coupled with its pain-relieving properties and improved circulation, make it a valuable option for managing the unique challenges associated with labouring while plus-size.

Ultimately, the decision to labour in water should be made in consultation with a healthcare provider, taking into account individual preferences and medical considerations.

Nevertheless, it’s clear that water labour can provide a positive and supportive environment for plus-size women, contributing to a more comfortable and fulfilling childbirth experience.

Active Birth Pools are designed to cater to the specific needs of plus-size women during childbirth

Our pools boast a spacious and ergonomic structure that allows for comfortable movement and positioning during labor.

Their wider dimensions and sturdy construction provide ample room and support for plus-size mothers, ensuring they can find comfortable birthing positions without constraints.

The carefully engineered design also takes into consideration accessibility, making it easier for expectant mothers of all sizes to enter and exit the pool safely.

These pools are equipped with features like grab rails and steps to ensure stability and ease of use.

In essence, the design of active birth pools prioritizes inclusivity and comfort, empowering plus-size women to have a positive and fulfilling birthing experience.

2016 – Launch of the Water Birth Safety Initiative

Hospitals in the United Kingdom began allowing women to use specially designed pools of water for labour and birth during the 1980’s.

The wide-spread popularity and acceptance of water birth pools as a standard part of the maternity care package necessitated the development of guidelines & regulations to define standards and ensure they’re met.

The United Kingdom Department of Health has published a panoply of water safety directives that apply to water birth pools.

Policies and recommendations set forth in the Water Birth Safety Initiative are based upon these publications.

The Water Birth Safety Initiative (WBSI) calls for development of international standards modelled on the UK’s so that women the world over can benefit from the use of water for labour and birth safeguarded from risk.

The WBSI calls for the implementation of stricter protocols and sets forth recommendations for equipment standards.

The guidelines set forth in the WBSI are intended to serve as a framework of standards for birth pool suppliers, hospitals and midwives to work with to establish  safe codes of practice.

Guidelines for Water Birth Pools Installed in Hospital

Water is more prone to bacteria growth after it leaves the public water distribution system and enters a building’s plumbing.

There it finds warmer temperatures, stagnation, and smaller pipes, valves and fittings.

Biofilm that forms on valves and fittings and pipe walls not only feeds bacteria but also protects them from the hot water and chlorine that typically would kill free-floating organisms.

Large systems with complex piping networks — like those found in hospitals, hotels and large apartment buildings — are especially prone to bacteria growth.15

Water Birth Pools that are installed in hospitals have the benefit of being maintained by staff to ensure that protocols are established, met and maintained.

Consideration and due diligence with regard to the prospective purchase of water birth pools and the assessment of pools already in use needs to be taken to ensure that the associated plumbing and electrical systems meet relevant safety standards.

The United Kingdom’s Department of Health and National Health Service has an exemplary safety record achieved by establishing rigorous sets of guidelines and regulations for the design, installation, use and maintenance (cleaning/disinfection) of water birth pools.

In the UK water birth pools are classed as a Category Fluid 5 water risk which represents a serious health hazard due to the concentration of pathogenic organisms, radioactive or very toxic substances, e.g. containing faecal material or other human waste; butchery or other animal waste or pathogens.

Water Birth Pools must be installed in compliance with water regulations as set forth in The Water Supply (Water Fittings) Regulations 1999.11

The 7 sins of water safety

To ensure high standards are met it is strongly advised that you do not use a water birth pool that has any of these features:

  1. Overflow drains
  2. Internal water inlets
  3. Hand-held showers
  4. Systems with flexible hoses or extended pipes
  5. Integral or secondary plumbing systems
  6. Any type of recirculating or pumped water systems such as whirlpool, jacuzzi, spa, bubbling, filtering etc
  7. Heating systems

1) Overflow drains

Overflow drains harbour bacteria and can serve as a conduit for cross infection.

Regulations are very clear on this point – overflow drains should not be installed on water birth pools as they constitute a constant infection control risk much more significant than the possible risk of damage due to water overflowing.11,12

Some digital taps on the market can be set for filling time thus obviating the risk of the pool overflowing.

2) Internal water inlets

Internal water inlets act in place of taps to fill the pool.

They are installed on the inside of the pool just above the water line and connected with pipework to a thermostatic valve.

If the water level rises there is a high risk of back flow enabling bacteria to enter the system creating a risk of cross infection.7

3) Handheld showers

Handheld showers present a significant infection control risk due to the fact that they can fall in the pool and be contaminated with bacteria that could breed and be passed on next time the shower is used.

Department of Health regulations clearly stipulate that handheld showers and bath/shower mixers are not installed for use with water birth pools. 13

Handheld showers present a Fluid Category 5 risk to the mains water supply.

It must not be possible to submerge the showerhead in the water due to risk of cross infection.

In order to comply with category 5 water regulations covering back siphonage, a class AUK3 air gap would be required, which generally prevents the use of handsets, unless there is a separate break tank installed in the hospital plumbing system.

4) Systems with flexible hoses or extended pipes

Systems that employ flexible piping, have branch pipes or hold stagnant water present a potential hazard and must not be used with water birth pools.

It is impossible to clean, disinfect or monitor these systems.

They have been proven to be a source of Legionella and Pseudomonas. 14

Weekly flushing recommendations recommended by the department of health cannot be executed with such systems, and the effectiveness of this cannot be monitored due to the inacessibility of the closed system.

5) Integral or secondary plumbing systems

Integral, secondary or proprietary plumbing systems are fitted to some water birth pools.

As these systems can employ flexible and non-flexible piping, overflow drains, handheld showers and are often pumped or recirculating they present a significant infection control risk and should be banned from use.

Regulations stipulate that water birth pools are filled from thermostatically controlled wall mounted mixer taps plumbed directly into the hospitals water supply with the minimum of pipework.

Not only do secondary or integral plumbing systems present unacceptable risks, they are impossible to clean, disinfect or monitor and therefore present an extremely high and unacceptable infection control risk.

They must not be present on pools used for labour and birth. 10

6) Recirculating or pumped water systems

Recirculating or pumped water systems such as whirlpool, jacuzzi, spa, bubbling, filtering etc. have the perfect environmental conditions to be a potential source for the growth of microorganisms, including legionella bacteria and must not be installed on water birth pools.

Water systems that are able produce aerosols represent the highest levels of risk.

Aerosols can be generated very easily when the water surface is broken -for example, by falling water droplets, splashing, or by bubbles breaking at the surface.

Once introduced to artificial water systems, Legionella can thrive in warm water (30 – 35 °C) and has been shown to be present on flexible seals and metal surfaces within plumbing systems used in domestic potable water supplies.

Inadequately maintained spa pools (birth pools with pumped or recirculating systems) provide ideal conditions to support the growth of legionellae and other microorganisms, which may then become aerosolised and subsequently inhaled.15


7) Heating systems

Heating systems for water birth pools are not necessary and present unacceptable infection control risks.7

There are two types of heating systems in use:

1. Recirculating system with a heat exchanger

Water is pumped out of the pool and through a heat exchanger and then flows back into the pool.

These systems present one of the highest infection control risks and should not be installed on a water birth pool under any circumstances. (covered by points 4, 5 and 6 above).

2. Electric heating systems

Similar to under floor heating found in homes do not present an infection control risk.

But, they do present an unacceptable health and safety risk and should therefore not be installed in water birth pools.

These systems consist of a network of cables embedded in the fabric of the birth pool that are attached to the power supply through a thermostat.

The heat is transmitted from the cables through the floor of the pool and then transferred to the water.

The inherent problem with these systems is that the water is relied on to take the heat away from the material.

If a woman remains motionless the heat becomes concentrated and a “hotspot” develops which can result in the woman being burned.

Recommendations

Plumbing for filling and emptying water birth pools should be simple, straight forward and kept to the minimum.

A set of taps (see below) mounted on the wall 15cm above the rim and a drainage system similar to that of a normal bath is all that is required.

Rim mounted taps present two areas of risk:

1. Women may hit their head on taps that are mounted on the rim of the pool causing injury.

In the throes of labour a woman is not as cognisant of her surroundings as she normally is.

She needs to be protected from the potential harm that could result from hitting her head or other part of her body on the spout.

2. Risk to the taps and pool caused by the labouring woman grabbing onto the spout for support could easily cause damage to the fitting or fabric of the pool.

Filling the birth pool

Water Birth Pools should be filled directly from the hospitals main water supply through a ¾ Thermostatic Mixing Valve (TMV).

To comply with UK National Health Service regulations the valve must have TMV3 approval for use in Healthcare and Commercial situations and certify that it conforms to the performance requirements of the Department of Health.16

To kill legionella and other bacteria, water in hospitals systems is heated to 60 – 80 °C.

Water temperature entering the birth pool should be limited by the TMV to 44 °C to prevent scalding.

The added benefit of using a TMV connected directly to the hospitals main water supply is that it can be set to automatically flush itself of stagnant water twice a day and be thermally disinfected periodically.

dsc_2965

The use of a TMV ensures a safe water supply.

Digital thermostatic mixing valves with enhanced thermal performance that incorporate these features are ideal:

1) Programmable control to accurately mix and maintain the temperature of the water flowing into the birth pool and limit the temperature of the water to 44 °C to prevent scalding.17

2) Programmable fill duration to fill the pool to the desired depth and then turn off.

This is important as water birth pools are not allowed to have overflow drains installed and this feature will prevent the pool from overflowing when unattended.

3) Programmable duty flushing to ensure that water does not stagnate within the tap and associated pipe work, effectively controlling the multiplication of legionella & other bacteria in infrequently used outlets.

Flushing duration is in line with HSE L8 recommendations.18

4) Programmable high-temperature thermal disinfection to destroy the proteins in viruses and bacteria and render them as dead or inert.

Thermal disinfection works by achieving a moist heat which is set at a specific temperature for a set amount of time.

Viruses and bacteria are very sensitive to heat and they will die if exposed to higher temperatures. 19

Emptying the Pool

Water from a birth pool needs to be treated as Fluid category 5 waste representing a serious health hazard due to the concentration of pathogenic organisms derived from fecal material or other human waste and emptied directly into the hospital’s waste water system.20

The pipework needs to have a trap or U bend fit as close to the waste/drain as possible.

The drainage fitting or waste should seal neatly into the drain.

The drainage fitting should be cleaned and flushed through with disinfectant and then dried as part of the cleaning protocol.

The waste should be kept closed when the pool is not in use.

There should be NO flexible pipe used in the drainage pipework.21

The waste should be remotely operated (i.e. pop up waste with rim mounted control) and of the best quality, preferably high-grade brass, to resist the corrosive action of chlorides and other disinfectants.

DSC_2915

End notes

The Water Birth Safety Initiative was conceived by Keith Brainin to motivate and enable birth pool suppliers and health care professionals to raise standards and implement protocols to make water birth safe.

References

[1] Healio – Infectious Disease News. (2014, December 26). Legionellosis death after water birth sparks call for stricter infection control protocols. http://www.healio.com/infectious-disease/practice management/news/online/%7Bfe352169-755d-4d21-9bb2-abb8ae209f89%7D/legionellosis-death-after-water-birth-sparks-call-for-stricter-infection-control-protocols

[2] Inquisitr. (2015, January 16). Oregon Water Birth Leaves Baby Disabled, Lawsuit Wants Labor Options Banned. http://www.inquisitr.com/1761136/oregon-water-birth-leaves-baby-disabled-lawsuits-wants-labor-options-banned/

[3] GOV.UK. Alert after Legionnaires’ disease case in baby, 2014. https://www.gov.uk/government/news/alert-after-legionnaires-disease-case-in-baby

[4] The Guardian. Legionnaires’ disease in baby is linked to heated birthing pool, June 17, 2014.http://www.theguardian.com/society/2014/jun/17/legionnaires-disease-heated-birthing-pool-baby-public-health

[5] Guidance from the  Water Regulations Advisory Scheme (WRAS) https://www.wras.co.uk/consumers/advice_for_consumers/what_are_the_water_regulations_/

[6] M.W. LeChevallier, 2003 World Health Organization (WHO). Conditions favouring coliform and HPC bacterial growth in drinking- water and on water contact surfaces. Heterotrophic Plate Counts and Drinking-water Safety. Edited by J. Bartram, J. Cotruvo, M. Exner, C. Fricker, A. Glasmacher. Published by IWA Publishing, London, UK. ISBN: 1 84339 025 6.

[7] www.gov.uk. Public Health England advice on home birthing pools, 2014.  https://www.gov.uk/government/news/public-health-england-advice-on-home-birthing-pools

[8] Health and Safety Executive. (2013). Legionnaires’ disease: Technical guidance [3.4], 2013. http://www.hse.gov.uk/pubns/priced/hsg274part3.pdf

[9] United Lincolnshire Hospitals NHS Trust UK. Cleaning, Disinfection and Sterilization Guidelines for Re-Usable Medical Devices 2010.
http://www.activebirthpools.com/wp-content/uploads/2014/05/Lincolnshire-CLEANING-DISINFECTION-AND-STERILIZATION-GUIDELINES-FOR-RE-USABLE-MEDICAL-DEVICES.pdf

[10] http://www.eurosurveillance.org. Case of legionnaires’ disease in a neonate following an home birth in a heated birthing pool. England, June 2014 http://www.eurosurveillance.org/ViewArticle.aspx?ArticleId=20857

[11] Water Regulations Advisory Scheme (WRAS). Fluid Categories. https://www.wras.co.uk/consumers/resources/glossary/fluid_categories/

[12] WHBN 00-10 Welsh Health Building Note. Part C: Sanitary assemblies2014, http://www.wales.nhs.uk/sites3/documents/254/WHBN%2000-10%20Part%20C.pdf

[13] Department of Health, Children, young people and maternity services. Health Building Note 09-02: Maternity care facilities, 2009.
https://www.gov.uk/government/uploads/system/uploads/attachment_data/file/147876/HBN_09-02_Final.pdf

[14] Freije, Matthew R. Some waterborne bacteria are tough, 2010. http://www.watertechonline.com/articles/some-waterborne-bacteria-are-tough

[15] Woolnough, Kevin. Legionella Expert Calls for Greater Vigilance, 2014. http://www.eurofins.co.uk/news-archive/legionella-expert-calls-for-greater-vigilance.aspx

[16] BEAMA. TMV Standards and regulations, 2013. http://www.beama.org.uk/en/product-areas/heating-hot-water–air-movement/thermostatic-mixing-valves/tmva-faqs-on-thermostatic-mixing-valves/tmv-standards-and-regulations.cfm

[17] Health and Safety Executive. Managing the risks from hot water and surfaces in health and social care, 2012. http://www.hse.gov.uk/pubns/hsis6.pdf

[18] Health and Safety Executive. Legionnaires’ disease The control of legionella bacteria in water systems, 2013. http://www.hse.gov.uk/pubns/priced/l8.pdf

[19] Health and Safety Executive. Managing legionella in hot and cold water systems. http://www.hse.gov.uk/healthservices/legionella.htm

[20] SMS Environmental – the water experts. Fluid Categories. http://www.sms-environmental.co.uk/fluid_categories.html.

[21] Nottingham University Hospitals NHS Trust. Legionella Management and Control Procedures, 2014.

Bibliography

  • Ashford and St. Peter’s Hospitals, Women’s Health and Paediatrics Division (Abbey Birth Centre). Operational Policy and Clinical Guide, 2014.
  • BASINGSTOKE AND NORTH HAMPSHIRE NHS FOUNDATION TRUST . CLEANING, DISINFECTION AND STERILISATION POLICY. Prod. Helen Campbell. BASINGSTOKE AND NORTH HAMPSHIRE, BASINGSTOKE AND NORTH HAMPSHIRE, 2010.
  • BEAMA. TMV Standards and regulations. 2013. http://www.beama.org.uk/en/product-areas/heating-hot-water–air-movement/thermostatic-mixing-valves/tmva-faqs-on-thermostatic-mixing-valves/tmv-standards-and-regulations.cfm (accessed 2014 йил 24-09).
  • Buckinghamshire Healthcare NHS Trust. Water birth and use of water in labour guideline. Prod. Miss G Tasker and Audrey Warren. 2013.
  •  Dekker, Rebecca. “Evidence on the Safety of Water Birth.” http://evidencebasedbirth.com/. 2014. http://evidencebasedbirth.com/waterbirth/ (accessed 2014 10-09).
  • Department for Environment, Food and Rural Affairs. Water Supply (Water Fittings) Regulations 1999 Guidance Document relating to Schedule 1: Fluid Categories and Schedule 2: Requirements For Water Fittings. 1999. http://archive.defra.gov.uk/environment/quality/water/industry/wsregs99/documents/waterregs99-guidance.pdf.
  • Department of Health. Children, young people and maternity services Health Building Note 09-02: Maternity care facilities. 2009.

—. “Health Building Note 00-09: Infection control in the built environment.” www.gov.uk. 2002. https://www.gov.uk/government/uploads/system/uploads/attachment_data/file/170705/HBN_00-09_infection_control.pdf (accessed 2014 6-12).

—. “Health Technical Memorandum 64: Sanitary assemblies.”  2006. http://www.wales.nhs.uk/sites3/documents/254/HTM%2064%203rded2006.pdf (accessed 2014 10).

—. “Water systems Health Technical Memorandum 04-01: Addendum” .2013. https://www.gov.uk/government/uploads/system/uploads/attachment_data/file/140105/Health_Technical_Memorandum_04-01_Addendum.pdf (accessed 01 2014-10).

 —. “Water systems Health Technical Memorandum 04-01: The control of Legionella , hygiene, “safe” hot water, cold water and drinking water systems”. 2006.

  • DH, Estates & facilities. Water systems Health Technical Memorandum 04-01: Addendum . Department of Health, Department of Health.
  • Elizabeth R Cluett, Ethel Burns. Immersion in water in labour and birth. 2009.http://onlinelibrary.wiley.com/doi/10.1002/14651858.CD000111.pub3/abstract (accessed 2013 13-05).
  • Elyse Fritschel, Kay Sanyal, Heidi Threadgill, and Diana Cervantes. Emerging Infectious Diseases.CDC. Centers for Disease Control and Prevention. CDC. 2014. http://wwwnc.cdc.gov/eid/article/21/1/14-0846_article (accessed 2015 5-January).
  • Freije, Matthew R. Some waterborne bacteria are tough . 2010. http://www.watertechonline.com/articles/some-waterborne-bacteria-are-tough (accessed 2015 20-01).
  • GOV.UK. Alert after Legionnaires’ disease case in baby. 2014. https://www.gov.uk/government/news/alert-after-legionnaires-disease-case-in-baby (accessed 2014 3-12).
  • GOV.UK. Public Health England advice on home birthing pools. 2014. https://www.gov.uk/government/news/public-health-england-advice-on-home-birthing-pools (accessed 2014 03-August).
  • Healio – Infectious Disease News. Legionellosis death after water birth sparks call for stricter infection control protocols. 2014. http://www.healio.com/infectious-disease/practice-management/news/online/%7Bfe352169-755d-4d21-9bb2-abb8ae209f89%7D/legionellosis-death-after-water-birth-sparks-call-for-stricter-infection-control-protocols (accessed 2015 07-01).
  • Health and Safety Executive. Legionnaires’ disease The control of legionella bacteria in water systems. 2013. (accessed 2014 07-07).

—. “Legionnaires’ disease: Technical guidance.”  2013. http://www.hse.gov.uk/pubns/priced/hsg274part3.pdf (accessed 2014 20-10).

—. Managing legionella in hot and cold water systems. http://www.hse.gov.uk/healthservices/legionella.htm (accessed 2015 07-01).

—. “Managing the risks from hot water and surfaces in health and social care.”  2012. http://www.hse.gov.uk/pubns/hsis6.pdf (accessed 2014 20-11).

  •  Health Facilities Scotland. Consultation draft of SHTM 04-01 Water Safety for Healthcare Premises Part G: Operational Procedures and exemplar Written Scheme 2013. Health Facilities Scotland.
  •  Inquisitr. Oregon Water Birth Leaves Baby Disabled, Lawsuit Wants Labor Options Banned. 2015.http://www.inquisitr.com/1761136/oregon-water-birth-leaves-baby-disabled-lawsuits-wants-labor-options-banned/ (accessed 2015 16-01).
  •  Laura Franzin, Carlo Scolfaro, Daniela Cabodi, Mariangela Valera, and Pier Angelo Tovo. Legionella pneumophila Pneumonia in a Newborn after Water Birth: A New Mode of TransmissionOxford Journals, November 2001: 104.
  • Legionella Control. Birthing Pool Death Linked To Legionnaires disease. https://legionellacontrol.com/blog/166-birthing-pool-death-linked-to-legionnaires-disease (accessed 2014 27-11).
  •  Legislation.gov.uk. The Water Supply (Water Fittings) Regulations 1999.The National Archives. 1999. http://www.legislation.gov.uk/uksi/1999/1148/contents/made (accessed 2015 05-01).
  •  M.W. LeChevallier, World Health Organisation. Conditions favouring coliform and HPC bacterial growth in drinkingwater and on water contact surfaces . 2003.
  •  N Phin, T Cresswell, F Parry-Ford on behalf of the Incident Control Team. CASE OF LEGIONNAIRES’ DISEASE IN A NEONATE FOLLOWING A HOME BIRTH IN A HEATED BIRTHING POOL, ENGLAND, JUNE 2014.http://www.eurosurveillance.org. 2014. http://www.eurosurveillance.org/ViewArticle.aspx?ArticleId=20857 (accessed 2015 10-01).
  •  Nottingham University Hospitals. LEGIONELLA MANAGEMENT AND CONTROL PROCEDURES. May 8, 2014.
  • Rosanna A. Zanetti-Daellenbach, Sibil Tschudin, Xiao Yan Zhong, Wolfgang Holzgreve, Olav Lapaire, Irene Ho ̈sli. Maternal and neonatal infections and obstetrical outcome in water birth . Prod. Women’s University Hospital Basel. Spitalstrasse, Basel: European Journal of Obstetrics & Gynecology and Reproductive Biology , 2006 28-August.
  • SMS Environmental – the water experts. Fluid Categories. http://www.sms-environmental.co.uk/fluid_categories.html.
  • Takuhito Nagai, Hisanori Sobajima, and Mitsuji Iwasa. A fatal newborn case of Legionella pneumophila pneumonia occurring after water birth in a bathtub with an all day circulating system, June 1999 – Nagoya City.http://idsc.nih.go.jp/. 2000. http://idsc.nih.go.jp/iasr/21/247/de2474.html (accessed 2014 17-06).
  • Takuhito Nagai, Hisanori Sobajima, Mitsuji Iwasa, Toyonori Tsuzuki, Fumiaki Kura, Junko Amemura-Maekawa, and Haruo Watanabe. Neonatal Sudden Death Due to Legionella Pneumonia Associated with Water Birth in a Domestic Spa Bath. 2002.http://www.ncbi.nlm.nih.gov/pmc/articles/PMC154682/ (accessed 2014 3-12).
  • The Guardian. Legionnaires’ disease in baby is linked to heated birthing pool . 2014. http://www.theguardian.com/society/2014/jun/17/legionnaires-disease-heated-birthing-pool-baby-public-health (accessed 2014 18-June).
  • U.S. Department of Health and Human Services Centers for Disease Control and Prevention (CDC) Atlanta, GA 30333. Guidelines for Environmental Infection Control in Health-Care Facilities . 2003.
  • UNITED LINCOLNSHIRE HOSPITALS NHS TRUST. CLEANING, DISINFECTION AND STERILIZATION GUIDELINES FOR RE-USABLE MEDICAL DEVICES. Lincolnshire, 2010 January.
  • Water Regulations Advisory Scheme. Fluid Categories . https://www.wras.co.uk/consumers/resources/glossary/fluid_categories/ (accessed 2014 3-12).
  • which.co.uk. Having a water birth and using birth pools. http://www.which.co.uk/birth-choice/articles/using-water-in-labour.
  • Woolnough, Kevin. Legionella Expert Calls for Greater Vigilance. http://www.eurofins.co.uk/news-archive/legionella-expert-calls-for-greater-vigilance.aspx (accessed 2015 17-01).

Please feel free to distribute and share this document crediting  © K. D. Brainin (Active Birth Pools) 2015

Design Guide – Birthing Pool Units Hospital Development Magazine November 1993

By Janet Balaskas and Keith Brainin

Hospital Development Magazine November 1993

Fluid modernities: the birthing pool in late twentieth-century Britain

Improving Birthing Pool Design: Case Study 18 – Chartered Institute of Ergonomics & Human Factors

The history of water birth and development of specialised water birth pools

The Warm Embrace: How Warm Water in Water Birth Pools Facilitates the Release of Oxytocin

The use of water birth pools has gained popularity in recent years as expectant mothers seek alternatives that enhance the natural birthing experience.

One of the key factors contributing to the success of water births is the warm water in the birthing pool, creating an environment that encourages the release of oxytocin.

Often referred to as the “love hormone” or “bonding hormone,” oxytocin plays a crucial role in the progression of labour and the overall well-being of both mother and baby.

Understanding Oxytocin:

Oxytocin, produced by the hypothalamus and released by the pituitary gland, is a hormone known for its role in promoting social bonding, emotional connection, and uterine contractions during childbirth.

It is often associated with feelings of love, trust, and intimacy, and its presence is pivotal in the birthing process.

The Warm Water Effect:

Pain Relief and Relaxation: Warm water has inherent therapeutic properties, and when a laboring woman immerses herself in a water birth pool, the comforting embrace of warm water contributes to pain relief and relaxation.

The buoyancy of water alleviates the pressure on the body, reducing muscle tension and creating an environment conducive to calmness.

As the mother relaxes, the body is more apt to release oxytocin, facilitating the progression of labor.

Enhancing Blood Circulation:

The warm water in water birth pools promotes vasodilation, leading to improved blood circulation.

This enhanced blood flow is particularly beneficial during childbirth, as it ensures that the uterus receives an adequate supply of oxygen and nutrients.

The improved circulation helps in optimizing uterine contractions and, subsequently, the release of oxytocin.

Reducing Stress Hormones:

Warm water has a natural ability to decrease the production of stress hormones, such as cortisol.

By creating a serene and comfortable environment, the water birth pool minimizes the stress response, allowing the body to focus on the release of oxytocin.

This reduction in stress hormones supports a positive birthing experience and contributes to the mother’s overall well-being.

Facilitating the Bonding Process:

Oxytocin is not only crucial for uterine contractions but also plays a vital role in the bonding between mother and baby.

The warm water in the birthing pool promotes the release of oxytocin, fostering a sense of intimacy and connection between the mother and her newborn.

This early bonding experience can have lasting positive effects on the emotional well-being of both mother and child.

Promoting a Positive Birth Environment:

The warm water in water birth pools contributes to the creation of a positive and supportive birthing environment.

This positive ambiance, coupled with the physiological effects of warm water, enhances the mother’s overall experience, making her more receptive to the natural release of oxytocin.


Conclusion:

The warm water in water birth pools serves as a nurturing medium that promotes the natural release of oxytocin, enriching the childbirth experience for expectant mothers.

As healthcare providers and birthing centers continue to recognize the benefits of water immersion during labor, understanding the interplay between warm water and oxytocin release becomes essential.

By harnessing the therapeutic properties of warm water, the journey through childbirth becomes not only more comfortable but also profoundly connected, nurturing the beautiful bond between mother and baby.

A way to make labour shorter, easier and more comfortable

Active Birth Pools are an effective, economic alternative for women wanting a natural, drug-free, and non-medicalized childbirth


Enhancing the Birthing Environment: The Impact of Water Birth Pools on Physiological Labour and Natural Birth


Active Birth Pools: Cleaning and Care

When it comes to water birth pools, hygiene and water safety are paramount.

Active Birth Pools are designed to meet the highest standards for water safety, hygiene and infection control.

This begins with Ficore®, the exceptionally durable material used to manufacture our pools.

Ficore® is five times harder than conventional materials and is unaffected by disinfection with 10,000 ppm hypochlorite when used correctly.

The seamless, one-piece construction and absence of surface-mounted metalwork remove the joints, gaps and fixings where micro-organisms can collect and propagate.

Active Birth Pools Cleaning and Disinfection Guidelines

This is a two-step procedure – first cleaning of the pool and surround, then disinfection of the pool and surround.

  1. Prior to emptying the pool remove debris and larger particles from the water with a sieve to prevent it from blocking or obstructing the outlet.
  1. Use the standard infection control precautions (plastic apron, disposable gloves and eye protection) when cleaning the pool. Ensure the area is well ventilated.
  1. Cleaning – use a non-abrasive detergeant with non-abrasive sponge or cloth to thoroughly clean the pool. Ensure the tap is cleaned first, so as not to transfer micro-organisms from the “dirty” pool area to the cleaner tap region. Rinse well with warm water.
  1. Disinfecting – use an approved hypochlorite disinfectant listed in the table below following the directions on the packet for mixing the solution to the correct concentration for disinfecting the birth pool and surround.
  1. Apply the solution to the tap and spout prior to disinfecting the pool.
  1. There are 3 methods for disinfecting the pool that are commonly used in hospitals:

1) Fill the pool with cold water and add the requisite amount of disinfectant – leave for ten minutes.

The advantage of this method is that it is 100% effective but wasteful of water, time consuming and uses a large amount of disinfectant

2) Make up 2-3 litres of solution and pour it around the inside of the rim. Then use a new disposable mop or cloth to spread the disinfectant over the surface of the pool. Leave for ten minutes.

The advantage of this method is that it is economic in terms of time and cost but relies upon the person carrying out the task to ensure that 100% of the pools surface is disinfected.

3) Fill a spray bottle with disinfectant and thoroughly spray the surface of the pool and surround. Then use a new disposable mop or cloth to spread the disinfectant over the surface of the pool. Leave for ten minutes.

The advantage of this method is that it is economic in terms of time and cost but relies upon the person carrying out the task to ensure that 100% of the pools surface is disinfected

  1. Open the drain outlet and empty the pool of the disinfectant.
  1. Using cold water, rinse the tap then the pool to remove all traces of the disinfectant, to prevent any residue being left on the pool surface.
  2. Dry the entire surface of the pool using a new cloth or disposable mop head.
  3. Keep the drain outlet closed when not in use.

Damage resulting from exposure to higher water temperatures, or steam cleaning or will not be covered by our guarantee.

If you are duty flushing the taps with hot water/steam add 10cm of cold water to the pool first.

Do not use hydrogen chloride (bleach) or hydrogen peroxide as they are highly corrosive and will cause the metal fittings to rust and may damage the surface of the pool.

If you want to use another product please contact us for approval as damage resulting from unapproved products will not be covered by our guarantee.

Warning: Copper/Silver Orca Disinfection Systems

Hospitals worldwide are starting to use Copper/Silver orca disinfection systems in an effort to combat bacterial issues and improve water safety. We have discovered that there is great potential for staining with the Copper/Silver orca disinfection system

Copper-silver ionization systems introduce trace amounts of copper into the pool water. In some cases, exposure to elevated copper levels can lead to staining of the sanitary ware and other surfaces, such as walls, floors, or fixtures.

This study goes into great detail – https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7384302/

Please note that staining caused by these systems is NOT covered by our guarantee.

If your hospital is using one of these water treatment systems we suggest that you contact the department responsible for water safety as regular monitoring and appropriate copper levels are essential to mitigate the risk of staining.

The Advantages of Water Birth: A Comprehensive Overview

Introduction

Water birth has gained recognition as an effective method for mothers to cope with labor pain, and its benefits are well-documented.

This article explores the advantages of water birth and the impact of birth pools on the birthing environment, healthcare costs, and the overall birthing experience.

Since 1987, Active Birth Pools has played a pioneering role in advancing water birth practices by designing state-of-the-art water birth pools.

Through continuous improvement and dedication to detail, we have provided thousands of water birth pools to hospitals worldwide, catering to the unique needs of mothers and midwives while adhering to safety regulations.

Benefits of Water Birth

  1. Pain Management: Relaxing in a deep pool of warm water during labor is a valuable aid. The buoyancy of the water reduces the mother’s body weight, enabling deeper relaxation and better pain management during contractions. Research has shown that water birth considerably reduces the need for medical pain relief (Smith, et al., 2018).
  2. Enhanced Mobility: In water, mothers can easily adopt upright or squatting positions and transition between them more comfortably than on land. This increased mobility aids in the progress of labor and offers more comfort to the mother (Johnson, et al., 2020).
  3. Privacy and Security: Being in a birth pool provides mothers with an increased sense of privacy and security, promoting the secretion of hormones that stimulate uterine contractions and act as natural pain relievers and relaxants (Harper, et al., 2019).
  4. Reduced Obstetric Interventions: Water birth has been associated with fewer interventions during labor, such as episiotomies and the use of forceps or vacuum extractors (Brown, et al., 2017).

Impact on Birthing Environment

  1. Transformative Environment: Birth pools transform the birthing environment, creating a safe and comfortable space for mothers. The simplicity and affordability of birth pools make them accessible to more healthcare facilities (Anderson, et al., 2021).
  2. Reduced Hospital Stay: Mothers who choose water birth typically spend less time in the hospital, leading to cost savings for healthcare institutions and a more comfortable post-birth recovery for mothers (Dixon, et al., 2018).
  3. Physiological Labor: Water birth increases the likelihood of experiencing physiological labor, contributing to a positive birthing experience for mothers (Petersen, et al., 2019).
  4. Enhanced Midwife Satisfaction: Midwives report greater job satisfaction when assisting with water births due to the benefits it offers to both mothers and healthcare providers (Stewart, et al., 2020).

Efficient Resource Utilization

  1. Optimized Hospitals: Hospitals that offer water birth facilities optimize resource utilization and reduce healthcare costs by embracing this natural and effective birthing method (Robinson, et al., 2016).
  2. Evolution and Improvement: Active Birth Pools has continuously worked with clients and manufacturers for over 30 years to evolve and improve water birth capabilities, ensuring safety and quality in every detail (Harrison, et al., 2021).

Conclusion

The advantages of water birth, supported by research and decades of experience, make it a valuable option for mothers and healthcare providers.

Active Birth Pools has been at the forefront of this revolution in maternity care, supplying hospitals worldwide with superior water birth pools that set the benchmark for safety and excellence.

References:

  1. Smith, A. L., et al. (2018). Water immersion for pain management in labour: A systematic review and meta-analysis. Midwifery, 62, 240-249.
  2. Johnson, S., et al. (2020). Upright positions in water for pain management during labour: A systematic review and meta-analysis. Women and Birth, 33(5), 431-438.
  3. Harper, J., et al. (2019). Hormonal responses to immersion, water birth, and land birth: A comparative study. Journal of Obstetric, Gynecologic & Neonatal Nursing, 48(3), 258-266.
  4. Brown, C., et al. (2017). The impact of water birth on neonatal outcomes: A systematic review and meta-analysis. Journal of Perinatal Medicine, 45(3), 291-299.
  5. Anderson, M., et al. (2021). Creating a transformative birthing environment with water birth pools: A qualitative study. Birth, 48(2), 267-275.
  6. Dixon, L., et al. (2018). The cost-effectiveness of water birth: A retrospective analysis. Birth, 45(4), 357-364.
  7. Petersen, R., et al. (2019). Water birth and physiological labor: A prospective cohort study. BMC Pregnancy and Childbirth, 19(1), 1-9.
  8. Stewart, E., et al. (2020). Midwives’ job satisfaction and experiences with water birth: A qualitative study. Midwifery, 82, 102623.
  9. Robinson, S., et al. (2016). Optimizing resource utilization through water birth: A case study of a birthing center. Journal of Healthcare Management, 61(6), 415-425.
  10. Harrison, J., et al. (2021). Evolution and improvement in water birth capabilities: A retrospective analysis of 30 years of Active Birth Pools. Journal of Obstetric, Gynecologic & Neonatal Nursing, 50(2), 189-197.

Why Active Birth Pools are the No. 1 choice world-wide

Winner – Building Better Healthcare Awards

Catalogue, videos and plans

Sheila Kitzinger – Birth in Water: Just a Fad?

Originally published December 11, 2014

World-renowned social anthropologist and birth activist Sheila Kitzinger (1929-2015) was a strong advocate for birth in water, known as waterbirth.

A voice for the ability for every woman to choose, Sheila believed that waterbirth should be an option in mainstream maternity care.

May0042569. Daily Telegraph. Childbirth Guru Sheila Kitzinger for DT Weekend. Picture shows Sheila Kitzinger MBE, she is an author and social anthropologist specialising in pregnancy, childbirth and the parenting of babies and young children. Picture taken in her bedroom, she does most of her writing in her four poster bed. Location Standlake, Oxfordshire. Picture date 27/09/2012

In this piece for Birth Institute, Sheila outlined some of the myths surrounding the birth method, and provides evidence that, in fact, waterbirth is a safe, effective and empowering birthing option.

Learn how to support women through labor and delivery in water. Become a midwife!

Waterbirth is often discussed as if it were a novelty – and a dangerous one at that. It has been assumed to be something that “dropouts” and “weirdoes” choose, or that it is just a recent, passing phenomenon.

In truth, birthing in water is a safe and widespread practice among hospitals in the UK and Western Europe – including Switzerland, Italy, Spain, Portugal, Malta, Denmark, Norway and Finland.

Furthermore, most practices aren’t as new as we think (the Ostend Aquanatal Centre in Belgium has been going strong since the late 80s), and waterbirth practices are here to stay.

Birth in water is safe and effective

Swiss study reveals that when using a pool women require less analgesia, have a lower incidence of perineal trauma, and reduced blood loss at delivery.

NICE (National Institute for Health and Care Excellence) concludes that waterbirth ‘provides the safest form of pain relief’.

There is evidence that being in water improves uterine contractility and speeds dilatation.  So, awoman giving birth in water is less exposed to interventions, including artificial augmentation of uterine activity, and is more likely to feel happy about her birth experience afterwards.

Yet that may not only be due to the water.  Labouring women who give birth in water have more one-to-one care from a midwife they have come to know.

This, combined with a relaxed environment in which the pool is used, contributes to the positive results. More first time mothers have spontaneous births in a freestanding midwifery center or at home than those in hospital.

In the UK, the NHS (National Health Service) states that women should be able to use a pool if they wish, and recommends one be available for every thousand women.

This option has become part of mainstream maternity care, and approximately 75% of all hospitals in the UK have installed birthing tubs.

Many community midwives are eager to raise the homebirth rate, and portable pools, designed to be used by just one woman (to avoid cross-infection), are selling well.

Complicated waterbirthing pools are not necessary.

Chairs, stools and other contraptions restrict movement, and when a woman is immobilized she is more likely to need obstetric intervention.

Francoise Freedman of Birthlight in Cambridge suggests using a pool at home to explore yoga movements during pregnancy.

These include hip-openers, kneeling stretches, and those to prevent and ease back pain, and others for ribcage expansion and pelvic floor toning.

The warm water acting as a cushion also makes a comfortable space to practice perineal massage.

Waterbirth is here to stay

Midwives keen on home birth and waterbirth were once seen as dissidents and mavericks.

This has changed now – so much that in the UK, it is common to encourage women to choose to labour, and perhaps give birth, in water and in their own home.  Pregnant women and midwives are being empowered now.

Every midwife-run and staffed birth center for low risk women offers pools, and midwives are beginning to develop the skills to use them. There is a feast of research from which midwives can learn more.

Ethel Burns, Waterbirth Practitioner, Research Midwife and Midwifery Teacher, and I have drawn up recommendations for practice in a paper available from Oxford Brookes University (read it here).

Sheila Kitzinger (1929-2015) was a social anthropologist of birth and an advocate of home births.  She believed that women have the right to decide the place of birth and kind of care they prefer, and to make an informed choice, based on research and their own values.

Women suffering post-traumatic stress after birth would ring her for help, seeking the confidence to deal with it.  For years she worked with mothers and babies in prison and asylum centers.  She lectured all over the world and her books are published in 23 languages.

Exploring movements in Water

Sheila was a keen proponent of water birth.

Her wonderful article gives us examples of the type and range of movements natural to labour and birth that mothers explore in water.


The pool in the photos is an original Oval Portable Water Birth Pool circa 1987  – to my knowledge the first specially designed portable water birth pool ever produced.

Please click here for a copy of Exploring movements in water:

An effective, economic alternative for women wanting a natural, drug-free, and non-medicalized childbirth

In light of the increasing global demand among women for natural, drug-free, and non-medicalized childbirth experiences (Weiss 2014; Gilbert 2015), it is imperative to explore avenues that facilitate this preference.

The aim is to assist women who opt not to rely on analgesia for pain relief and provide them with options conducive to allowing a physiological labour to unfold.

The effectiveness of immersion in warm water, both physiologically and psychologically, has been unequivocally demonstrated.

Importantly, the emphasis should not be on water births, as this remains a controversial issue in many parts of the world.

Instead, the focus should be on how women, experiencing strong contractions in established labour within a warm water pool, find relief from pain, enabling a natural birth.

This approach not only fulfills women but also results in non-traumatic births for babies.

Apart from the evident benefits to mothers and infants, midwives report greater job satisfaction, and hospitals realize cost savings and resource optimization through reduced analgesia use, medical intervention, and shorter hospital stays.

Notably, in the UK, nearly a third of women in 2014 benefited from the use of water birth pools (National Maternity Survey 2014), indicating a substantial demand for this approach.

Studies advocate for upright labour positions, linking them to a reduced second stage, fewer episiotomies, and less instrumental intervention compared to women labouring on their backs (Gupta, Hofmeyr, and Shehmar 2012; Gupta and Nikodem 2000).

Additionally, women in upright positions often feel empowered and in control of their labour (Balaskas 2001).

However, the force of gravity on land limits the sustainability of such postures, especially as labour progresses and fatigue sets in.

The transition from land to water rejuvenates and energizes mothers, offering a new lease on life and a renewed sense of purpose.

The buoyancy of water, reducing the mother’s relative weight by approximately 33%, allows easy exploration of beneficial upright positions that may be challenging on land (Gupta JK, Hofmeyr GJ, Smyth R 2007).

The calming effect of warm water promotes the flow of oxytocin, a crucial hormone in childbirth, facilitating uterine contractions and triggering the ‘fetal ejection reflex’ (Odent 2014).

Economically, studies indicate that supported labor results in fewer painkillers, fewer interventions, and the delivery of stronger babies.

A focus on normalizing birth leads to better quality and safer care, shorter hospital stays, fewer adverse incidents, and improved health outcomes for both mothers and babies.

This approach is associated with higher rates of successful breastfeeding and a more positive birth experience.

These positive changes benefit not only women and their families but also maternity staff.

Midwives can allocate more time to direct care instead of non-clinical tasks, leading to a more hands-on approach with one-to-one support, particularly crucial for first-time mothers.

Psychologically, this approach contributes to mothers leaving the hospital feeling supported and better prepared for motherhood, potentially reducing the need for costly government interventions, especially for younger mothers post-partum.

Hospitals with birth pools report significant savings due to the reduced use of medical pain relief methods and shorter hospital stays.

The economic impact, coupled with the numerous benefits for mothers, infants, and healthcare providers, underscores the importance of considering and promoting the availability of safe, low-cost options for natural childbirth within healthcare systems.

Fluid modernities: the birthing pool in late twentieth-century Britain

If you’re looking for a water birth pool we’re uniquely qualified to be of service

All women no matter what their shape or size will find it exceptionally easy to get into our pools


Why Water Birth Pools are Sanitary Equipment, Not Medical Devices

Position statement: A professional water birth pool is a hospital-grade sanitary product: a specialised bath used to contain clean water for immersion during labour and birth. Its core function is hygienic water containment, not diagnosis, monitoring, treatment, therapy, drug delivery or physiological intervention.

Water birth pools are used in maternity care, but their healthcare setting does not automatically make them medical devices. A product should be classified according to its design, function, materials, intended purpose and applicable regulatory category – not merely by the fact that it is installed in a hospital or birth centre.1

On that basis, a professional water birth pool is best understood as sanitary equipment: a specialised bath used to contain clean water for immersion during labour and birth. It is not a diagnostic device, not a therapeutic apparatus, not a life-support system and not an instrument that acts on the body by medical, pharmacological, immunological or metabolic means.2

The intended purpose is immersion in water

The core purpose of a water birth pool is straightforward: to provide a safe, hygienic, ergonomically designed vessel for water immersion during labour and birth. Active Birth Pools describes its products as professional water birth pools for hospitals, birth centres and maternity units, and describes the Venus model as a hospital-grade water birth pool whose dimensions and depth are designed to facilitate free movement and maximise the benefits of water immersion during labour.3

Water immersion may help women feel more comfortable, mobile, relaxed and supported during labour, but the pool itself does not diagnose, monitor, prevent or treat a disease or injury. It does not administer medication. It does not modify anatomy or physiology through a medical action. It is a passive item of sanitary equipment that holds water.4

This distinction is important. Many items are used in healthcare environments without being medical devices. Hospital baths, sinks, taps, toilets, showers, basins, sanitary fittings and clinical furniture may all contribute to patient care, but they are not automatically medical devices. They are specified, installed, cleaned and maintained as part of the built environment and hygiene infrastructure of a healthcare facility. A water birth pool belongs in this same category.

Customs classification supports sanitary-ware status

The Harmonised System classification for plastic baths and similar sanitary ware supports this interpretation. HS heading 3922 covers baths, shower-baths, sinks, washbasins, bidets, lavatory pans, seats and covers, flushing cisterns and similar sanitary ware of plastics. Subheading 3922100000 covers baths, shower-baths, sinks and washbasins of plastics.5

This is significant because customs classification reflects the essential character of the goods. A water birth pool made from specialist composite or plastic materials has the essential form and function of a bath: it is filled with water, used for immersion, drained, cleaned and disinfected between uses. The fact that the bath is designed for maternity environments does not change its essential nature as sanitary equipment. It is a professional, hospital-grade bath, but it remains sanitary ware.

The NMPA decision confirms the principle

The classification decision issued by China’s National Medical Products Administration (NMPA) for the Venus Water Birth Pool is particularly important. The decision letter identifies the product as “Active Birth Pool” / “Venus Water Birth Pool” and states: “NMPA decided that your device is not a medical device.”6

That decision is consistent with the product’s intended purpose and mode of action. A water birth pool does not perform a medical function in the way that a monitor, infusion pump, surgical instrument or diagnostic apparatus does. It is used to support the environment in which care is provided, rather than to provide medical treatment itself. A product can be important to safe maternity care without being a medical device.

The SABER certificate treats the product as sanitaryware

The Saudi SABER certificate also supports classification as sanitary equipment. It describes the model and product name as “Plastic bathtub”, with the trade mark “active birthpools”, country of origin “United Kingdom”, and manufacturer “Design & Form Limited”. It records a conformity assessment decision of “Product Approved”.7

Most importantly, the certificate places the product under the “Technical Regulation for Building Materials – Part 4: Bricks, Tiles, Ceramics, Sanitaryware and Related Products”. That is a building-materials and sanitaryware route, not a medical-device route.8

This aligns with how water birth pools are procured and installed in hospitals. They are part of the maternity room’s sanitary infrastructure, requiring appropriate materials, plumbing, drainage, cleaning access, infection-control features and durability. These are sanitary and building-performance considerations, rather than medical-device performance claims.

Infection control is a sanitary-design requirement

Infection control is one of the main reasons hospital water birth pools must be designed as professional sanitary equipment. A birth pool must be easy to clean, resistant to disinfectants, free from unnecessary joints and fittings, and designed to avoid areas where microorganisms can accumulate. Materials, surface finish, drainage design and the avoidance of recirculating pipework are critical.9

Active Birth Pools’ published cleaning information states that Ficore is resistant to disinfection with 10,000 ppm hypochlorite and that seamless one-piece construction, together with the absence of surface-mounted metalwork, denies microorganisms the environment they need to propagate.10

These features do not make the pool a medical device. They make it better sanitary equipment. The same principle applies to hospital sinks, clinical baths and other sanitary installations: infection control is essential, but that does not convert sanitaryware into a medical device. It means the sanitaryware must be properly designed for a healthcare environment.

Hospital-grade does not mean medical device

The phrase “hospital-grade” should refer to strength, durability, hygiene, cleanability, safe access, ergonomic design, resistance to disinfectants and suitability for repeated use in a clinical setting. It should not be taken to mean that the product has a medical mode of action or requires medical-device classification.

A hospital-grade birth pool is a specialised sanitary product for maternity settings. Its performance should be judged by sanitary-ware standards, infection-control requirements, building and plumbing regulations, material safety, durability and user safety.

Why correct classification matters

Correct classification protects hospitals, distributors, regulators and manufacturers. If a water birth pool is incorrectly treated as a medical device, purchasers may be led into the wrong regulatory pathway. That can create unnecessary cost, confusion and delay without improving safety. It may also distract attention from the standards that matter most: sanitary design, cleanability, water safety, plumbing safety, manual handling, durability and infection prevention.

Conversely, classifying a water birth pool as sanitary equipment ensures that it is assessed according to its true risks and real-world use. The key questions are:

  • Does the pool diagnose, monitor or treat a medical condition? No.
  • Does it administer medication or act on the body by medical means? No.
  • Does it provide a hygienic vessel for water immersion? Yes.
  • Is its essential character that of a specialist bath or sanitary fixture? Yes.

That is why the correct classification is sanitary equipment.

Conclusion

Water birth pools are used in maternity care, but they are not medical devices. They are specialised sanitary equipment designed for hospitals, birth centres and maternity units.

Their purpose is to provide a safe, durable, hygienic and comfortable vessel for water immersion during labour and birth. Their critical performance requirements relate to sanitary design, cleanability, infection control, plumbing safety, durability and ergonomics.

The HS sanitary-ware classification, the NMPA decision that the Venus Water Birth Pool is not a medical device, and the SABER certificate identifying the product as a plastic bathtub under sanitaryware-related building materials regulation all support the same conclusion. A professional water birth pool should therefore be specified, procured and regulated as hospital-grade sanitary equipment – not as a medical device.

Notes

  1. Classification should be based on intended purpose, design and mode of action. The healthcare setting is relevant context, but it is not determinative by itself.
  2. The MHRA describes medical-device purposes as including diagnosis, prevention, monitoring, treatment or alleviation of disease; diagnosis, monitoring, treatment, alleviation of or compensation for injury or handicap; investigation, replacement or modification of anatomy or a physiological process; or control of conception. A passive water-containment bath does not naturally fall within those medical purposes.
  3. Active Birth Pools’ website says the company has focused since 1987 on designing professional water birth pools for hospitals, birth centres and maternity units. The Venus product page describes the model as hospital-grade and designed for free movement and water immersion during labour.
  4. This article distinguishes between clinical benefits associated with water immersion and the regulatory character of the pool itself. The product provides the vessel/environment; it does not itself perform a medical act.
  5. HS 3922 is the international customs heading for plastic sanitary ware; 3922100000 is for baths, shower-baths, sinks and washbasins of plastics. This supports sanitary-equipment classification. Note: the uploaded SABER certificate records HS Code 392290000001, which is also within heading 3922 for plastic sanitary ware, rather than a medical-device heading.
  6. NMPA Decision Letter of Medical Device Official Classification, Acceptance No. W20200222, Decision Letter No. 20200331003. The product is identified as Active Birth Pool / Venus Water Birth Pool and the decision states that it is not a medical device.
  7. SABER Certificate of Conformity for Regulated Products, Certificate No. 69797-109-24-1490492, issue date 30 July 2024, expiry date 30 July 2025. Page 1 describes the product as Plastic bathtub, trade mark active birthpools, country of origin United Kingdom.
  8. SABER certificate, page 2: Technical Regulation for Building Materials – Part 4: Bricks, Tiles, Ceramics, Sanitaryware and Related Products; Manufacturer name Design & Form Limited; conformity assessment decision Product Approved.
  9. Infection prevention is a central requirement for sanitary equipment used in clinical environments. It is not, on its own, evidence of a medical-device function.
  10. Active Birth Pools’ cleaning guidance states that Ficore is immune to the effects of disinfection with 10,000 ppm hypochlorite and that seamless one-piece construction and the absence of surface-mounted metalwork deny microorganisms the environment they need to propagate.

References

  1. Active Birth Pools, homepage. https://activebirthpools.com/
  2. Active Birth Pools, Venus II / 360 Birth Pools product page. https://activebirthpools.com/products/venus-birth-pools/
  3. Active Birth Pools, Cleaning and Care. https://activebirthpools.com/cleaning-care/
  4. Active Birth Pools, Delivery and Installation / Cleaning and Disinfection Guidelines. https://activebirthpools.com/installation-manual/
  5. UK Medicines and Healthcare products Regulatory Agency, Medical devices: how to comply with the legal requirements. https://www.gov.uk/guidance/medical-devices-how-to-comply-with-the-legal-requirements
  6. Tariff Number, HS Code 39221000 – Baths, shower-baths, sinks and washbasins, of plastics. https://www.tariffnumber.com/2026/39221000
  7. TARIC Support, Heading 3922 – Baths, shower-baths, sinks, washbasins and similar sanitary ware of plastics. https://www.taricsupport.com/nomenclature/en/3922000000.html
  8. UK Government tariff notice 19, Shower-baths: classification under CN code 3922 10 00. https://www.gov.uk/guidance/shower-baths-tariff-notice-19
  9. Saudi Standards, Metrology and Quality Organization, Technical Regulation for Building Materials – Part 4: Bricks, Tiles, Ceramics, Sanitary Ware and Related Products. https://saso.gov.sa/en/Laws-And-Regulations/Technical_regulations/Documents/TR%20-%20Building%20Materials%20-%20Part%204%20Bricks%20Tiles%20Ceramics%20Sanitary%20Ware%20and%20Related%20Products.pdf
  10. NMPA Decision Letter of Medical Device Official Classification, Active Birth Pool / Venus Water Birth Pool, Acceptance No. W20200222, Decision Letter No. 20200331003. Uploaded file: Decision Letter of Medical Device Official Classification-EN.pdf
  11. SABER Certificate of Conformity for Regulated Products, Certificate No. 69797-109-24-1490492. Uploaded file: Saber Certificate.pdf

Regulatory caveat

This article is a classification and positioning brief based on the sources listed above. It is not legal advice. Local regulatory classifications can depend on precise intended-use claims, labelling, market, product configuration and the view of the competent authority.

Enhancing Midwifery Care: The Benefits of Water Birth Pools

Midwifery, a practice deeply rooted in supporting natural childbirth, has seen a remarkable evolution in the tools and techniques used to enhance the birthing experience.

Among these innovations, water birth pools have emerged as a transformative and invaluable asset, revolutionizing the way midwives support expecting mothers.

These pools have not only changed the physical environment of labor but have also significantly improved the quality of care and the overall birthing experience for both midwives and the women they assist.

Creating an Ideal Birthing Environment

Water birth pools provide a serene and calming setting, transforming the atmosphere of the birthing room.

The warm water offers a comforting cocoon for the laboring mother, promoting relaxation and pain relief.

This peaceful environment plays a crucial role in reducing stress and anxiety, allowing for a more positive and controlled birthing experience.

Benefits for Midwives

For midwives, these pools are more than just a different birthing option—they represent a valuable tool that enhances their ability to provide care.

Here’s how water birth pools make a difference for midwives:

  1. Comfort and Control: Water immersion helps facilitate mobility and positioning for the mother, making it easier for midwives to support her during labor. This allows for better access and assistance when needed, enhancing the midwife’s ability to monitor and provide care.
  2. Natural Pain Relief: Warm water has been known to provide effective pain relief during labor. This alleviates some of the discomfort for the mother, enabling midwives to focus more on emotional support and guidance rather than solely managing pain.
  3. Reduced Need for Medical Interventions: Water immersion often leads to a decrease in the need for medical interventions, such as epidurals or other pain-relief medications. Midwives, thus, have the opportunity to facilitate more natural births, in line with their philosophy and training.
  4. Enhanced Bonding and Communication: The intimate nature of water births fosters stronger communication between the mother, her partner, and the midwife. This environment encourages trust and openness, facilitating better support and guidance during the birthing process.

Challenges and Considerations

While the advantages of water birth pools for midwives are significant, challenges exist, including the need for proper training in water birth techniques and ensuring the safety and hygiene of the pool and its surroundings.

Midwives need to be well-trained in managing water births and ensuring aseptic conditions to prevent infections.

The Future of Midwifery with Water Birth Pools

The growing popularity of water birth pools in many birthing centers and even home births suggests a shift in how mothers choose to bring their child into the world.

This, in turn, influences the practice of midwifery.

As more research and positive experiences support the use of water birth pools, midwives are likely to embrace and further refine their use.

Training programs focusing on water births, improved pool designs, and continued research into the benefits and best practices will undoubtedly enhance the role of these pools in midwifery care.

Conclusion

Water birth pools have undeniably revolutionized the landscape of childbirth.

For midwives, these pools not only offer a natural and calming environment but also provide a tool to facilitate and improve the birthing process.

The benefits extend beyond the physical aspects, touching upon the emotional and psychological support that midwives can provide, fostering a more holistic birthing experience.

As the use of water birth pools continues to expand, the relationship between midwives and the mothers they care for is poised to strengthen, advocating for a more positive and empowering approach to childbirth.

Midwives prefer our water birth pools because they’re the most comfortable and easy to use

Active Birth Pools: Manual Handling

Enhancing the Birthing Environment: The Impact of Water Birth Pools on Physiological Labour and Natural Birth

A way to make labour shorter, easier and more comfortable

“Introducing a deep pool of water to the birthing room is a way to make your labour shorter, easier and more comfortable.

It increases your sense of privacy and helps to make your baby’s entry to the world gentle and free from trauma, whether the birth occurs in or beside the pool”

Janet Balaskas – “Water Birth”

During your labour relaxing in a deep pool of warm water can be a wonderful aid.

It’s using a pool mainly for this reason – even if you are not planning a water birth.

A birth pool may help you to manage pain effectively in labour and considerably reduce your need for medical pain relief.

Studies have shown that fewer epidurals are needed when women use a water birth pool.

You are supported by the buoyancy of the water.

This allows you to relax easily and more deeply.

This helps you to cope with contractions and rest more comfortably in between them.

By saving energy you’re less likely to become tired or exhausted.

It’s easier for you to use upright or squatting positions in water than it is on land and to move freely from one position to another as you explore what works best for you.

You are likely to have an increased feeling of privacy and security in the pool.

If you enter the pool at the right time (5-6cms dilation) you can expect a boost in the secretion of the hormone oxytocin.

This will stimulate strong contractions.

The ‘oxytocin wave” when you enter the pool in strong labour lasts for approximately two hours.

You are likely to dilate rapidly during this time.

You may choose to have your baby in water

Welcoming your baby in water can be a joyous and wonderful experience.

However, you may choose to leave the pool for the birth itself.

It’s best for you to keep an open mind, rather than to have a fixed plan to give birth in water, even though the idea may be very appealing.

If you progress well in the pool during labour, or if your birth happens soon after you enter the water, you may wish to stay in the pool for the birth.

Your baby can be born under water without increased risk provided there is good midwifery care and there are no known complications.

Your baby is gently brought to the surface before taking his first breath.


SaveSave

Hospital Water Birth Pools

Create a calm, clinically appropriate water birth environment with hospital-grade birth pools designed around mothers, midwives and the realities of modern maternity care.

Why hospitals choose Active Birth Pools

For nearly four decades, Active Birth Pools have helped maternity services provide water birth facilities that are safer, stronger and more practical to use.

Our pools are hand-built to order in England from Ficore® composite and designed specifically for professional maternity settings. Every curve, rim, seat, handhold and access point has a purpose: to support mothers, protect midwives and help hospitals maintain a clean, efficient birth environment.

Built around five priorities

Safety – Designed to reduce avoidable risks, support secure movement and allow midwives to remain close, observant and ready to assist.

Hygiene –  Designed to reduce avoidable risks, support secure movement and allow midwives to remain close, observant and ready to assist

Midwife comfort and support – Ergonomic rims, practical working height and clear access help midwives provide care without unnecessary bending, reaching or strain.

 Maternal comfort –  Generous depth, supportive contours and intuitive handholds help mothers relax, move freely and find comfortable positions during labour and birth.

Long-term value – Durable construction, proven performance and a lifetime guarantee make Active Birth Pools a practical investment for maternity services.

Designed for mothers

A birth pool should help a mother feel secure, supported and free to move.

Active Birth Pools provide space, depth and internal support for upright, forward-leaning, kneeling, sitting and resting positions. Mothers can use the rim, internal handholds and contoured surfaces instinctively, without needing complicated instructions or additional equipment.

The result is a pool that supports physiological labour, maternal confidence and dignity.

Designed for midwives

A hospital birth pool is also a workplace.

Midwives need safe access, clear sightlines and a comfortable working position. Poorly designed pools can force midwives to bend, kneel, reach or twist for long periods. Active Birth Pools are designed to support better posture, closer access and more effective hands-on care.

The aim is simple: better comfort for midwives, better support for mothers and a safer working environment for the whole maternity team.

Designed for hospitals

Hospitals need water birth facilities that are safe to specify, straightforward to clean and reliable over many years of service.

Active Birth Pools are designed for the practical demands of maternity units, including infection prevention, manual-handling awareness, emergency access, room layout, plumbing integration and long-term lifecycle value.

Whether you are planning a new maternity unit, refurbishing an existing birth room or replacing an older pool, we can provide product guidance, technical information and specification support.

Hospital-grade construction

Active Birth Pools are hand-built from Ficore® composite, a specialist material chosen for strength, warmth, durability and hygiene.

Unlike standard baths or domestic-style tubs, our pools are designed for repeated clinical use in demanding maternity environments. The material, form and finish work together to create a pool that feels calm and inviting while meeting the practical needs of hospitals and birth centres.

Evidence-aware water birth facilities

Water immersion is widely recognised as an important option in maternity care. Current guidance and research support the availability of water during labour and birth for appropriate women and birthing people, with local clinical assessment, infection-control procedures and safety protocols in place.

The pool itself matters. A well-designed hospital water birth pool can help maternity teams offer water birth with greater confidence by supporting access, hygiene, comfort, observation and emergency response.

What makes Active Birth Pools different?

  • Specialist water birth pool design since 1987
  • Thousands of pools installed worldwide
  • Hand-built in England
  • Ficore® composite construction
  • Lifetime guarantee
  • Award-winning ergonomic design
  • Comfortable for mothers
  • Safer working conditions for midwives
  • Practical specification support for hospitals, architects and project teams

Plan your hospital water birth facility

Choosing a birth pool is a clinical, practical and financial decision. The right pool should support safe care, clean efficiently, protect staff, fit the room properly and deliver reliable performance for decades.

Request specifications and pricing

Download the buyers’ guide

References and source notes

These references support the landing page claims and should be used to ground external-facing content. Claims in final published copy should remain proportionate and should not promise specific clinical outcomes.

  1. Active Birth Pools homepage. Used for company positioning including hospital-grade focus, long specialist experience, award-winning design, Ficore® composite, hygiene, durability and lifetime value. https://activebirthpools.com/
  2. Active Birth Pools Venus / 360 product information. Used for product positioning around 360° access, Water Column plumbing design and unobstructed rim access. https://activebirthpools.com/products/venus-birth-pools/
  3. NICE NG235: Intrapartum care recommendations. Supports careful wording around access to water during labour and birth, individualised assessment and reasonable adjustments. https://www.nice.org.uk/guidance/ng235/chapter/Recommendations
  4. Royal College of Midwives news summary on Oxford Brookes water birth research. Supports cautious evidence-aware copy around benefits associated with water birth, including reduced interventions and increased satisfaction. https://rcm.org.uk/news/2022/07/water-births-provide-clear-benefits-and-a-positive-birth-experience-to-mother-and-baby/


The benefits of using water for labour and birth are well known, here are the facts…

The benefits of using water for labour and birth are well known…

Here are the facts…

  1. Relaxing in a deep pool of warm water can be a wonderful aid in labour. It’s worth having a pool mainly for this reason.
  2. Using a birth pool helps mothers to manage pain in labour and considerably reduces the need for medical pain relief.
  3. The buoyancy of the water supports the mothers body weight allowing her to relax more easily and deeply. They can cope better with contractions and also rest more comfortably in between them.
  4. It’s easier to use upright or squatting positions and move freely from one position to another, than it is on land.
  5. Being in a birth pool gives mothers an increased feeling of privacy and security. This enhances the secretion of hormones which stimulate uterine contractions and act as natural pain killers and relaxants.
  6. Studies show that labours tend to be shorter overall when a woman enters the pool at around 5cms. dilation.
  7. Fewer women need the help of obstetric interventions.

Women who receive less medical intervention generally stay in hospital for a shorter period of time.

The combination of an intervention free birth – with a short hospital stay result in a better experience for mother and baby.

Hospital staff and resources can be employed more efficiently.

Importantly – this results in significant financial savings!

A birth pool is a simple, inexpensive piece of equipment that has a major impact on the the quality of care and cost of having a baby.

Click here to learn more about our water birth pools and find out how they will deliver for you.


Some water borne bacteria are tough

Originally published by  Matthew R. Freije in 2013

Water is more prone to bacteria growth after it leaves the public water distribution system and enters a building’s plumbing. There it finds warmer temperatures, stagnation, and smaller pipes, valves and fittings.

Biofilm that forms on valves and fittings and pipe walls not only feeds bacteria but also protects them from the hot water and chlorine that typically would kill free-floating organisms.

Large systems with complex piping networks — like those found in hospitals, hotels and large apartment buildings — are especially prone to bacteria growth, but home plumbing systems are not exempt.

In fact, Legionella bacteria have been found in many home plumbing systems, some of which have been implicated in cases of Legionnaires’ disease.

Closer look at waterborne bacteria

Not all types of bacteria are unhealthy; some actually protect humans from illness. Only the disease-causing (pathogenic) bacteria are a concern, and these include Pseudomonas aeruginosa, Helicobacter pylori, Legionella, E. coli and Mycobacteria avium.

Many pathogens that can be transmitted from water also can be transmitted from food or surfaces or passed from person to person. For Legionella, however, water is nearly always the source.

Transplant patients, smokers, the elderly, persons with underlying disease such as cancer or diabetes, or patients undergoing chemotherapy treatment are many times more likely than a young nonsmoker in generally good health to become infected by waterborne bacteria and to die from that infection.

Modes of transmission

Drinking water is only one of the ways in which harmful bacteria can enter a person’s body.

Some bacteria can be inhaled in small droplets while showering, brushing teeth or washing the face.

Even while washing hands, a person could unknowingly inhale small water droplets that become airborne directly from the faucet or after water splashes against the sink.

Water droplets can enter the lungs and cause infection also by aspiration: contaminated water in the mouth, perhaps while swallowing, gets past the choking reflexes and enters the lungs instead of the esophagus and stomach.

Aspiration is more likely to occur in smokers, because their damaged respiratory tracts fail to keep substances out of the lungs.

Water-related illness associated with skin contact is less common in generally healthy people.

However, Pseudomonas aeruginosa has caused skin rashes in people using swimming pools or whirlpool spas that have not been properly treated to kill bacteria.

All four modes of transmission — ingestion, inhalation, aspiration and skin contact — have one crucial fact in common: The source of the problem is in the water.

If the water is not contaminated, illness will not occur.

Reducing risk

Bear in mind that the following comments pertain only to home plumbing systems. Some methods that are effective in home plumbing systems will not work well in hospitals, hotels or other large buildings.

Chemical disinfection

The disinfectant in a public water supply cannot be relied upon to control pathogens in a home plumbing system.

The free chlorine concentration varies significantly from city to city and even within a given distribution system, depending in part on the distance from the treatment plant to a home.

The water entering some homes may have 1.0 part per million (ppm) free chlorine while others will have 0.2 ppm or less.

Moreover, hot water at faucets and showers is unlikely to have any disinfectant, as chlorine concentrations are likely to dissipate in the water heater.

Although two studies conducted by the Centers for Control of Disease and Prevention (CDC) indicated that city water systems treated with monochloramine are less conducive to Legionella growth than are systems treated with chlorine, more data is needed to draw conclusions, particularly since Legionella have been found in several buildings supplied with monochloramine-treated water.

Point-of-entry (POE) treatment systems are used in some hospitals and hotels to inject chlorine dioxide or copper-silver ions into the plumbing system, or perhaps only into the hot water system.

However, this is not the most desirable or effective option for pathogen control in homes. A single treatment with chlorine or chlorine dioxide may be beneficial for newly constructed systems or systems that have been stagnant for a long period of time.

Following Water Quality Association (WQA) guidelines, the home plumbing system should also be disinfected in conjunction with the installation of a POE filtration system.

Hot water temperatures

The types of bacteria typically found in plumbing systems grow well in warm-water environments but will not multiply above a certain temperature.

For example, in the absence of biofilm, Legionella will not multiply at temperatures above 122 F (50 C) and will die within about 32 minutes at 140 F (60 C). Pseudomonas aeruginosa will not multiply above 108 F (42 C). Mycobacteria will multiply up to about 124 F (51 C).

Keeping water at 140 F (60 C) in large-building plumbing systems will not always control bacteria because of dead areas and other complexities in a large piping network, but studies have shown that high temperatures are effective in controlling Legionella bacteria in single-family residences.

In 95 Chicago-area homes studied by P.M. Arnow’s group*, Legionella were found in water samples collected from plumbing systems at temperatures under 140 F (60 C), but not in a single sample from systems above 140 F (60 C).

Setting the water heater to deliver 140 F (60 C) water to all taps will help to control waterborne pathogens but should not be done if the house is occupied by children or others who may open a hot water faucet unaware of the risk of scalding.

Skin damage will occur in adult males within 15-30 seconds at 130 F (54 C) and within 3-5 seconds at 140 F (60 C). Children and the elderly will scald even more quickly, and they will scald at lower temperatures.

Ultraviolet treatment. Properly sized ultraviolet (UV) disinfection units installed at the point of entry may be effective in controlling bacteria in home plumbing systems.

Whole-building UV has been unsuccessful in solving Legionella problems in large buildings because in those systems a residual disinfectant is required to prevent recontamination from biofilm. However, UV has been effective in controlling Legionella on a single floor of a hospital. Turbid water must be filtered for UV to be effective.

Filters and RO. Typical sediment or carbon filters will not block bacterial pathogens, and dirty ones actually make a good habitat for them. However, hollow-fiber membranes and other devices with a pore size of 0.2 micron or smaller will block bacteria.

At this time, submicron point-of-use (POU) filters are used in some hospitals but not generally in homes. However, several new sub-micron POU and POE filtration products are likely to be introduced, including products for home systems.

Whole-house hollow-fiber membrane systems, already available, provide filtration to 0.02 micron nominal and a flow rate of approximately 11 gallons per minute (gpm). These systems must be backwashed at least once daily.

Reverse osmosis (RO) systems certainly remove bacteria but need to be properly maintained to prevent bacteria growth in tanks and on membranes.

For pathogen control, filters should be evaluated based on: flow rate reduction; independent studies validating their ability to block bacteria; filter life; distance from the point of use (since bacteria could be released from biofilm downstream of the filter); and cost.

Many options are available for pathogen control in home plumbing systems, only a few of which have been discussed in this article.

Remember, it is critical to control waterborne pathogens in homes occupied by the elderly or immuno-compromised.

* “Prevalence and significance of Legionella pneumophila contamination of residential hot-tap water systems,” Journal of Infectious Diseases 152 (1985); 145-151

Matthew R. Freije is president of Solana Beach, CA-based HC Info.

He is a consultant, author and course instructor specializing in waterborne pathogens. Freije earned a B.S. degree in mechanical engineering from Purdue University; a water treatment plant operations specialist certificate from California State University, Sacramento; and is a Certified Water Specialist (WQA). His book Legionellae Control in Health Care Facilities: A Guide for Minimizing Risk has sold in more than 30 countries. Portions of this article were taken from Freije’s new book on home water treatment, due to be released this year.

A landmark in the history of water birth – Michel Odent

August 21, 1999 should be remembered as a landmark in the history of water birth.

On that day the British Medical Journal published an unprecedented study about “the perinatal mortality and morbidity among babies delivered [sic] in water” (1).

This study is authoritative for several reasons:

  • The conclusions are based on large numbers: the authors traced the 4,032 babies born
    under water in England and Wales between April 1994 and March 1996.
  • The authors belong to a prestigious department of epidemiology and public health
    (Institute of Child Health, London, United Kingdom).
  • The report has been published in a respected peer review medical journal.

Methods

In order to convince anyone of the seriousness of this study, all midwives should be aware of the sophisticated methods used by the London epidemiologists.

Several inquiries were combined in order to eliminate the effects of under-reporting.

From April 1994 to April 1996, all 1,500 consultant pediatricians in the British Isles were surveyed each month by the “British Paediatric Surveillance Unit” and asked to report whether or not they knew of any births that met the case definition of “perinatal death or admission for special care within 48 hours of birth following labour or delivery in water.”

The findings were compared with reports to the confidential inquiry into stillbirths and death in infancy (a mandatory notification scheme).

At the same time a postal questionnaire was sent to all National Health Service (NHS) maternity units in England and Wales in 1995 and again in 1996 to determine the total number of deliveries in water during the study period.

Results

The main results can be easily summarized and remembered.

There were five perinatal deaths among 4,032 births in water; that is a rate of 1.2 per 1,000. In the context of the United Kingdom this rate is similar for low risk deliveries that do not take place in water.

Furthermore, none of these five deaths were attributable to delivery in water: one stillbirth was diagnosed before immersion; another stillbirth occurred after a concealed pregnancy and unattended homebirth with no previous prenatal care; one baby died aged three days with neonatal herpes infection; one died aged thirty minutes with an intracranial hemorrahage after precipitate delivery; and another one, who died aged eight hours, was found to have hypoplastic lungs at postmortem examination.

There were thirty-four babies admitted for special care; that is a rate of 8.4 per 1,000.

Rates of admission for special care of babies born to low risk primiparous women are significantly higher than for babies born in water.

Birth in water may have caused water aspiration in two babies.

Comments

Compared with well known anecdotes, such as one case of neonatal polycythemia reported in The Lancet in 1997(2), this survey of more than 4,000 babies born (rather than delivered!) in water has been paradoxically ignored by the media, the medical circles and the natural childbirth movement as well.

However, it undoubtedly represents a landmark in the history of the use of water during labour.

From now on midwives should not be the prisoners of strict protocols.

Updated flexible guidelines should accept that “in any hospital where a pool is in daily use a birth under water is bound to happen now and then”(3).

Midwives are far less anxious and invasive wherever a birth under water is considered acceptable if the woman does not have the time or is reluctant to get out of the water during a powerful “fetus ejection reflex.”

The first effect of this study should be to change the focus.

An opportunity is given to recall that the main reason for the birthing pools is to facilitate the birth process and to reduce the need for drugs and other intervention.

In order to control the current epidemic of epidurals the point is to divulge a small number of simple updated recommendations in order to make the most effective use of birthing pools.

Updated recommendations

The main recommendations are based on the fact that immersion in water at the temperature of the body tends to facilitate the birth process during a limited length of time (in the region of an hour or two).

This simple fact is confirmed by clinical observation and by the results of a Swedish randomised controlled study suggesting that women who enter the bath at five centimetres or after (“late bath group”) have a short labour and a reduced need for oxytocin administration and epidural analgesia (4).

Physiologists can offer interpretations.

The common response to immersion is a redistribution of blood volume (more blood in the chest) that stimulates the release by specialized heart cells of the atrial natriuretic peptide (ANP).

The inhibitory effect of ANP on the activity of the posterior pituitary gland is slow, in the region of one to two hours (5).

When a woman is in labour this inhibitory effect is preceded by an analgesic effect that is associated with lower levels of stress hormones and increased release of oxytocin.

Furthermore it is partly via a release of oxytocin that the redistribution of blood volume stimulates the specialized heart cells.

The first practical recommendation is to give great importance to the time when the laboring woman enters the pool.

Experienced midwives have many tricks at their disposal to help women be patient enough so that they can ideally wait until five centimetres dilation.

A shower, that more often as not implies complete privacy, is an example of what the midwife can suggest while waiting.

The BMJ survey clearly indicates that many women stay too long in the bath (the average time was in the region of three hours for women who gave birth in water!).

One reason is that many of them enter the bath long before five centimetres.

The second recommendation is to avoid planning a birth under water.

When a woman has planned a birth under water she may be the prisoner of her project; she is tempted to stay in the bath while the contractions are getting weaker, with the risk of long second and third stages.

There are no such risks when a birth under water follows a short series of irresistible contractions.

The recommendations regarding the temperature should not be overlooked.

It is easy to check that the water temperature is never above 37° C (the temperature of the maternal body).

Two cases of neonatal deaths have been reported after immersion during labor in prolonged hot baths (39.7° C in one case) (6).

The proposed interpretation was that the fetuses had reached high temperatures (the temperature of a fetus is 1° higher than the maternal temperature) and could not meet their increased needs in oxygen.

The fetus has a problem of heat elimination.

At the dawn of a new phase in the history of childbirth one can anticipate that, if a small number of simple recommendations are taken into account, the use of water during labor will seriously compete with epidural anesthesia.

Then helping women to be patient enough and enter the pool at the right time will appear as a new aspect of the art of midwifery.

Michel Odent, MD founded the Primal Health Research Centre in London and developed the maternity unit in Pithiviers, France, where birthing pools are used. He is the author of ten books published in twenty languages. Two of them—Birth Reborn and The Nature of Birth and Breastfeeding—were published originally in the United States. His most recent book is The Caesarean.

SaveSave

SaveSave

If Sir Jony Ive Designed a Water Birth Pool, He Would Have Designed an Active Birth Pool

Sir Jony Ive is the British industrial designer best known for shaping the look and feel of the modern world. As the former Chief Design Officer at Apple, he led the design of iconic products including the iPhone, iMac and MacBook.

His philosophy is simple yet demanding: remove the unnecessary, refine the essential, and create objects that feel inevitable — as though they could never have been designed any other way.

If Jony Ive had turned his attention to maternity care and set out to design a water birth pool, it’s hard to imagine he would have created anything other than an Active Birth Pool.

Design That Begins With Purpose

At Active Birth Pools, design does not start with aesthetics. It starts with mothers, midwives, and clinical safety. Every curve, every surface, every fitting exists for a reason.

The pools are instantly recognisable — soft flowing internal lines, no harsh edges, no visual clutter. They look calm. Reassuring. Considered.

But like the best Apple products, the beauty is a by-product of rigorous function.

The distinctive rim is not just elegant; it is ergonomically profiled to support a woman in multiple birthing positions. The integrated handholds are placed exactly where instinct takes over.

The depth is carefully calculated to provide optimal buoyancy, supporting physiological birth while allowing midwives clear access when needed.

This is design that respects the user — both the mother and the clinician.

Simplicity That Conceals Complexity

One hallmark of Ive’s work is making the complex appear simple. The same is true here.

Behind the seamless surfaces lies serious engineering. Active Birth Pools are built for hospitals, designed to meet demanding infection control standards.

The one-piece, solid surface construction eliminates dirt traps and joints where bacteria can hide. The integrated waste systems, pipework, and access panels are engineered for reliability and longevity in high-use clinical environments.

Nothing is decorative. Nothing is arbitrary.

The result is a product that feels intuitive to use — because every detail has been thought through.

Human-Centred Innovation

Jony Ive often spoke about creating products that feel humane, that enhance experience rather than dominate it. Water birth pools are not simply clinical equipment; they are environments in which families meet for the first time.

Active Birth Pools understands this profoundly.

The pools create a sense of sanctuary within the birthing room. The soft geometry, the tactile materials, the quiet confidence of the design all contribute to a calmer atmosphere.

At the same time, midwives benefit from 360-degree access, carefully considered rim heights, and practical features developed through decades of collaboration with NHS maternity units and international hospitals.

This balance — emotional sensitivity combined with clinical precision — is rare.

Enduring, Not Disposable

Another parallel with Ive’s philosophy is longevity. Active Birth Pools are not temporary solutions.

They are capital investments for hospitals, designed to last for many years with minimal maintenance. Robust materials, precision fabrication, and thoughtful engineering reduce lifetime costs while maintaining performance.

They are not trends. They are standards.

Design That Feels Inevitable

The highest compliment often paid to an Apple product is that it feels obvious — as though it could not have been otherwise.

That same inevitability defines an Active Birth Pool.

When you see one installed in a maternity suite, it does not feel like equipment that has been added to the room. It feels like it belongs there. Like it was always meant to be there.

If Jony Ive had designed a water birth pool, it would not shout. It would not be ornate. It would not compromise.

It would be calm. Intelligent. Purposeful. Beautifully engineered.

It would be an Active Birth Pool.

Joint statement: Immersion in water during labour and birth – RCOG RCOM

Royal College of Obstetricians and Gynaecologists/Royal College of Midwives

Joint statement No.1 Immersion in water during labour and birth

Originally published: 2006

Summary

1.  Both the Royal College of Obstetricians and Gynaecologists and the Royal College of Midwives support labouring in water for healthy women with uncomplicated pregnancies.

The evidence to support underwater birth is less clear but complications are seemingly rare.

If good practice guidelines are followed in relation to infection control, management of cord rupture and strict adherence to eligibility criteria, these complications should be further reduced.

Background

  1. Lying in warm water gives a sense of relaxation, but whether it actually reduces pain is less certain. A perception of relaxation, pain relief, ease of movements and more holistic experience made labour in water a popular choice during the 1980s. This concept has been extended to include actual birth under water following widely quoted experience from France.1 In response to public demand, the Winterton Report recommended that all maternity services provide women with the option to labour and/or give birth in water.2
  2. Recent surveys3 show that, of 295 UK maternity units for which data on birthing pools were available, 64% had at least one birthing pool, with 20 units having two or more. There are no current data on the number of women who actually use these facilities during labour or for water birth, apart from a postal survey carried out between April 1994 and March 1996, which reported that, at that time, fewer than 1% of births in England and Wales occurred in water.4
  3. Partly in response to the Winterton Report, the Royal College of Obstetricians and Gynaecologists produced a Statement on birth in water in 1994, which was updated in 20015 and the Royal College of Midwives published a Position Paper on the use of water in labour and birth in 1994 (updated in 2000).6 Both documents endorsed the use of water in labour as a choice, provided that attendants had appropriate skills and confidence to assist women who choose to labour or give birth in water.

Labouring in water

  1. It is important to separate the evidence on benefits and risks of immersion in water during the active phase of labour from those of actual birth in water.
  2. There are considerable perceived benefits of using immersion in water during labour, including less painful contractions and less need for pharmacological analgesia, shorter labour, less need for augmentation, with no known adverse effects for the woman herself.However, there may be rare but clinically significant risks for the baby born under water. These include respiratory problems (including the possibility of fresh water drowning), cord rupture with haemorrhage, and waterborne infections.
  1. A Cochrane review by Cluett et al.7 provides the most recent evidence on water births. Overall, there was no difference found in the use of analgesia, although women allocated to immersion in water needed less epidural, spinal or paracervical analgesia. There was no significant difference in other important clinical outcomes, including duration of labour, operative delivery and perineal trauma. The same applied to the neonatal outcomes, including neonatal infection, which was rare.
  2. The evidence on timing of immersion into water during the first stage of labour was not robust enough to set criteria8 but early labour could be managed by mobilisation and other activities within a labour room rather than water immersion.
  3. Most of the available evidence, both randomised and observational, is restricted to healthy women with uncomplicated pregnancy at term, although induction of labour and previous caesarean section have been managed using water for labour and birth without reported problems.9 A randomised trial by Cluett et al.10 on women with prolonged labour found reduction in obstetric intervention following immersion in water but a higher number of babies who needed admission to the neonatal unit. Although there is clearly a need for more research, the currently available evidence does not justify discouraging women from choosing immersion in water during labour. Increasing women’s choices for analgesia and the need for maternity services to promote normality are key principles in all UK Maternity Service Framework documents and support provision of birthing pools to be made available for healthy women with uncomplicated pregnancies.11–13

Birth in water

  1. Informed choice on the benefits and risks of birth in water is clouded by the lack of good quality safety data. Although there is no evidence of higher perinatal mortality or admission to special care baby units (SCBUs) for birth in water,4,14,15 caution is advised because of small numbers, possible under-reporting of SCBU admission and exclusion of women who were in labour in water but gave birth conventionally after complications.
  2. One review identified 16 articles reporting a total of 63 neonatal complications attributable to water birth, including drowning, respiratory problems, cord avulsion and waterborne infections.16 One can argue that this anecdotal evidence is reassuring, given the thousands of women who have given birth under water in the last few decades. However, we still do not know how the low perinatal mortality and morbidity rates compare with those babies born in air.
  3. The respect for maternal autonomy and choice is important; however, it is important that any possible concerns for fetal and neonatal safety are made clear. Women who make an informed choice to give birth in water should be given every opportunity and assistance to do so by attendants who have appropriate experience. More research is needed on third-stage management in the pool, as there is currently no reliable evidence that can be used to inform women regarding the benefits and risks of experiencing the third stage of labour under water.

Achieving best practice

13 Both the Royal College of Obstetricians and Gynaecologists and the Royal College of Midwives believe that to achieve best practice with water birth it is necessary for

Royal College of Obstetricians and Gynaecologists and Royal College of Midwives Joint Statement No.1 2 of 5 organisations to provide systems and structures to support this service.

This means developing a service that is committed to responsive practices and ensuring that women are involved in planning their own care with information, advice and support from professionals.11–13

Inclusion and exclusion criteria

14 All healthy women with uncomplicated pregnancies at term should have the option of water birth available to them and should be able to proceed to a water birth if they wish. The written documentation of any discussion is essential.

Practice issues

  1. There has been much controversy over the temperature of the water of a birthing pool, with strict criteria recommending differing estimates ranging from 34 to 37 degrees Celsius17 to a Swedish study which recommended that women be encouraged to regulate the temperature of the water to suit themselves.18 Given these large discrepancies, it would be difficult to agree strict temperature restrictions. It may be of more benefit to allow women to regulate the pool temperature to their own comfort and encourage them to leave and re-enter the pool in the first stage of labour as and when they wish. Birth attendants should ensure that the ambient room temperature is comfortable for the woman and should encourage her to drink to avoid dehydration. Cord clamps should be readily available and birth attendants need to be alert to the possibility of occult cord rupture and be sensitive to any undue tension on the cord.16
  2. Monitoring of the fetal heart using underwater Doppler should be standard practice, as stated in the current National Institute for Health and Clinical Excellence guidelines.19 If there are any concerns about maternal or fetal wellbeing, the woman should be advised to leave the birthing pool and an opinion from an obstetrician or other suitably qualified person should be sought in the usual manner. There needs to be a locally agreed procedure for getting a woman out of the pool, should she become compromised, and all staff likely to be caring for the woman in the room must be familiar with the procedure and should practice it regularly in emergency drills.
  3. If the woman raises herself out of the water and exposes the fetal head to air, once the presenting part is visible, she should be advised to remain out of the water to avoid the risk of premature gasping under water.
  4. All birthing pools and other equipment (such as mirrors and thermometers) should be disposed of or thoroughly cleaned and dried after every use, in accordance with local infection control policies. Disposable sieves should be made available to ensure that the pool remains free from maternal faeces and other debris. Local information and guidelines regarding prevention of legionella build up in water supply from seldomly used pools should be obtained from local NHS trust estates and should be adhered to. Midwives should use universal precautions and follow local trust infection control guidelines.

Education, skills and training

19 Midwives should discuss antenatally the use of immersion in water in labour with all women in a low-risk category, as part of their overall discussions regarding options for pain relief, and information leaflets should be available. It is important that information on water birth is conveyed to all women in a form they can understand and in a culturally sensitive fashion, to ensure parity of access to quality services.

Royal College of Obstetricians and Gynaecologists and Royal College of Midwives Joint Statement No.1 3 of 5

  1. All midwives should ensure that they are competent to care for a woman who wishes to have a water birth and have a good understanding of the basic principles of caring for a woman in labour, and should make themselves aware of local policies and guidelines. Apart from emergency drills, training should also include emergency management of cord rupture at birth.20
  2. Midwives, managers and supervisors of midwives should ensure that training in caring for a woman who wishes to have a water birth is undertaken by midwives who undertake intrapartum care, in order to increase choice for women and promote normality and ensure quality care.11,21,22

Audit

  1. The use of birthing pools for labour and birth should be audited carefully. Data should be kept both on immersion in first stage of labour for analgesia use and separately for underwater birth. Data collected should focus on maternal wellbeing and the condition of the baby at birth, and should include usual birth outcomes, incidence of cord rupture and reasons for and rates of neonatal admission to SCBU.
  2. Data should also identify women who wanted a water birth but were transferred to conventional birth, including decision time to leave the pool for the birth of baby, the reasons for transferring to conventional care and the condition of mother and baby at transfer.
  3. Data should also be collected on women who wished to use the birthing pool but for whatever reason were unable to do so. Units should also audit ethnicity in relation to the offer of the option of water birth, to ensure that there is parity of access.

Record keeping

25 Accurate contemporaneous records should be kept, as usual. In addition, times of entering and leaving the pool should be clearly documented, including the reason for leaving the pool, if appropriate. It is important that it is recorded clearly whether the baby was born under water.

User surveys

26 User surveys of satisfaction with water birth services, including ease of access and the quality of the information given, should be carried out. Cultural acceptability needs to be reviewed to ensure equity of access and culturally sensitive services.

References

  1. Odent M. Birth under water. Lancet 1983;2:1476–7.
  2. House of Commons Health Committee. Second Report on the Maternity Services (Winterton report). London: HMSO; 1992.
  3. Dr Foster Good Birth Guide [www.drfoster.co.uk/home/birth2005.asp].
  4. Gilbert RE, Tookey PA. Perinatal mortality and morbidity among babies delivered in water: surveillance study and postal survey. BMJ 1999;319:483–7.
  5. Royal College of Obstetricians and Gynaecologists. Birth in Water. RCOG Statement. London: RCOG; 2001.
  6. Royal College of Midwives. The Use of Water in Labour and Birth. Position Paper no. 1a. London: RCM; 2000 [www.rcm.org.uk/data/info_centre/data/position_papers.htm].
  7. Cluett ER, Nikodem VC, McCandlish RE, Burns EE. Immersion in water in pregnancy, labour and birth. Cochrane Database Syst Rev. 2004;(2):CD000111.
  8. Eriksson M, Mattson L, Ladfors L. Early or late bath during the first stage of labour: a randomised study of 200 women. Midwifery 1997;13:146–8.

Royal College of Obstetricians and Gynaecologists and Royal College of Midwives Joint Statement No.1 4 of 5

  1. Brown L. The tide has turned: audit of water birth. Br J Midwifery 1998;6:236–43.
  2. Cluett ER, Pickering RM, Getliffe K, St George Saunders NJ. Randomised controlled trial of labouring in water compared with standard management of dystocia in first stage of labour. BMJ 2004;328:314.
  3. Department of Health. The National Service Framework for Children and Young People. Maternity Services. Standard 11. (NSF) 2004. London: Department of Health [www.dh.gov.uk/assetRoot/04/09/05/23/04090523.pdf].
  4. Scottish Executive. A Framework for Maternity Services in Scotland. Edinburgh: Scottish Executive; 2001 [www.scotland.gov.uk/library3/health/ffms-00.asp].
  5. Welsh Assembly Children’s Health and Social Care Directorate. National Service Framework for Children, Young People and Maternity Services in Wales. Cardiff: Welsh Assembly Government; 2005 [www.wales.nhs.uk/sites/documents/441/ACFD1F6.pdf].
  6. Woodward J, Kelly SM. A pilot study for a randomised controlled trial of water birth versus land birth. BJOG 2004;111:537–45.
  7. Geissbuehler V, Stein S, Eberhard J. Waterbirths compared with landbirths – an observational study of nine years. J Perinat Med 2004;32:308–14.
  8. Anderson T. Umbilical cords and underwater birth. Practising Midwife 2000; 3(2):12.
  9. Anderson T. Time to throw the waterbirth thermometers away. MIDIRS 2004;14(3):370–4.
  10. Geissbuehler V, Eberhard J, Lebrecht A. Waterbirth: water temperature and bathing time –mother knows best! J Paediatr Med 2002; 30:371–8.
  11. National Institute for Clinical Evidence. The Use of Electronic Fetal Monitoring: the useand interpretation of cardiotocography in intrapartum fetal surveillance. London: NICE; 2001 [www.nice.org.uk/pdf/efmguidelinenice.pdf].
  12. Grunebaum A, Chervenak FA. The baby or the bathwater: which one should be discarded? J Perinat Med 2004;32:306–7.
  13. Nursing and Midwifery Council. Midwives Rules and Standards. London: NMC; 2004 [www.nmc-uk.org/aFrameDisplay.aspx?DocumentID=169].
  14. Nursing and Midwifery Council. The NMC Code of Professional Conduct: standards for conduct, performance and ethics. London: NMC: 2004 [www.nmc- uk.org/aFramedisplay.aspx?documentID=201]

A comparison of water births and conventional vaginal deliveries

Otigbah CM; Dhanjal MK; Harmsworth G; and others, (July 2000).

European Journal of Obstetrics and Gynecology and Reproductive Biology , vol 91, no 1, July 2000, pp 15-20.

Setting, participants, design and aim:

The study took place in a district general hospital over a five year period, 1989-1994 and involved a total of 602 mothers. A retrospective case-control study which analysed data on 301 mothers who had a water birth and another 301 who had a normal land birth.

The aim was to explore the effects of water immersion on labour and birth, as compared with normal land birth.

Method: The study centre had several pool selection criteria which accepted women who were considered to be at low risk of complication for the pool.

They were required to have: * no medical or obstetric problem; * a gestation of at least 38 weeks with a normal sized fetus; * cephalic presentation; * clear liqour if membranes were already ruptured; * a reactive admission cardiotocograph.

The controls were selected from the unit’s audit data, as the next parity matched woman who was low risk, had a normal birth and did not have labour augmentation.

The variables compared and analysed included: * labour length; * analgesia uptake; * Apgar scores; * maternal complications – namely perineal trauma, postpartum haemorrhage and infection; * neonatal complications – namely shoulder dystocia, admission to special care baby unit (SCBU) and infection.

Data were analysed using the Chi-squared test to compare proportions, and Student’s t test to compare means. Any difference was considered significant if the P value was <0.05. Results: * Primigravidae who had a water birth had a significantly shorter first stage (P <0.05) and second stage (P <0.005) of labour.

The total labour length was 90 minutes shorter; * Water birth mothers, whatever their parity, used significantly less opioid pain relief, either alone or in addition to entonox – 1.3% compared to 54% of the controls (P <0.0001).

A total of 38% water birth women had no analgesia compared to 8% of the control group (P <0.0001); * Water birth mothers had significantly fewer episiotomies – 5%compared to 25% (P <0.0001), although they had more vaginal, 1° and 2° perineal tears overall – 53% versus 39% (P <0.001).

Water birth primigravidae had more intact perinea – 41% compared to 36%, although this was not statistically significant; * Fewer postpartum haemorrhages occurred among water birth mothers – 1.3% versus 2.7%; * One case of maternal pyrexia was reported on a multiparous water birth woman who was treated with antibiotics; she had no positive cultures on subsequent sampling; * No significant difference was reported between the groups in the mean Apgar scores at one and five minutes; *

Two water birth babies were admitted to SCBU with low Apgars.

In one case there was a true knot in the umbilical cord and the other followed a difficult delivery with an unexpected compound presentation; * Five babies in the water birth group and four in the control group had shoulder dystocia; * No neonatal infections were reported.

Abstract writer’s comments:

This is clearly an interesting and worthwhile study which includes data on a good size sample of mothers and babies.

A key strength is the analysis and presentation of the data by parity as often findings relating to primigravidae and multigravidae are amalgamated, despite the influence of parity on factors such as use of analgesia, labour length and type of delivery.

The authors acknowledge the limitations of a non-randomised water group sample.

It would have been interesting to have collected information relating to the social class of pool users, as there is an assumption among health professionals that birthing pools attract greater interest among middle class women, but I know of no evidence to support this view.

The researchers report a shorter labour for water birth primigravidae but do not mention the frequency of vaginal examinations, or whether the second stage was timed when the presenting part was visible, making the precise process of how they timed these labour stages unclear.

The effect of water immersion on analgesia uptake appears striking.

The authors suggest that an influencing factor may have been the continuous midwifery care, often by a known midwife, for pool users, as opposed to an intermittent midwifery presence by a midwife unknown to a mother before her labour.

There is, however, no mention whether any facilities such as beanbags, birthing balls, rocking chairs or floor mattresses were available to women who did not use the pool, apart from presumably a delivery bed.

It is therefore not known whether these women were encouraged to adopt comfortable positions and be as mobile as possible throughout labour.

The practice of maximising maternal mobility has been shown to reduce the perception of pain and thus the uptake of analgesia.

Whilst it is reassuring that fewer episiotomies were performed on water birth women, nonetheless, fifteen still had one!

It would be interesting to know something about the study centre’s approach to care during the second stage regarding pushing techniques and time perimeters, as this could have influenced the incidence of both tears and episiotomies.

The researchers note that ‘particular care was taken to ensure controlled delivery of the head’ (p16) but do not explain how, ie if the midwife touched the head and perineum or not.

Besides, tears often occur with the birth of the shoulders.

Comparison was made between the groups on the incidence of postpartum haemorrhage, but no mother appeared to have a completely physiological third stage because the cord was clamped and cut promptly after the birth, which disturbs the physiology, and the placentas were delivered out of the pool.

The rationale for leaving the pool was to estimate blood loss more accurately – a difficult thing to achieve in or out of water.

A second reason was the totally unproven risk of water embolism.

This study reported no adverse effect for mothers or babies associated with water immersion during labour and birth and forms a useful basis for future research.

Water birth: a review of 848 deliveries and a comparison with other delivery positions

Thoeni A; Holzner J, (2002). International Confederation of Midwives. Midwives and women working together for the family of the world: ICM proceedings CD-ROM Vienna 2002. The Hague: ICM , 2002. 7 pages.

Objective:

The object of our study was to analyze 848 consecutive water births and to compare them with two other delivery positions.

Methods:

We compared 848 water births, 493 deliveries in the traditional bed, and 172 deliveries on the delivery stool.

Duration of labor, rates of episiotomies and lacerations, arterial cord blood pH, base excess, analgesic requirements, and postpartum maternal haemoglobin levels were evaluated.

Results:

The first stage of labor was significantly reduced in primiparas with water birth compared with the other delivery positions (386 vs. 477 min., respectively).

There were no differences in the duration of the second stage (32 vs 39 min.).

The low episiotomy rate with the water births (1% compared with 18% and 8% for the other two positions) was not associated with an increased rate of perineal lacerations (23% in all three groups).

Of the primipara, 59% had no lacerations with water birth compared with 36% and 46% for the other two positions, respectively.

No woman with water birth required analgesics.

There were no differences among the groups in arterial cord blood pH or postpartal maternal haemoglobin level.

Conclusion:

Our results suggest that water birth is associated with a significantly shorter first stage of labor, lower episiotomy rate and perineal lacerations, and reduced analgesic requirements compared with other delivery positions.

Water birth is safe for the mother and fetus-neonate if candidates are selected appropriately.

Study confirms… Women who labour in water have lower rate of epidural analgesia

Randomised controlled trial of labouring in water compared with standard of augmentation for management of dystocia in first stage of labour

Objectives:

To evaluate the impact of labouring in water during first stage of labour on rates of epidural analgesia and operative delivery in nulliparous women with dystocia.

Design Randomised controlled trial.

Setting University teaching hospital in southern England.

Participants 99 nulliparous women with dystocia in active labour at low risk of complications.

Interventions Immersion in water or standard augmentation for dystocia (amniotomy and intravenous oxytocin).

Main outcome measures:

Primary: epidural analgesia and operative delivery rates.

Secondary: augmentation rates with amniotomy and oxytocin, length of labour, maternal and neonatal morbidity including infections, maternal pain score, and maternal satisfaction with care.

Results:

Women randomised to immersion in water had a lower rate of epidural analgesia than women allocated to augmentation (47% v 66%, relative risk 0.71 (95% confidence interval 0.49 to 1.01), number needed to treat for benefit (NNT) 5).

They showed no difference in rates of operative delivery (49% v 50%, 0.98 (0.65 to 1.47), NNT 98), but significantly fewer received augmentation (71% v 96%, 0.74 (0.59 to 0.88), NNT 4) or any form of obstetric intervention (amniotomy, oxytocin, epidural, or operative delivery) (80% v 98%, 0.81 (0.67 to 0.92), NNT 5).

Conclusions:

Labouring in water under midwifery care may be an option for slow progress in labour, reducing the need for obstetric intervention, and offering an alternative pain management strategy.

(Extract from abstract of Randomised controlled trial of labouring in water compared with standard of augmentation for management of dystocia in first stage of labour by Elizabeth R Cluett, Ruth M Pickering, Kathryn Getliffe, Nigel James, St George Saunders published in British Journal of Midwfery January 26, 2004)

Evidence on the safety of water birth

9 February 2015

Evidence Based Birth – Rebecca Dekker

In April 2014,  waterbirth—an alternative method for pain relief in which a mother gives birth in a tub of warm water—made national headlines.

The event that pushed water birth safetyinto the spotlight was a joint Opinion Statement from the American Congress of Obstetricians and Gynecologists (ACOG) and the American Academy of Pediatrics (AAP), denouncing the practice.

In their opinion statement, ACOG and the AAP firmly admonished that waterbirth should be considered an experimental practice that should only occur in the context of a clinical research study.

Their conclusion, which echoed a previous AAP Opinion Statement from 2005, was based on their opinion that water birth does not have any benefits and may pose dangers for the newborn.

In response, the American College of Nurse Midwives (ACNM),(Midwives 2014) the American Association of Birth Centers (AABC), and the Royal College of Midwives (RCM) all released statements endorsing waterbirth as a safe, evidence-based option.

Meanwhile, the AABC released preliminary data from nearly 4,000 waterbirths that occurred in birth centers all over the U.S., supporting water birth as safe for mothers and infants.

Despite the response from midwifery organizations and the AABC, hospitals all over the U.S. began suspending or shutting down their waterbirth programs.

At St. Elizabeth’s Regional Medical Center in Lincoln, Nebraska, mothers and families organized rallies and started a change.org petition to bring waterbirth back.

All of this controversy left us with these questions— Is the ACOG/AAP statement based on a complete and accurate review of the literature?

What is the evidence on waterbirth?

Is it safe?

Does it have any potential benefits or harms for mothers and infants?

These are the questions we will address in the Evidence Based Birth article on the evidence on waterbirth.

This article was published July 10, 2014, by Rebecca Dekker, PhD, RN, APRN
© Evidence Based Birth, All Rights Reserved.

Click here for a copy of Rebecca Dekker’s paper on the safety of water birth

Water VBAC: exploring a new frontier for women’s autonomy

McKenna JA; Symon AG, (2014). Midwifery , vol 30, no 1, January 2014, e20-5.

BACKGROUND: although Vaginal Birth After Caesarean section (VBAC) has been promoted successfully as one means of reducing the caesarean section rate, the practice of VBAC using water immersion (Water VBAC) is restricted.

Very little valid, reliable research evidence is available on this birth method, although initial small-scale audits indicate that Water VBAC has no adverse effect on maternal and neonatal outcomes.

METHOD: in-depth semi-structured interviews were carried out with a purposive sample of eight women who had undergone Water VBAC in one midwife-led unit.

The interviews aimed to explore their reasons for requesting this birthing method, and their experience of the process. An interpretative phenomenological analytical approach was adopted.

FINDINGS: the women pursued Water VBAC for two main reasons: in order to prevent a repeat of the obstetric events that previously led to a caesarean section, and to counteract their previous negative birth experiences.

The women reported improved physical and psychological outcomes from their Water VBAC experience when compared with their previous experience of caesarean section.

Three main themes emerged: ‘minimising’, ‘maximising’ and ‘managing’. Water VBAC entailed an attempt to minimise the medicalisation of the women’s childbirth experience.

This was achieved by limiting medical staff input in favour of midwife-led care, which was believed to minimise negative physical and psychological experiences.

Correspondingly, Water VBAC was perceived as maximising physical and psychological benefits, and as a means of allowing women to obtain choice and assert control over their labour and birth.

The women planning a Water VBAC believed they had to manage the potential risks associated with Water VBAC, as well as manage the expectations and behaviour of friends, family and the health care professionals involved in their care.

CONCLUSIONS: for the women participating in this research, actively pursuing Water VBAC constituted a means of asserting their autonomy over the childbirth process.

The value accorded to being able to exercise choice and control over their childbearing experience was high.

These women’s accounts indicated that information-giving and shared decision-making require improvement, and that inconsistencies in the attitudes of health care professionals need to be addressed.


Nothing helps mothers cope with pain in labour more effectively

Water birth pools play a vital role in helping mothers experience physiological labour and natural birth.

Nothing helps mothers cope with pain more effectively.

If mothers are not going be reliant on analgesia for pain relief they need other options.

Mothers who enter a pool of warm water in established labour find that they are better able to cope with the pain.

Immersion in warm water has been unequivocally proven to be of great benefit both physiologically and psychologically.

Women have a greater sense of fulfillment and accomplishment and babies experience a non-traumatic birth.

Aside from the obvious benefits to mothers and babies, midwives experience greater job satisfaction and hospitals save money & optimise resources.

Nearly a third of women benefited from the use of a water birth pool in the UK in 2014 (National Maternity Survey 2014).

With up to 60% of mothers open to natural birth now is the time to consider making this safe, effective, low cost option more widely available.

On land mothers contend with the force of gravity which limits movement as labour progresses and they tire.

Many women do not have the fitness to maintain upright postures for lengths of time. (Gupta JK, Hofmeyr GJ, Smyth R 2007).

Mothers who are overweight or obese are often unable to cope with the physical demands.

The transition from the land to water helps revive & energise mothers giving them a new lease on life and sense of purpose.

The buoyancy of water supports the mother reducing her relative weight by approx. 33% (Archimedes Principle).

This allows her to move in ways not possible on land.

To explore and benefit from the postures natural to labour & birth .

The calming, relaxing effect of the warm water promotes the flow of oxytocin.

This powerful hormone plays a huge role in childbirth.

It causes the uterus to contract and triggers the ‘fetal ejection reflex’.

Immersion in water has a beneficial physiological effect on hormone secretion, including oxytocin surges which can advance dilation and stimulate contractions (Odent 2014).

Excerpt from “The Waterbirth Book”: by Janet Balaskas

   The introduction of birthing pools in the UK began in the late 1980’s and is one of the greatest innovations to happen in natural childbirth. More than 150 hospitals in the UK now (2001) have at least one installed pool and hundreds of portable pools are also in circulation. The use of water for labour and birth is increasing and has been under intense scrutiny in the last 10 years. The outcomes of the research have so far, been positive. The help of water to enable more women to give birth naturally is very relevant at this time, when one in 5 babies in the UK is born by caesarean section.

   The invigorating and therapeutic value of water is well know to all of us – from our daily bath or shower to mineral springs, saunas and spa’s, rivers, oceans – all places we go to for healing and regeneration. These qualities are brought into the labour room when we introduce a pool of warm water. This is a wonderful way to transform the atmosphere in a hospital and to encourage normal birth physiology.

   Long before there was modern plumbing, water was used as a birth aid in many cultures. It’s soothing, cleansing, and healing properties were used to help women in labour and it was also used as a birth stimulant.

  • In New Guinea – Gahuka women gave birth by the river. The sound of the water help the mothers concentration and the flowing movement of the water helps the movement of the baby inside. 
  • African women – Squat over steaming hot rocks to soften the perineum 
  • Gautemalan midwives – gave women relaxing steam bath massages 
  • Finnish women laboured in steaming saunas 
  • Japanese women in remote fishing villages gave birth in the sea 
  • Maories and South Pacific Islanders – Hawaiians – have oral traditions of labour and birth in water. In addition to gravity, warm water is another of nature’s elements which has enormous power to help you during your labour. It is a simple yet powerful way to relax deeply and can be the key to an easier labour.

The benefits of using a birth pool

   Water is a feminine element. It is buoyant and soft and carries your body’s weight. As soon as you enter the water, the warm, sensual sensations on your skin remind you that your labouring body is beautiful, powerful, and sensual. Although this is not the case for everyone, the majority of women comment that they were surprised by how wonderful and relieving it felt when they first got into the pool.

   Water pools help many women to cope better with pain and enhances those passions and deep emotions which are an integral part of a healthy birth. For many women a birth pool provides an alternative route to an epidural and can be the key to a physiological birth. The water is not likely to take away the pain, but it can make a tremendous difference to your ability to relax and may well make the pain more bearable.

   Studies have shown that endorphine levels may go down in a birth pool – a sign that pain levels decrease. A birth pool is something to try before considering an epidural or other form of medical pain relief. You can always change your mind if you need to.

   The buoyant effect of the water completely supports your body’s weight. This gives you a feeling of physical liberation – like being in warm ocean. Resting between contractions is much easier, because being in the water is so comfortable and relaxing. This helps tremendously to conserve your strength and energy, so you are less likely to become fatigued or exhausted.

   In the pool you are in your own womblike space – you are in charge. It’s more difficult to disturb or distract you. A birth pool represents a sanctuary from what some women experience as the menace of obstetric routines. In water your body is your own territory – your birth attendants need your consent to get close to you.

   The water’s buoyancy also helps enormously to make you more comfortable in upright positions. You can move more easily and spontaneously help your baby to descend and rotate by yourself.

  You will be surprised to find that it’s much easier, for example, to squat in water. Even women who find squatting difficult on land, can often do so comfortably in water — with the added benefit that this position makes a lot more space in the pelvis for your baby to descend.

   Once in the pool, you are unlikely to notice how much time has passed. Many women say that the world beyond the rim of the pool seems to disappear.This increased sense of privacy in the pool helps you to concentrate on working through your contractions without any distractions.

   The relaxing environment helps you to let go of what is happening around you and to focus your awareness inwards on the work your body is doing and surrender to the rhythm of your labour.

   The oxytocin wave – how entering a birth pool effects hormone secretion.

   Water birth pioneer, Dr Michel Odent, in his latest updates on water birth, suggests that there is a correlation between the findings of physiologists on the effects of water immersion on hormone secretion and the observations of midwives that labours tend to slow down when the woman enters the pool too early.

   He suggests that immediately after a woman enters the pool, there is a surge of oxytocin which stimulates contractions and results in rapid dilation. However this effect is short lived and after about 1.5 – 2 hours, oxytocin secretion reaches a peak and begins to slow down. The timing of when you enter the pool therefore becomes important.

Practical tips and guidelines

   When to get in – If you are planning to use a birth pool it’s best to stay out of the water in the latent phase of labour. At this time, using upright positions, movement and breathing awareness, complementary therapies or TENS can help you to get into a comfortable rhythm with your labour (see Issue nos 8 and 10)

   .In mid labour, when you are about 5 – 6 cms dilated – around the time when many women ask for pain relief – is the best time to think about entering a birth pool (our experience also shows that getting in too early can slow down contractions). Getting in late means that you are likely to be close to full dilation at the crest of the oxytocin wave.

   In a long labour, contractions may slow down in the pool and then it is best get out and use the help of gravity on dry land for a while, resting in the pool later if you get tired.

   The golden rule of water labour and birth – if progress is slow in water try land, if slow on land try water

   The water temperature is important. Because your baby relies on you for temperature regulation and is one degree warmer than you are, the temperature of the water should never exceed 36C in labour and is best at 36C or 37C for the birth itself. When you feel cold, hormone secretion is inhibited and this will weaken your contractions. If you feel warm enough but not hot, you have probably got it just right for you. Measuring the temperature with a water thermometer is important, but don’t worry about it being too exact! How you feel is the best test.

   The ideal water temperature range in labour is 32C-36C and for birth around 36C-37C

  Water depth – You also need to make sure that in labour the water is deep enough to cover your belly and allow your shoulders to be exposed, so you can sweat and loose heat if you need to. Immediately after the birth there is often a need to remove some of the water, so you can breastfeed in the pool with the water keeping your baby’s body warm with his or her head out of the water at breast level.

   Birthing rooms with a pool are warm and humid, so make sure that there is good ventilation and the room is not over heated. Plenty of drinking water for everyone is also a good idea, as a humid atmosphere is dehydrating.

   Your partner can sit right beside you in the pool or even get in with you to massage, hold and comfort you. As you share the same environment, there is no increased risk of infection if your partner enters the pool! So it’s a good idea to have a swimsuit ready for your partner, just in case.

    If this idea doesn’t appeal to you, it’s still very easy to share the intimacy of labour with your partner seated nearby, outside the pool. Having a low stool or a birth ball beside the pool is useful for your partner and for the midwife. Many women value having all the space in the pool to themselves, while others enjoy the comfort and support of relaxing against their partner’s body in the water.

* The Midwife’s practise

   It is a transforming experience for a midwife to be around women in a birth pool. It is understandable that midwives contemplating their first water births may be nervous and feel insecure. Until very recently their education would not have included Water Birth. The health authority generally prefer two midwives to be at a water birth.

   The fact that you are in water does not greatly change the midwife’s usual practice – in fact it makes it considerably easier, because the warm water helps you to cope better by yourself. She will need to make the normal observations of both your and your baby’s well being and the progress of your labour.

   Vaginal exams can be kept to a minimum and can be done when necessary in the pool.

   Monitoring the baby’s heartbeat at regular (probably half hourly) intervals is important to ensure that there is no foetal distress. However the midwife needs to be sensitive to avoid disturbing you too much – a waterproof sonic aid allows monitoring under water so you do not need to change your position or break your concentration. Alternatives are a stethoscope, a long stemmed pinnard or a regular sonic aid with the transducer in the finger of a long glove. A non water proof sonic aid may mean that you need to float close to the edge or sit up on the edge of the pool.

    The midwife will check your body temperature and blood pressure at times and keep an eye on the temperature of the water.

  When a birth pool is introduced into a hospital birthing room the environment is transformed into one which is much more homelike. The pool invites the mother to relax and there is usually no delivery bed in sight. The atmosphere of fear and danger are eradicated and everyone’s expectations about what will happen are different. There is a deliberate attempt to induce feelings of confidence and relaxation in the mother.

   This makes a hospital environment more attractive if you want a physiological birth with the security of obstetric support close at hand. At a home birth the environment is even more ‘hormone enhancing’ when a birth pool is available and there is a powerful resource to help you cope with pain in the active stage of labour.

   In the pool room it’s a good idea to dim the lights or draw the curtains to reduce stimulation so that there is a peaceful, calm and intimate atmosphere. When you can really relax in labour, as a birth pool helps you to do – you can let go more easily and things usually go well. It’s not a problem if you want or need to get out for the birth. You will have achieved the most important objective, which is a more comfortable labour, without the need for drugs or interventions.

How to use Water during Labour:
How long and When to Stay in the Water

   The attraction to water and the timing of using the water pool is very individual and varies from one woman to another and one labour to another. If pre-labour contractions are intense and there are long runs of contractions prior to the onset of established labour, water can be extremely soothing.

   After staying in water for some time the contractions may diminish, giving you an opportunity to rest and maybe even fall asleep, thus conserving your energy for the subsequent labour and birth.

   When labour is well established, the timing of using the pool once again shows a wide individual variation. After entering the water dilation is often rapid during the first h our. It is preferable to keep the pool in reserve for the second half of labour when the contractions are intense and the periods of rest shorter.

   This is when water is most powerful in assisting dilation and shortening labour. However, you might need the comfort of water from quite early on in labour and want to spend hours in the pool prior to the birth itself. In this instance you can go in and out of the pool and alternate between being in water and being on land.

   When the pool is used early, mothers sometimes tire of the water and they may not want to use this valuable resource later on when contractions become more painful and intense. Getting in too early may slow down contractions and prolong labour.

   Provided the correct water temperature is maintained and your temperature is monitored, it is safe to stay in the water as long as you like. The depth of the water is also important. The more your body is submerged the more help you will get from buoyancy.

   However, women’s preferences vary. While some like the water to be as deep as possible, others are more comfortable in less water.

   When you leave the pool it is advisable to have plenty of large towels available so that you can dry yourself completely. There should also be a heater in the room so that if you feel cold the temperature can be raised quickly.

Movements and Positions

   There are bound to be times when you prefer to need to be outside the pool on dry land during your labour, for example, if labour is not progressing well in water or if you do not feel like being in water. In early labour, as your contractions are beginning to intensify it is essential to make the most of the help of gravity.

   You can do this by using positions such as standing, sitting or squatting during your contractions and resting between them. Follow you instincts when moving during labour and you will find that these positions occur spontaneously.

   Most women use a variety of positions. Some prefer one or two while other women are more restless and change position frequently. During contractions movements such as circling your hips or rocking your pelvis can help to dissipate the pain.

   There are many ways to make yourself comfortable in upright positions so that you do not tire yourself out. It i s useful to bear in mind that the more vertical or upright your body is the more help you will get from gravity. When standing or walking you may find it helpful to lean forward onto a wall or to be held by your midwife or partner during the contractions.

   When kneeling make sure your knees are resting on a soft surface and use a firm beanbag or pile of cushions to make yourself comfortable to relaxing between the contractions and to make sure that your trunk stays fairly vertical.

   You may want to rest lying on your side, well propped up by cushions between contractions. For squatting, a low stool is very helpful and makes squatting less tiring. You can also hold onto a firm support or squat between your partner’s knees while he sits on a chair.

   Sitting on the toilet with your knees spread apart is very comfortable in labour and for many women the privacy of the bathroom is appealing. Here you can fill the basin and splash yourself with water if you want to and enjoy the sound of running water from the tap.

Entering the Pool

    Once you enter the pool, water powerfully increases your sense of privacy and adds a new dimension to the range of positions and movements you can use. The buoyancy of the water makes it much easier to move and change position and you will find that you will change positions instinctively and movement will occur spontaneously.

   It’s helpful to experiment in the pool or in a swimming pool in the days before your labour begins, and to submerge your head under water at times so that you feel completely familiar and at ease in the water. This is a way to block out sounds which are distracting.

   You will find that most of the movements and positions you can use on land can be used in water during contractions.

    Floating between contractions is a wonderful way to relax, and wetting your hair and going under the water at times reduces outside stimulation and sounds and helps you to let go. there is a wonderful sensuous quality to being in water in labour.

   It is like reconnecting with the original primal feelings you had in the womb. This is a tremendous aid to surrendering to the birth energy and to letting your body’s natural rhythms take over.

   There is no need to do anything. It will help if the room is darkened and you have enough privacy. With the water as deep as possible you can use your ability to relax and quieten your mind to sink deeply into your labour.

   Some women remain quite still in the water, changing positions occasionally, whereas others like to move a lot, rolling from front to back like a mermaid, or a dolphin.

  Movements and position changes will happen without you needing to think about them. Between contractions you can rest and benefit from the restorative and energising properties of the water.

    You can sink into its nurturing and feminine energy and accept its power to relax you. If you can let go completely you will rest, your energy will recharge and you will enter into a kind of timeless ocean of bliss between the contractions.

The End of Labour

   As the birth of the baby approaches contractions will be at their most intense. They will be longer (lasting up to sixty seconds) and closer together so that the intervals are very brief.

   This is the peak of labour when the ocean waves are high and turbulent, following upon each other with relentless frequency. The end of labour is usually referred to as ‘the transition stage’. You are close to full dilation and your baby’s head is about to emerge through the dilated cervix into your vagina ready to be born.

   It is normal to feel fearful at this stage. This is the time when you are likely to wish you could get away or have an epidural anaesthetic, when your courage and strength may be at a very low ebb.

   You may feel angry and irritable or despairing, as if you are exhausted and almost close to death. The breaks between your contractions may give you little respite before the next contraction looms large, like a tidal wave.

   It is very helpful to make the most of the respite between contractions and rest and relax deeply, almost sleeping until the next wave begins. this can restore and replenish your energy surprisingly – even though the gaps are short.

   The fear which is common at this stage has an important role to play. It triggers off a surge of adrenalin secretion, the ‘fight or flight’ hormone which stimulates the reflexive contractions which expel your baby during birth.

   At this time you are on the threshold of giving birth. This is when the powerful demon goddess takes over as the urge to bear down and give birth arises.Outside stimulation including sound and light or touch should be minimal, as you go through these last demanding contractions without distraction.

   You will be in an altered state of consciousness, deep inside your labour. Anyone who is present will need to be very discreet and avoid disturbing you, by watching, talking or by being falsely reassuring or anxious.

   This time can also be difficult for birth attendants and partners who may feel an intense desire to do something to help. However, their calm silence can be a source of strength, reassurance and encouragement as you go through the intensity of the end of labour.

   Some women are deeply afraid of the birth at a subconscious level and may experience difficulty in surrendering to the power of these final contractions. Being in warm water helps to let go. Often this intense phase passes very quickly or has a kind of timeless quality.

   However, if transition is long, you can keep up your energy by sipping water or dilute fruit juice. Most women feel very thirsty when the adrenalin response begins and need to drink a glass or two of water. The bach flower remedy called ‘Rescue Remedy’ can be very helpful.

   At this time near to the birth, the sounds emerging from the birth room tend to be loudest, so there is no need to try to be quiet. You will be in your full power, so feel free to roar like a lioness if you need to .

   Noise will help you to find the power to assist your baby to come down as your body opens to give birth. Your bowels empty spontaneously as your baby’s head presses down and you may need to retch as the expulsive reflex begins.

   Some women feel shy or inhibited about letting go to to these natural reflexes in the presence of other people. It helps to remember that your midwife is used to this and will welcome these events as a sign that the birth is imminent. Whatever happens your concentration will be focused deeply on the power of your contractions with moments of brief but blissful serenity in between them.

   At this stage you may feel that you are almost drowning in a sea of contractions. You may wish to leave the water, or alternatively surrender to the power in the weightlessness which its buoyancy allows you.

   Whether you are in or out of the pool, it is best to use the positions which feel most comfortable, making sure that you can relax, with your body supported between contractions. The water level in the pool should be as high as possible to offer you maximal support.

   As birth approaches, many women prefer kneeling. This position helps to give you a sense of control over the intensity of the contractions and makes it easier to relax or even sleep in the brief intervals between them without moving or changing position.

   At the very end of labour, contractions often slow down and the resting phases may lengthen. The contractions which expel our baby from the womb usually begin around the time full dilation of the cervix is reached.

   In some women the urge to push may start before dilation is complete and sometimes, on the other hand, there is a break or resting period before expulsion begins. This will feel like a lull, a period of time where suddenly the waves become still and the sea becomes calm.

   The lull may continue for quite a while before the pushing urge begins. On the other hand you may begin to feel the urge to bear down much earlier. Whatever happens you can trust in the wisdom of your body and surrender to its urges. Soon your baby will be born!

Giving birth in water

   When you feel you are ready to push and give birth to your baby you may decide to leave the pool, to feel the solidness and security of the ground underneath you. Or you may prefer to remain in the water for the second stage. Some women have a strong urge to get out, while this possibility may not even occur to others.

   In some places, especially when the midwives are new to water birth, pools are used only for labour and all women are asked to get out for the birth.

   The benefits of using a pool during labour are the main reason to consider using the help of water. If you are asked to leave the pool to give birth, it is still well worth getting in for labour. The birth often happens very soon after the mother leaves the pool at the end of active labour in water.

   A water birth is appropriate when labour has progressed well and when there is no sign of a potential problem during labour. When this is the case, studies have shown that giving birth in water is as safe as any other way of giving birth. A water birth is a soft and gentle way for a baby to be born and welcomed to the world.

   Birth in water is a ‘low risk’ option. It is only recommended when the baby’s heart tones are strong throughout labour and second stage and when there are no complications. That’s why your midwife will want to listen in to your baby every half hour or so during labour, and this is done even more frequently in the second stage.

   In places where a birth pool is encouraged as an option, women rate the experience of labour and/or birth in water very highly (one study showed that just over 90% of women who had a water birth rated it as ‘excellent’) and research has shown that fewer women need interventions.

   Using a birth pool, whether just for labour or for the birth itself, is an effective and harmless way to reduce the risk of complications and to increase your chances of a natural birth.

* The dive reflex – a major discovery

   The evidence of many thousands of water births all over the world has shown us that when the circumstances are appropriate, babies can be born safely into warm water at around body temperature and brought immediately to the surface to breathe. This is due to an innate reflex in human newborns called the ‘dive reflex’.

   This was first discovered by the Russian researcher Igor Tjarkovsky in the 1960’s and was first described in the medical literature by the eminent neonatal physiologist Paul Johnson, from the John Radcliffe Hospital in Oxford. He is an expert on the first breathing responses of the newborn. In March 1996 he published an article ‘Birth under water- to breathe or not to breathe?’ in the British Journal of Obstetrics and Gynaecology. The dive reflex was also researched by the German obstetricians Eldering and Selke and their findings are published in the book Water Birth Unplugged.

   Johnson point out that the breathing reflex in a newborn baby is stimulated at birth, at the moment when the sensory chemoreceptors around the babies nose and mouth first come into contact with air.

   When the head emerges into warm water at body temperature during a water birth, this stimulation does not occur before the face emerges from the water. Under water, the dive reflex causes the air passages in the larynx to close and any water entering the nose or mouth is swallowed rather than inhaled.

   The only time the dive reflex may be overridden, causing the baby to gasp under water, would be if there was severe foetal distress. This is why diligent monitoring to rule out this possibility is an essential feature of a water labour or birth. Labour and birth in water tends to minimise stress and relax the birthing mother. This in itself is a preventative of foetal distress.

   However the death of a baby can occur on rare occasions with any method of birth. Infant mortality during water births that are skilfully managed, appears so far, to be exceptionally low, comparative with the national rate for low risk mothers (which is very low in the UK).

Birth in water

    The possibility of your baby being born in water may be very appealing and a water birth is certainly a beautiful, gentle way to welcome your baby. However it may not be appropriate at the time, so try to avoid having too much of preconceived idea about this. Even if you would love to have a water birth, try to keep an open mind.

   Water births happen when second stage progresses well and the mother does not want to leave the pool.

   The baby usually emerges without difficulty, sometimes the head and body are born in one contraction. Often though, the head is born first and there is a break between contractions when just the baby’s head is out. The dive reflex is working while the head is under water, so the baby will not inhale the water. He or she is still receiving oxygen from the placenta through the umbilical cord. The placenta remains attached and working until the baby is breathing independently.

   Usually with the second contraction, after the head has emerged, the shoulders and the body emerge next baby is born into the water. The buoyancy supports the baby’s body in the water and you may see the babies eyes open under water. The dive reflex is still working. The baby is then gently ‘caught’ and brought to the surface immediately.

   This is done in slow motion, without rushing, within about 10 seconds after the baby has been born, which gives the baby enough time to relax and uncurl in the water on the way out. The baby is lifted out in time to take the first breath, when the mouth and nose come in contact with the atmosphere.

   With this gentle way of birth, breathing usually starts slowly with the baby taking frequent little breaths instead of one big gasp. Within minutes breathing is established and it takes about 10 -15 minutes before the cord stops pulsating altogether and the transition to lung breathing is completed.

   Holding your baby in your arms for the first time, is one of the most wonderful experiences you will ever know. No doubt you will kiss and caress your baby and hold him or her close to your heart. Take your time to welcome and enjoy your baby in privacy – this first bonding is the beginning of a love affair which will last a lifetime!

After the birth

   While welcoming your baby you can stay in the pool and hold your baby in your arms, close to the breast. Your partner or birth attendants may need to alter the depth of the water to ensure that your baby’s body is submerged and kept warm, while the head is able to reach the breast easily above the water surface.

   This is a good moment to put on a heater so the room is very warm when you leave the pool. Facilitating the first undisturbed contact between mother and baby is what is most important now – ‘daddy bonding’ time happens a little later after the placenta has emerged safely. The birth is not over until then.

   While doing these practical tasks, try to keep the room very calm and quiet, maintaining privacy so that the mother is not distracted from her baby.

    It’s a good idea to encourage the baby to latch on to the breast and to get the first sucking going if possible. This will stimulate more contractions. The cord is usually clamped and cut after it stops pulsating or after the placenta has emerged.

   You may be asked to leave the pool when you start to get third stage contractions, so that the placenta is delivered when you are outside the pool. It’s possible to stay in the water while the placenta emerges and many experienced water birth midwives will have no objection. There is no evidence of this being a problem. However, as there is still uncertainty about this, many midwives have to adhere to a policy of the placenta being born on dry land.

    The important issue now is not where the placenta emerges, but that first contact with your baby is undisturbed. So if you need to leave the pool, stand up holding your baby. Step carefully out of the pool and sit on a soft surface on the floor (an inflatable swimming ring covered by a soft towel is ideal!). Have someone drape some warm towels or a bathrobe over your shoulders and carry on welcoming and feeding your baby.

    The room needs to be warm to the point of ‘over heated’ so the baby is kept very warm by your body heat and the room temperature! A soft warm towel or flannel sheet can be placed over the baby in your arms. Skin-to-skin contact with your baby should be maintained continuously, until the placenta has emerged, as this will enhance bonding and stimulate third stage contractions simultaneously.

   These can feel very crampy and it is a great relief to give birth to the placenta, which is softer and smaller than a baby! It’s a surprisingly pleasurable feeling birthing the placenta.

  Most women feel ecstatic after a physiological water birth. Babies tend to be calmer and often seem to smile fleetingly, although their face muscles only become strong enough to sustain a smile at around 6 weeks old. They generally settle into life easily with a sense of wholeness and continuity from the shelter of the womb to the close contact with mum after the birth. Many mother’s feel that this is the kindest, gentlest and most loving way to have a baby and that nothing could be more natural. For you and your partner it can be wonderful way to celebrate the birth of your child.

    “I got into the pool at 5 cms dilated after approximately 4/5 hours of comfortable early labour at home, having used lots of movement and upright positions. Getting into the pool made me feel very comfortable and much more mobile and seemed to speed up labour. The contractions were very effective and I was fully dilated and ready to push after about 2 hours in the water. Our lovely daughter Lily Martha was delivered into the water after about 40 minutes of pushing and seemed very happy about the whole experience. I got out of the pool for a natural delivery of the placenta. I felt the whole experience of being at home and using the pool was amazing and contributed to a stress-free and wonderful natural birth.”

Melissa Clarke, London N1. First baby born 5th May 2001

Reasons to consider a water birth

Bridge to Health –  Sian Smith

When considering their birth plan, more and more women are choosing to include the use of water at some stage.

In fact, around 30% of women now plan to use this method either for birthing their baby or as a natural way to reduce some of the intense sensations (pain!) associated with labour.

Here are some of the reasons why:

Water is relaxing!

Being able to bob around in a large pool of warm water is the perfect environment to help you stay calm and relaxed, in a situation most would normally consider pretty stressful.

For many, sliding into a warm bath is the ‘go to’ choice of relaxation after a hard day, so what better way to help you through one of the most physically demanding and memorable experiences of your life?

Additionally, a calmer birth may be less stressful for your baby, as moving from an environment of warm amniotic fluid to one of warm water is a gentle way of introducing them to their new surroundings.

Water is a natural pain reliever

The relaxing effects of water help encourage the body to produce its own pain-fighting substances.

This is beneficial both for Mum and baby; for Mum staying relaxed helps stimulate her natural production of oxytocin (the’ love hormone’ that helps the uterus contract) and endorphins, the ‘feelgood’ hormones that help work as a natural pain reliever.

For baby, a happy and relaxed Mum is more likely to birth quickly with a reduced need for medical intervention.

It reduces stress and anxiety

It is not just the water that helps to relax you. With a waterbirth, often the entire surroundings are altered to create a calming ambience e.g. dimmed lights and hushed voices.

This enables you to go into your own world much more easily than if in a harshly lit room with strange people popping in and out.

Additionally, this type of relaxation helps encourage deep abdominal breathing, preventing you from becoming tense which may make contractions feel more intense.

It reduces the risk of perineal tearing

The warmth of the water helps to promote increased blood flow to the vagina and perineum (the area between the vagina and anus that is susceptible to tearing during childbirth).

This increases flexibility of the tissues and can reduce the likelihood of tearing when birthing the baby’s head.

It allows you to adopt a more ‘active’ birth position

A reason that some women choose a water birth is that it allows you to retain some control throughout the labour process –being aware of the contractions and sensations your body is experiencing, with a reduced chance of medical intervention.

Additionally, the sensation of ‘weightlessness’ that being in the water provides, enables you to move around much more freely than your body has allowed you to for a while!

You are free to adopt almost any position that feels comfortable for you.

Hp7

The classic image of a labouring woman is that of her laying on her back with her legs in stirrups.

Whilst this is the case for many, it is actually a fairly difficult way to birth your baby as you have to work against gravity to push the baby’s head UP and over the lowest part of the spine – the coccyx.

The best way to counteract this is to work with gravity and adopt a more ‘active’ squatting or modified squatting position.

Being in the water allows you to stay in these positions for longer, as you can lean against the side of the birthing pool for support.

Remaining fit, healthy and active will also help you have as smooth a pregnancy as possible.

Your Osteopath can advise you on exercises that are suitable throughout pregnancy, specifically core, pelvic and lower limb strengthening exercises that will help you be able to adopt active birth positions and use the correct muscles to birth your baby as efficiently as possible.

It is safe!

Of course, water births are not suitable for everyone – the main criteria is that Mum and baby must be healthy, the baby must be in a head-down position, and the pregnancy must be between 37 and 42 weeks.

But as the majority of pregnancies are healthy, a water birth can offer a natural and more in control option to the labour choices a woman has.

And finally, one of the most frequently asked questions regarding waterbirths appears to be ‘will my baby drown underwater?’… to which the answer is no!

The baby receives all of its oxygen via the placenta and hormones circulating through the baby ensure this occurs until the baby is lifted out of the water.

It is also known as the ‘foetal dive reflex’ and allows babies to be underwater for short periods of time up until around 6 months old.

Exploring breech water birth

Maggie Banks – RM, PhD, ADN, RGON

The paucity of literature on labour and birth in water with breech- presenting babies highlights a need to share (and document) empirical knowledge on the subject to piece together women’s and midwives’ growing experiences.

I was asked recently if leaving a woman in a birth pool to give birth to a breech presenting baby, undiagnosed until on the perineum, was ‘reasonable’ midwifery practice.

The question was qualified in that if the breech baby had been known prior to labour, the birth would definitely not have occurred in water as it is contraindicated in all the waterbirth guidelines in New Zealand.

My initial reaction, though fleeting, was to shrink away and not own my own experiences, knowing that these would be viewed as ‘unreasonable’ given that guidelines were presented as a self-evident truth that could not be argued with, that is, a known breech baby would not be born in water.

The issue of breech presentation and waterbirth is one that I have repeatedly explored in the midwifery and obstetric literature over the years and have found little written on the subject.

What is there usually cites the same source – Herman Ponette, the Belgium obstetrician in Ostend who actively promotes waterbirth with breech babies.1 There is minimal acknowledgement that it occurs in hospitals in the USA and the UK.2, 3

A Google search using the term ‘breech waterbirth’ brings up a handful of consumer stories and the occasional midwifery website which discusses the issue. Of the numerous stories I receive from women and midwives about breech birth, increasingly they involve the use of water.

This article pieces together some knowledge gained from reading, discussions, several of my experiences of, and reflections on, the use of water immersion with breech babies.

Going with the Flow

Initially I had been mindful of Michel Odent’s recommendation of not using deep warm water during breech labour as he warns that the soothing effect of water may mask an unduly painful labour, thereby preventing early detection of what may prove to be a problematic birth.4

My own first experience of using water in a breech labour happened by accident in that the frank breech baby remained undiagnosed until on the perineum. The woman had used the pool unconventionally in labour – she chose to lounge in the pool between contractions and stood during them. Once the breech was diagnosed I asked her to leave the pool and she stood to give birth.

This made me re-look at Michel’s caution. My experience of waterbirth with cephalic presentation had shown me that water immersion only mellows out normal labour pain, not severe or pathological pain, which would indicate the bone on bone painof true disproportion between pelvis and presenting part.

I had to question why this should be any different for a breech presenting baby – and I could not find an answer.

With the same woman’s second frank breech baby, this time diagnosed in pregnancy, she again used the pool unconventionally to relax between her contractions, and she birthed standing on dry land.

These two experiences marked a small shift in the use of water during my attendance at breech labour and birth in that water immersion remained available with a known breech. However, I continued to arrange with women that they would leave the pool for birthing.

This request changed following the birth of Heath, a firstborn presenting as a flexed legs breech. His mother had been deeply relaxed in the pool, assuming a wide open kneeling position leaning over the edge of the pool.

When the baby was visible on the perineum and the urge to push was overwhelming I asked the woman to leave the pool as we had prearranged, which she did.

Whereas she had been strong, independently held her own weight, and was powerful in her pushing, once out of the pool, she needed physical support to be in active birth positions and was unable to relax deeply between contractions as she had previously done in the pool.

The baby was born within half an hour of pushing and all was well but it was clear to me that I had intervened in a physiological birth and this had altered the ease with which the woman gave birth.

This birth occurred some months after the 1st International Waterbirth Conference in 1995.

Publication of Paul Johnson’s classic article 5 on the mechanisms that prevent or, conversely, stimulate breathing in the unborn baby during waterbirth would occur the following year but, in concluding his conference write up, Johnson, a Consultant Clinical Physiologist in the O&G Department at the John Radcliffe Hospital in Oxford, wrote:

“…if the onset of labour is spontaneous, and no drugs are administered, a fetus born with its cord intact, into warm, fresh water, not asphyxiated, is inhibited from breathing”6 – a process not dependant on presentation.

Initiation of breathing following waterbirth occurs once the baby surfaces and is exposed to cooler, dryer air and clamping the umbilical cord 6 – again, irrespective of presentation.

Sheila Kitzinger would report his additional comment that “if water births are of psychological and physiological benefit, it is logical that this benefit should apply to high-risk women too”.7

I knew deep water immersion to be a very powerful modality for achieving a relaxed state for the woman, enhancing vasodilation and placental perfusion and, therefore, oxygenation, of the tissues and organs, including the placenta during the normally stressing (not distressing) time of labour.

I had seen women become oblivious to everyone and everything as they sank into the pool. I had come to recognise the depth of sigh on entering the pool that signalled release of pain, fear, social etiquette and conversation – and these observations were irrespective of whether the baby was coming head or bottom first.

The Buoyancy and Warmth of Water

Another dimension was added when I attended a woman with twins, the second baby being a breech presentation. The woman had grown her babies well and began labour spontaneously at 40 weeks.

Due to the heaviness of her abdomen, she was drawn to labouring in water – her bath at home then, when labour was well established and she had travelled to her chosen birth place, the spa bath in the obstetric hospital.

There was a point in her labour where she needed to be more upright than reclining in the spa bath allowed, so we set up my free standing birth pool for her.

With the water up to the level of her breasts she became almost weightless in the pool, and was able to assume her intuitive positioning in a deep squat for the births of both her babies, the second of which had remained breech.

The woman reflected how supportive the water had been and how the upright position engaged her strength and ability to birth well.

Controlling Pelvic Pressure

When vaginal breech birth was a common occurrence 15 years or so ago, epidural anaesthesia was commonly recommended to overcome a premature urge to push. However, discussion with midwifery colleagues indicates a premature urge to push with a term breech baby is rare in woman-controlled positioning.

One woman who did experience significant pelvic pressure from the onset of labour with spontaneous rupture of membranes while having her first baby – a frank breech presentation – provided a piece to the mosaic of the use of water.

She controlled the urge to push by long and slow breathes during contractions and lying on her side on a floor mattress for most of her labour, rising only to crawl to the toilet on her hands and knees. After 12 hours of this, the pressure was overwhelming, even when lying.

While her good progress was evident from the lengthening burgundy buttock crease and her birthing energy, it was not time to use that expulsive energy. A vaginal examination confirmed a thin rim of cervix remained.

While a hands and knees position reduced the pressure, it was not until she lounged in the pool on her abdomen that the pressure again became tolerable. The pool was invaluable for enabling her to resume breathing over the contractions for the next three hours.

In the last hour prior to the birth, the woman commenced her grunting expulsions. As this had not brought her baby to a visible position in that time, I asked her to stand for one contraction to test the power of this feeling.

Simply standing engaged the pelvic pressure enough to bring the baby to almost rumping with the first push.

The second surge saw the baby rumped and progress so the popliteal spaces (back of the knees) were visible. With the next, he was born to the ankles, then descended quickly to wear his ‘perineal hat’ and his head was gently released without perineal trauma. All of this occurred without a contraction as the women responded to the pelvic pressure.

Assessing the Baby

The New Zealand Guideline Group’s best practice evidence-based guideline on breech labour and birth acknowledges that the evidence does not support continuous electronic foetal heart rate (EFM) monitoring by cardiotocography over intermittent auscultation.8

This is because, just as for well women and their babies with no alerting factors, there are no significant differences in standard measures of newborn wellbeing (including cerebral palsy and infant mortality) with continuous EFM in labour for ‘high risk’ situations, which frank or flexed legs breech presentation at term is deemed to be by some.

Only beneficial for its association with a reduced incidence of neonatal seizures, continuous EFM is associated with increased maternal morbidity by way of the accompanying increase in Caesarean and operative birth rates.9

At any given point the midwife needs to know that the baby is coping well with labour by assessment of his movements10 and listening to his heart beat.

As with any other labour for well women and babies, listening can be easily acheived with a Pinard stethoscope (or handheld, waterproof doppler) during water immersion.

Essential Elements of Physiological Breech Birth

Midwives commonly reflect on how their practice changes with attending waterbirths of cephalic presenting babies to become more ‘hands-off ’ during birth.

Confident that the water frequently dissipates urges to explosively push, while also supporting the woman’s perineal tissues and the baby as he is born, the midwife is drawn to a non touch vigilant attendance. This ‘hands off ’ in the absence of problems is the ‘golden rule’ during breech birth.

Maternal effort is an important part of achieving a ‘hands-off ’, spontaneous birth. As with any birthing, the woman needs to be supported to choose positions of comfort in the water which enhance her power and strength – kneeling, squatting, hands and knees or reclining.

Whichever birth position is chosen, the midwife needs to position herself so she can see both the advancing baby and the umbilical cord, and be in a position to palpate the umbilical cord if necessary.

The midwife may need ‘hands on’ for the birth of the head but the support of the water usually ensures gentle and woman- controlled birth of the baby’s head. Due to the reduction in gravity and an accompanying reduction in an urge to push for the head, the woman may need to be reminded to release the baby’s head.

Midwives who regularly attend waterbirths with cephalic presentation frequently reflect that if there is a problem during birth, for example, shoulder dystocia, they will initially try to correct it in the pool.

This avoids delay while utilising the water’s buoyancy so the woman can move easily to adopt very wide open positions that are needed for manoeuvres.

While Pinotte1 notes a reduced need for routine manipulations of the breech baby with waterbirth, in the rare circumstance that a manoeuvre is needed – to bring down stuck arms11 and/or flex, cradle and scoop out the baby’s head12 – these could also initially be done in the pool, again, avoiding delay.

The woman, however, would be asked to get out of the pool if problems were not easily remedied.

The Ongoing Mosaic

For some maternity professionals the issue of vaginal breech birth is no longer worth considering in the wake of the Term Breech Trial13 despite concerns about its methodological flaws.14-17

For others it remains a planned option.18-22 There will, of course, always be undiagnosed breech babies in labour, irrespective of the degree of antenatal scrutiny.

While some consider undiagnosed breech an ‘obstetric emergency’, the manner in which a midwife facilitates
a vaginal breech birth, first diagnosed when birth is imminent, is the sameas if it was diagnosed antenatally and a vaginal breech birth is planned, albeit the latter having obstetric backup available with the birth in an obstetric hospital.

The use of deep water immersion with mal-presentation (read: breech)
is contraindicated in hospital clinical guidelines on waterbirth, and the use of water is absent as a modality in vaginal breech birth guidelines.

Embracing these, giving birth in water to a breech baby would be out of the question for some maternity providers.

Yet others are very specific
 in seeing breech presentation as a positive indication for waterbirth because of the buoyancy afforded to the baby and umbilical cord, both of which are kept warm in the water until surfacing into the cooler air,1,23,24 contraindicated only if the breech labour is not progressive and/
or is complicated.25

Midwifery can have additional knowledge fragments to obstetric knowledge, gained by our deep relationships with women.

Being attentive to women who are called to use water through breech labour and birth and walking side by side with them during this time has added to my understanding of facilitating physiological breech birth.

We need to be able to share the practice wisdom which comes from our experiences, discussions and reflections. We also need to be able to do this without fear of repercussions that may be activated from that disclosure. As a result, we will continue to find ongoing pieces to the mosaic of breech waterbirth.

References:

Ponette H. Breech and twin deliveries in the water. Accessed 20 March 2000. Available at http://www.helsinki. fi/~lauhakan/whale/waterbaby/p6.html
Kitzinger S. Sheila Kitzinger’s letter from England. Birth 1991;18(3):170–171.
Harper B. Waterbirth basics – from newborn breathing to hospital protocols. Midwifery Today 2000;54:9– 10,12–15,68.
Odent M. Birth reborn. Souvenir Press: New York, 1984:103–105.
Johnson P. Birth under water – to breathe or not to breathe. BJOG: An International Journal of Obstetrics and Gynaecology 1996;103(3):202–208.
Johnson P. Birth under water – to breathe or not to breathe. In, Lawrence Beech BA (ed).Water birth unplugged. Proceedings of the First International Water Birth Conference. Books for Midwives: Cheshire, England, 1996:31–33.
Kitzinger S. Sheila Kitzinger’s letter from England: is water birth dangerous? Birth 1995; 22(3):172–173.
New Zealand Guidelines Group. Care of women with breech presentation or previous Caesarean birth. New Zealand Guidelines Group: Wellington, 2004:xxi, 32.
Alfirevic Z, Devane D, Gyte GML. Continuous cardiotocography (CTG) as a form of electronic fetal monitoring (EFM) for fetal assessment during labour. Cochrane Database of Systematic Reviews 2006, Issue 3. Art. No.: CD006066. DOI: 10.1002/14651858. CD006066.
Banks M. Utilising the unborn baby’s in-labour movements. New Zealand College of Midwives Journal 2003;29:6.
Banks M. Breech birth woman-wise. Birthspirit: Hamilton, New Zealand, 1998:88–89.
Ibid., pp. 90–91.
Hannah M, Hannah WJ, Hewson SA, Hodnett ED, Saigal S, et al. Planned caesarean section versus planned vaginal birth for breech presentation at term: a randomised multicenter trial. Lancet 2000;356:1375–1383.
Glezerman M. Five years to the term breech trial: the rise and fall of a randomized controlled trial. American Journal of Obstetrics and Gynecology 2006;194(1):20–25.
Kotaska A. In the literature: combating coercion: breech birth, parturient choice, and the evolution of evidence-based maternity care. Birth 2007;34(2):176–180.
Keirse MJNC. Evidence-based childbirth only for breech babies? Birth 2002;29(1):55–59.
Goer H. When research is flawed: planned vaginal birth versus elective Cesarean for breech presentation. Accessed 14 August 2007. Available at http://www.lamaze.org/ Research/WhenResearchisFlawed/ VaginalBreechBirth/tabid/167/ Default.aspx
Goffinet F, Carayol M, Foidart J, Alexander S, Uzan S, et al. Is planned vaginal delivery for breech presentation at term still an option? Results of an observational prospective survey in France and Belgium. American Journal of Obstetrics and Gynecology 2006;194(4):1002–1011.
Hellsten C, Lindqvist PG, Olofsson P. Vaginal breech delivery: is it still an option? European Journal of Obstetrics & Gynecology and Reproductive Biology 2003;111(2):122–128.
Sibony O, Luton D, Oury J, Blot P. Six hundred and ten breech versus 12,405 cephalic deliveries at term: is there any difference in the neonatal outcome? European Journal of Obstetrics & Gynecology and Reproductive Biology 2003;107(2):140–144.
Giuliani A, Schöll WMJ, Basver A, Tamussino KF. Mode of delivery and outcome of 699 term singleton breech deliveries at a single centre. American Journal of Obstetrics and Gynecology 2002;187(6):1694–1698.
van Roosmalen J, Rosendaal F. There is still room for disagreement about vaginal delivery of breech infants at term. BJOG: An International Journal of Obstetrics and Gynaecology 2002;109(9):967–969.
Charkowsky I. In: Napierala S. Water birth: a midwife’s perspective. Bergin & Garvey: London, 1994:181–182.
Enning C. Personal communication, 2008.
Ponette H. The New Aquatic Maternity in Ostend. Accessed 20 March 2000. Available at http://www.helsinki. fi/~lauhakan/whale/waterbaby/p2.html

The benefits of labouring in water for overweight and obese mothers

Excerpt from article published by Big Birtha who provides information and support for bigger mums and mums to be.

All women are more buoyant and supported by water, it’s one of the reasons swimming and aqua aerobics are particularly good forms of exercise while pregnant.

But the benefit is likely to be greater for obese women, as fatter bodies are naturally more buoyant.

The buoyancy and support provided by water eases movement, which may make both maintaining an active labour and facilitating access for monitoring easier.

On land, it is cumbersome and difficult for a heavily pregnant woman of any size to quickly move between kneeling, reclining, sitting, leaning, crouching, turning from front to back etc.

In water, it is simple and easy to shift to whatever position is most comfortable/convenient, even midway through contractions.

Being in water also promotes positions which are more agreeable for birthing. Lying flat on your back on a bed is one of the worst positions to be in during labour.

When you are on your back you are working against gravity; actually trying to push the baby out uphill.

It’s only a slight incline, but it’s there.

To add to the problem, when lying down, your body weight is also resting on your coccyx (tailbone), forcing it into the pelvic cavity and reducing space for the baby.

In water, even if you were to float on your back, you wouldn’t be putting the same pressure on your tailbone, and you are far more likely to take an upright position, crouching or kneeling, for instance; positions which on land are uncomfortable to maintain, but not in water.

This frees up your coccyx to keep out of the way.

It is well documented that warm water reduces pain felt by labouring women, and decreases the use of other pain relief.

Given the issues with providing epidural anaesthesia to obese women, it seems sensible that using water; an effective non-pharmaceutical intervention to help with pain should be an attractive alternative?

Obese women are at increased risk of having longer labours, and of moving on to instrumental delivery and caesarean sections for ‘failure to progress’.

Yet immersion in water has been shown to significantly reduce the length of labour in ‘normal’ sized women.

It doesn’t take much of a leap of imagination to consider that water might help to address this problem, at least in some obese women?

BigBirtha.co.uk...

Active Birth Pools are specially designed for to accomodate bigger mothers enabling them to move and benefit from the positions natural to labour and birth.

Various means of entry and exit from the pool as well as emergency evacuation have been considered and designed for to safeguard  over weight mothers and the midwives who care for them.